THG09-001
Answer the following:
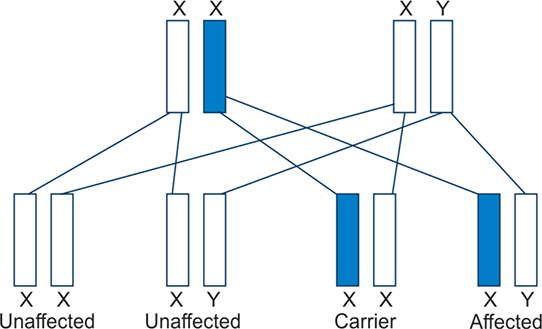
a. The following pedigree is an example of which mode of Mendelian inheritance.
b. In this inheritance, affected fathers do not transmit to their sons. State True/False
c. All daughters of affected fathers are carriers in this inheritance. State True/False
d. Name three examples of this inheritance.
Answer
- a. X-linked recessive
- b. True
- c. True
- d. Hemophilia, glucose-6-phosphate dehydrogenase (G6PD) deficiency, and Duchenne muscular dystrophy
THG09-002
Match the following:
| Congenital anomalies | Process | Example |
|---|---|---|
| 1. Malformation | A. Breakdown of normal tissue | a. Congenital talipes equinovarus (CTEV) |
| 2. Dysplasia | B. Abnormal formation of tissue | b. Amniotic band syndrome |
| 3. Deformation | C. Abnormal organization of cells in tissue | c. Achondroplasia |
| 4. Disruption | D. Unusual forces on normal tissue | d. Spina bifida |
Answer
- 1 – B, d (Malformation – Abnormal formation of tissue – Spina bifida)
- 2 – C, c (Dysplasia – Abnormal organization of cells in tissue – Achondroplasia)
- 3 – D, a (Deformation – Unusual forces on normal tissue – Congenital talipes equinovarus [CTEV])
- 4 – A, b (Disruption – Breakdown of normal tissue – Amniotic band syndrome)
THG09-003
A 7-year-old boy is being followed up in the child development clinic for the past 3 years for behavioral problems. He was disruptive and rebellious in his class. His academic performance was poor. He had an uneventful antenatal period with a normal perinatal transition. His growth was appropriate and his gross motor skills were age-appropriate. He had an elder sibling aged 16 years who had “some problem with his muscles” and was wheel-chair bound from the age of 11 years. His mother said that the elder sibling had walked late at 22 months and seemed to lose his ability to walk gradually as he got older. In the initial workup of this child, his blood tests included liver function tests (LFTs): Serum bilirubin—23 mg/dL (conjugated 8 mg/dL), aspartate aminotransferase (AST)—102 IU/L, alkaline phosphatase (ALP)—156 IU/L, serum albumin—3.8 g/dL, creatine phosphokinase (CPK)—800 IU/L. His mother’s CPK was 810.
a. What is the likely diagnosis in this child?
b. What is the explanation for the raised CPK level?
c. Which test would clinch the diagnosis?
d. What is the chance of recurrence of the condition?
Answer
- a. Klinefelter syndrome. This syndrome presents at pubertal age with delayed puberty, eunuchoid habitus with cryptorchidism and poorly developed phallus. But in childhood they present as behavioral problems and psychiatric disturbances and the diagnosis is not then established unless a karyotype is done.
- b. In this case, his 16-year-old brother has Duchenne dystrophy from the history, but this boy is asymptomatic with an elevated CPK because of the extra X chromosome, i.e., he is acting like a carrier.
- c. Karyotyping
- d. Less than 1% as Klinefelter syndrome is likely to be due to nondisjunction.
THG09-004
Match the following about nonsyndromic craniosynostosis:
| Skull Shape | Suture |
|---|---|
| 1. Dolichocephaly | A. Metopic suture |
| 2. Brachycephaly | B. Sagittal suture |
| 3. Turricephaly | C. Bilateral coronal suture |
| 4. Trigonocephaly | D. Fusion of four or more sutures |
Answer
- 1 – B (Dolichocephaly – Sagittal suture)
- 2 – C (Brachycephaly – Bilateral coronal suture)
- 3 – D (Turricephaly – Fusion of four or more sutures)
- 4 – A (Trigonocephaly – Metopic suture)
THG09-005
A 16-month-old girl has a history of Pierre Robin sequence with cleft palate repair at 6 months. She has high myopia and mild high-tone sensorineural deafness. She has moderate joint hypermobility.
a. What is the most likely diagnosis?
b. Which test would help in confirming the diagnosis?
c. Name two other skeletal manifestations which can occur in this condition.
d. What is the recommended surveillance for this condition?
Answer
- a. Stickler syndrome
- b. Exome sequencing
- c. Early-onset arthropathy/osteoarthrosis/scoliosis, kyphosis
- d. Annual eye examination and hearing assessment
THG09-006
A 6-week-old baby was referred for failure to thrive. He was born at term with a birth weight of 2.2 kg. Baby had microcephaly with maxillary hypoplasia and long smooth philtrum. He had a systolic murmur on auscultation.
a. What is the most important history which would give a clue to the diagnosis?
b. True/False—the causative agent is extremely teratogenic in all trimesters of pregnancy.
c. Name four central nervous system (CNS) abnormalities seen in this condition
Answer
- a. Alcohol consumption during pregnancy suspecting fetal alcohol syndrome
- b. True
- c. Microcephaly, structural brain anomalies like partial or complete agenesis of corpus callosum, cerebellar hypoplasia, developmental delay, intellectual deficit, neurobehavioral abnormality, and cognitive dysfunction
THG09-007
A 5-day-old baby presented to your outpatient department (OPD) with poor suck. On examination, the baby is hypotonic, has flat facies, slanted palpebral fissures, small ears, short neck, and single palmar crease. On auscultation, this baby has systolic murmur.
a. What test would you like to do to confirm the diagnosis?
b. What is the most common cardiovascular abnormality associated with it?
c. What is the prevalence of hypothyroidism in this condition? Which growth chart would you use for this baby?
d. What is the risk of recurrence in the next baby?
Answer
- a. FISH (fluorescent in situ hybridization) for chromosome 21 (reported in 48–72 hours) and karyotyping (reported in 2–3 weeks)
- b. Endocardial cushion defect
- c. 50%. CDC (Centers for Disease Control and Prevention) growth chart for Down syndrome (DS)
- d. If the previous child has trisomy 21/nonfamilial translocation DS, the recurrence risk is 1% more than the age-related risk of the mother. If the mother is a translocation carrier, then the recurrence risk of DS is 10–15% whereas if the father is a carrier, then the recurrence risk is 1–3%. If the parent is a 21q21q translocation carrier, then the recurrence risk is 100%.
THG09-008
A 14-year-old girl was brought by her mother with complaints of primary amenorrhea. You noticed that she is short stature, has slight webbing of neck, shield-like chest, and hyperconvex nails. She has a systolic murmur on auscultation. You did karyotyping and it revealed the following:
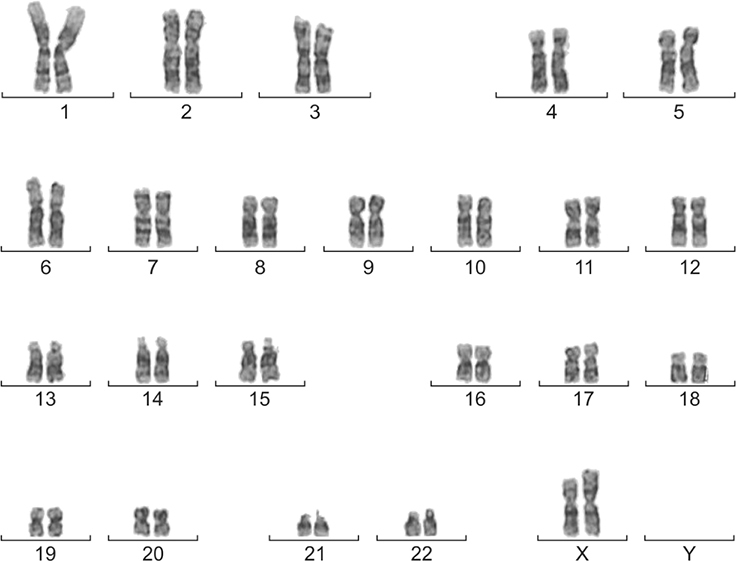
a. What is the interpretation of the above test and what is the diagnosis?
b. What is the most common cardiovascular and renal abnormality associated with it?
c. What are the potential medical interventions to address growth and development?
Answer
- a. Karyotyping reveals 46,X,i(Xq) suggestive of isochromosome Xq and Turner syndrome. At cell division instead of dividing longitudinally, the X chromosome divides transversely, resulting in a X chromosome with two q arms and no p arm, called isochromosome Xq.
- b. Coarctation of aorta and horseshoe kidney
- c. Growth hormone therapy indicated as early as possible (4–6 years) preferably before 12–13 years, which can significantly improve final adult height. Low-dose estrogen replacement therapy to induce puberty and promote secondary sexual characters.
THG09-009
A 6-year-old boy was referred for evaluation of hyperactivity disorder. As an infant, he had interrupted aortic arch syndrome and a cleft lip, both of which have been repaired. He was the second born of a nonconsanguineous couple. First sibling died in the neonatal period following cardiac surgery for truncus arteriosus.
a. What is the most likely diagnosis?
b. What tests will confirm the diagnosis?
c. What other blood investigation would you do?
d. How will you counsel regarding recurrence risk to the parents?
Answer
- a. DiGeorge syndrome
- b. FISH for 22q11 microdeletion in the index child followed by FISH for 22q11 microdeletion in parents. If the clinical picture is not clear, chromosomal microarray can be suggested.
- c. Plasma calcium and complete blood count [T, B, and natural killer (NK) cell lymphocyte subsets]
- d. It is inherited in autosomal dominant pattern. If it is de novo deletion in the child, the recurrence risk is very low. If one of the parents carries the microdeletion, the recurrence risk to their offspring is 50% in their future pregnancy. Likely to be an autosomal dominant pattern in this family due to the sibling history of cardiac condition.
THG09-010
A 2-year-old boy presented with developmental delay. He has a small head, small bulbous nose, puffy eyes, full lips, full cheeks, long philtrum, small widely spaced teeth, and small chin (elfin-like facies). He is very friendly and sociable.
a. What is the likely diagnosis?
b. Which test will you order to confirm the diagnosis?
c. What is the most common cardiac condition associated with it?
d. Name some endocrine abnormality seen in this condition.
Answer
- a. Williams syndrome
- b. FISH for microdeletion analysis for locus 7q11.23
- c. Supravalvular aortic stenosis
- d. Hypercalcemia, hypercalciuria, and subclinical hypothyroidism
THG09-011
A 10-year-old boy is brought to you by his mother with complaints of excessive weight gain. He has an insatiable appetite. He had a history of acting aggressively with irrational rage when food is restricted. He has typical facial features of almond-shaped eyes, narrow nasal bridge, and thin upper lip with downturned corners of the mouth. He has micropenis with poorly rugated scrotum and small testicles.
a. What is the likely diagnosis?
b. How will you confirm the diagnosis?
c. Name one endocrine abnormality associated with it.
d. Growth hormone (GH) therapy is indicated in this condition—True/False.
Answer
- a. Prader–Willi syndrome (PWS)
- b. DNA methylation studies for PWS. Karyotype of the proband and FISH or chromosomal microarray to identify the deletion
- c. Hypothalamic dysfunction causing GH deficiency, central hypothyroidism, central adrenal insufficiency, and hypogonadism
- d. True
THG09-012
State True/False regarding triple nucleotide repeat disorder:
a. Disease phenotype worsens from generation to generation.
b. More the repeats, later is the disease.
c. Longer the repeat, the more severe the disease is.
d. Name two trinucleotide repeat disorders.
Answer
- a. True
- b. False
- c. True
- d. Any two of the following: Huntington’s disease, myotonic dystrophy, fragile X syndrome, and Friedreich ataxia
THG09-013
A 35-year-old pregnant woman who has conceived for the first time comes for prenatal counseling as she is anxious about her age. She is 10 weeks pregnant now.
a. What screening test would you advise?
b. What gestation should this test be done?
c. What is the detection rate for trisomy 21?
d. What is noninvasive prenatal testing (NIPT)? What is the detection rate for trisomy 21 in NIPT?
Answer
- a. First trimester combined screening (FTCS) tests: Nuchal translucency (NT) + β-human chorionic gonadotropin (β-hCG) + PAPP-A (pregnancy-associated plasma protein A) + maternal age
- b. 11–13 weeks
- c. Around 90%
- d. Noninvasive prenatal testing (NIPT) is a noninvasive screening method that analyses cell-free fetal DNA (cffDNA) that is circulating in the maternal blood. Fetal cfDNA constitutes 10–20% of the total cfDNA of the mother. It originates from the placenta but represents fetal genotype. The detection rate of DS in NIPT is 98–99%.
THG09-014
A 6-year-old boy presented to your clinic with intellectual disability. You noticed the boy avoids eye contact, does not respond to his name, but notices a small sound coming from the AC in the office. He keeps flapping his hands.
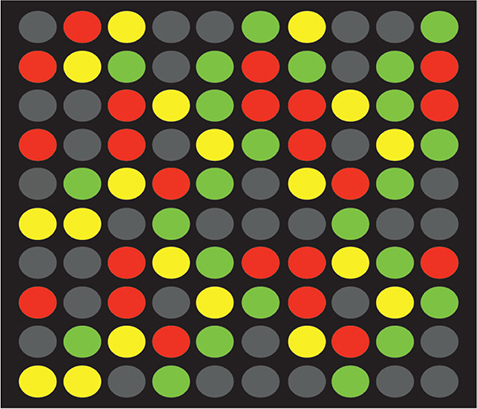
a. What genetic testing is shown in the picture above?
b. What is the principle behind this testing?
c. Which clinical conditions would you like to order this test?
Answer
- a. Chromosomal microarray
- b. Compares the sample DNA with control for copy number variations (CNVs)
- c. Unexplained developmental delay, intellectual disability, multiple congenital anomalies, and autism spectrum disorder
THG09-015
You are called to see a 3-day-old girl baby in the postnatal ward for poor feeding and abnormal movements. She was born to a nonconsanguineous couple. Antenatal scans were normal except for polyhydramnios. On examination, she has mild dysmorphic features with high forehead with central furrowing, bitemporal narrowing, and bilateral fifth finger clinodactyly. She has axial hypotonia and poor sucking reflex. While examining, she has multifocal clonic seizures. After transferring to neonatal intensive care unit (NICU) she continues to have refractory seizures. She requires nasogastric feeding and has poor weight gain and head growth. Complete septic screen and metabolic tests were performed and found to be normal. Formal electroencephalogram (EEG) and cranial ultrasound were requested.
a. The EEG shows hypsarrhythmia. What is the treatment of choice?
b. The cranial ultrasound shows few visible gyri and absent corpus callosum. What is the next step?
c. What is the likely diagnosis?
d. Which testing would confirm the diagnosis?
Answer
- a. Steroid medication: Adrenocorticotropic hormone (ACTH), dexamethasone, prednisone, and hydrocortisone have all been used. Treatment of hypsarrhythmia is difficult and is resistant to most antiepileptic drugs.
- b. Magnetic resonance imaging (MRI) of the brain
- c. Neuronal migration disorder / Miller–Dieker syndrome, as suggested by her clinical features and MRI, which showed lissencephaly and absent corpus callosum.
- d. Chromosomal microarray / MLPA (multiplex ligation-dependent probe amplification) for microdeletion syndrome (Miller–Dieker syndrome—microdeletion of 17p13.3)
THG09-016
A 11-year-old boy was referred by the school nurse for investigation of his short stature. He was born on the 50th percentile for height but on presentation, was below the 3rd percentile. As a baby, he suffered from gastroesophageal reflux, recurrent vomiting, and failure to thrive. He walked at 20 months. He was thought to be clumsy and diagnosed as dyspraxia. General examination revealed a prominent chest, systolic murmur of grade 3/6, well conducted to the back, low posterior hairline, and small-volume testes. His bone age was 8 years.
a. What is the probable diagnosis?
b. What is the most common mode of inheritance of this condition?
c. How will you confirm the diagnosis?
d. Name two common cardiac conditions associated with this condition.
e. Which malignant condition are these children predisposed to?
Answer
- a. Noonan syndrome (NS)
- b. Autosomal dominant
- c. Gene panel testing / exome sequencing; the most common gene: PTPN11
- d. Pulmonary valve stenosis, hypertrophic obstructive cardiomyopathy (HOCM)
- e. Juvenile myelomonocytic leukemia (JMML); children with NS having JMML have a better prognosis compared to those without NS.
THG09-017
A 25-day-old male child presented with hypotonia and weakness, proximal > distal; Examination shows an alert child with absent deep tendon reflex (DTR) and tongue fasciculation.
a. What is the likely diagnosis?
b. What genetic tests would confirm the diagnosis
c. What is the latest treatment available for this condition?
d. Which is the commonest genetic mechanism in this condition?
Answer
- a. Spinal muscular atrophy (SMA)
- b. MLPA / qPCR (quantitative Polymerase chain reaction)
- c. Gene therapy
- d. Exonic deletion / exon 7 deletion
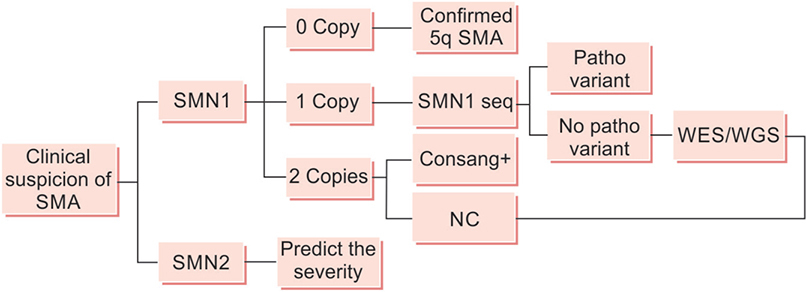
Approach to clinical suspicion of SMA
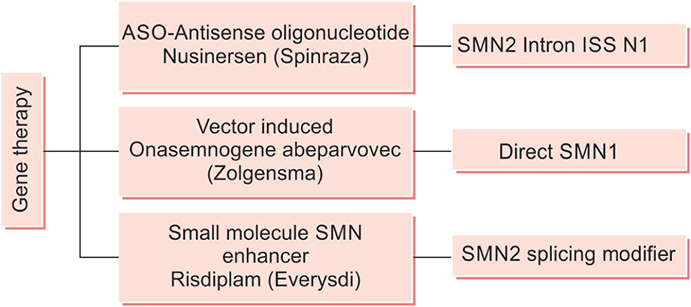
Gene therapy in SMA
THG09-018
A 11-year-old boy was referred for delayed eruption of his permanent dentition. His past medical history showed that he underwent surgical orchidopexy. On examination, his weight is between 50th and 90th centile and height between the 2nd and 9th centile. He has mild frontal bossing and prominent jaw, delayed dentition. When asked, he was able to bring both shoulders around so that they meet anteriorly in the midline. The radiograph below, shows the classical abnormality associated with this disease.
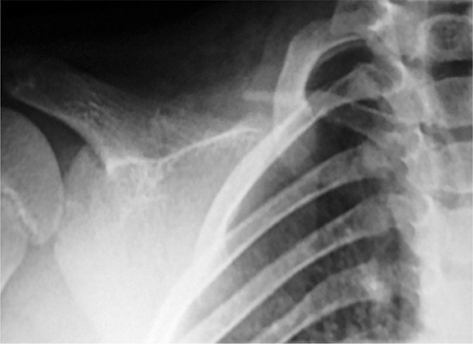
a. What does the radiograph show?
b. What is your diagnosis?
c. What is the usual inheritance pattern of this disease?
d. What is the line of management?
Answer
- a. Clavicular hypoplasia
- b. Cleidocranial dysostosis
- c. Autosomal dominant
- d. Multidisciplinary approach: Orthopedics, physiotherapy, respiratory, genetics, and maxillofacial
THG09-019
A 37-week-old female infant is born via cesarean delivery due to preeclampsia to a 26-year-old G1 mother. All maternal serologic test results are within normal limits. The pregnancy was complicated by maternal primary generalized epilepsy treated with monotherapy and supplemented with folic acid, mild thrombocytopenia attributed to side effect of medication, which later improved. On examination, the neonate is found to have subtle dysmorphism with flat nose, cleft lip and palate, lumbosacral meningomyelocele, and splaying of sagittal sutures. Cranial ultrasound reveals Chiari II malformation and mild ventriculomegaly. Echocardiogram reveals a large perimembranous ventricular septal defect (VSD) and a moderate secundum atrial septal defect (ASD). Abdominal and renal ultrasounds are unremarkable.
a. What is the likely diagnosis?
b. What is the recurrence risk in next pregnancy?
c. How could this have been prevented?
d. Name two likely mechanisms which led to this birth defect.
Answer
- a. Fetal valproate syndrome
- b. Around 50–55%, if the mother continues to take sodium valproate. If she switches to less teratogenic medication, the risk reduces accordingly.
- c. Switching over to monotherapy with least teratogenicity like lamotrigine
- d. Proposed mechanisms of valproic acid (VPA) teratogenicity include folic acid deficiency, oxidative stress, and inhibition of histone deacetylases that result in altered gene expression
THG09-020
A woman who is 8 weeks pregnant would like to know the risk for her unborn baby as she had inadvertently got exposed to radiation. She underwent chest X-ray 1 week prior to this for her lower respiratory tract infection. She was unaware of her pregnancy at the time of exposure.
a. What is the risk to her fetus?
b. What is the unit of radiation exposure and what is the limit for teratogenicity?
c. How would you counsel her?
d. Which radiation exposure has maximum risk of teratogenicity? What is the future risk of cancer?
Answer
- a. Radiation exposure from chest X-ray is 0.1 mSv or 0.01 rad
- b. Unit of radiation exposure rad or millisievert (mSv). Safety level of 5 rads or 50 mSv
- c. Fetus has low risk as the exposure is less than safety level of 5 rads or 50 mSv
- d. Barium enema / abdominal CT
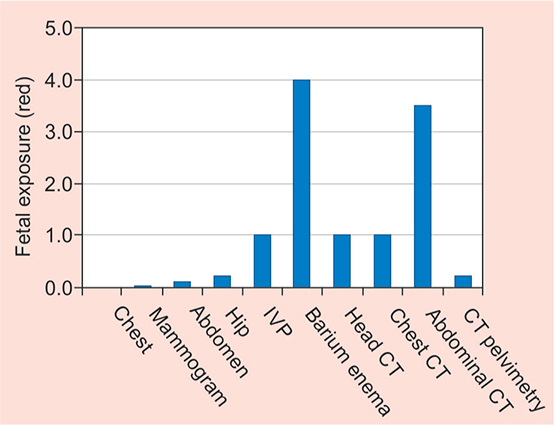
Exposure of conceptus from diagnostic X-ray studies
THG09-021
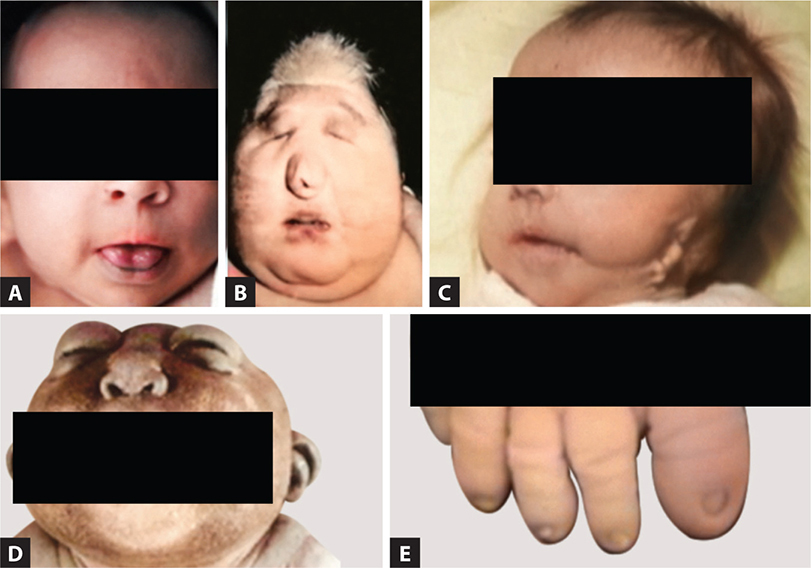
Identify the congenital malformation and match with the teratogens in given images A to E.
- Isotretinoin
- Maternal diabetes
- Methotrexate
- Phenytoin
- Alcohol
Answer
- 1 – C (Isotretinoin – Craniofacial abnormality)
- 2 – B (Maternal diabetes – Holoprosencephaly)
- 3 – D (Methotrexate – Anencephaly)
- 4 – E (Phenytoin – Hypoplastic nails)
- 5 – A (Alcohol – Smooth philtrum)
Salient Features
- A. Smooth philtrum
- B. Holoprosencephaly
- C. Craniofacial abnormality
- D. Anencephaly
- E. Hypoplastic nails
Features in Detail
- Isotretinoin embryopathy: Craniofacial, cardiac, thymic and central nervous system malformations. Cleft lip, thymic aplasia, neural tube defect, microtia, micrognathia.
- Congenital malformation seen in infant of diabetic mother: Comprised of neural tube defects, hydrocephalus, anencephaly, hydranencephaly, holoprosencephaly, microcephaly, and caudal dysgenesis.
- Fetal methotrexate syndrome: Microcephaly, craniosynostosis, large fontanelles, skull defects, and hypoplasia of the skull bones. Holoprosencephaly, choroid plexus cysts, cerebellar hypoplasia, absent corpus callosum, tetralogy of Fallot, pulmonary valve atresia, limb reduction defects, and syndactyly.
- Fetal hydantoin syndrome: Abnormalities of skull and facial features, growth deficiencies, underdeveloped nails of fingers and toes.
- Fetal alcohol syndrome: Distinctive facial features, including small eyes, an exceptionally thin upper lip, a short, upturned nose, and a smooth skin surface between the nose and upper lip (smooth philtrum). Deformities of joints, limbs and fingers. Vision difficulties or hearing problems. Small head and brain size. Heart defects and problems with kidneys and bones.
THG09-022
A 5-year-old boy presented with developmental delay noted during infancy and behavioral problems for the past 2 years. His perinatal and family history was unremarkable. He was hyperactive and aggressive and had behavioral issues and showed bizarre habits like smelling of undergarments and chewing of his dress. During examination he was alert, interested in surroundings, responded to simple commands, and indicated toilet needs but could not sit at one place.
a. What is the likely diagnosis?
b. Which test would help in confirming the diagnosis?
c. Which clinical finding in external genital examination would be present in this condition?
d. What is the mode of inheritance?
Answer
- a. Fragile X syndrome
- b. DNA methylation studies / msTP PCR (methylation-sensitive triplet-repeat primed PCR)
- c. Macroorchidism / large testis. Usually in postpubertal boys
- d. X-linked dominant
THG09-023
A term baby boy was admitted to the neonatal unit at 4 hours of age with respiratory distress. On admission, he was noted to be micrognathic, with a posterior cleft palate, syndactyly of the second and third toes of both feet and mildly reduced tone. Initial septic workup and baseline metabolic testing [tandem mass spectrometry (TMS) and gas chromatography mass spectrometry (GCMS)] were normal. Progress was slow, he was hypotonic and remained reluctant to feed, requiring top-ups via a nasogastric tube to ensure adequate calorie intake. At 4 weeks of age, he developed persistent vomiting. A repeat septic screen was negative. The venous blood gas revealed a pH of 7.49, bicarbonate of 36.2 mmol/L, and potassium of 3.0 mmol/L. Suspecting an underlying genetic etiology, cholesterol, and dehydrocholesterol was ordered.
a. What is the cause of respiratory distress? Which position would help in respiratory distress?
b. What metabolic abnormality has he developed? What is the likely cause for this metabolic abnormality?
c. What is the possible underlying etiology?
Answer
- a. Pierre Robin sequence / micrognathia; Due to the tongue obstructing the airway; prone position
- b. Metabolic alkalosis; infantile hypertrophic pyloric stenosis
- c. Smith–Lemli–Opitz syndrome.
THG09-024
A 20-day-old child presented with progressively worsening jaundice. She had persistent pulmonary hypertension (PPHN) during the neonatal period and was subsequently discharged home on day 10 of life. Other examination findings included a large broad forehead, a straight pointed nose, deep-set eyes, a soft systolic murmur, and hepatosplenomegaly. Evaluation revealed conjugated hyperbilirubinemia, elevated alanine transaminase, γ-glutamyl transferase (GGT), and hypertriglyceridemia. Liver biopsy was performed as a part of cholestasis evaluation, which showed bile duct to portal tract ratio of 0.7, indicating ductal paucity.
a. What is the likely diagnosis?
b. How would you confirm this?
c. What is the eye sign found in this condition?
d. What nutritional deficiency is this child at risk of and how would you prevent it?
Answer
- a. Alagille syndrome
- b. Molecular testing / exome sequencing. Mutation in JAG1
- c. Posterior embryotoxon
- d. Fat-soluble vitamin deficiency due to fat malabsorption secondary to chronic cholestasis. Dietetic support with fat-soluble vitamin supplementation.
THG09-025
A 9-year-old female child, firstborn to nonconsanguineous parents by lower segment cesarean section (LSCS), had an uneventful neonatal period. She had delayed motor milestones and delayed speech. She developed seizures at 1 year. On examination, she had a small head, pointed chin, wide jaw, and protruding tongue. She had repetitive movements and inappropriate intermittent laughter and found to have unsteady gait.
a. What is the likely diagnosis?
b. Which genetic test usually helps in confirming the diagnosis?
c. Name two genetic mechanisms which result in this condition.
Answer
- a. Angelman syndrome
- b. MS MLPA—Methylation-specific MLPA
- c. Deletion, uniparental disomy, and imprinting disorder.