VVK19-001
Metabolic compensation of respiratory disorders.
| Disorder | Metabolic Compensation |
|---|---|
| Acute respiratory acidosis | ( |
| Chronic respiratory acidosis | ( |
| Acute respiratory alkalosis | ( |
| Chronic respiratory alkalosis | ( |
Answer
| Disorder | Expected Compensation |
|---|---|
| Acute respiratory acidosis | ( |
| Chronic respiratory acidosis | ( |
| Acute respiratory alkalosis | ( |
| Chronic respiratory alkalosis | ( |
VVK19-002
You receive KUB ultrasound report of a 4-year-old child. His height is 100 cm and weight is 22 kg. His serum creatinine is 1 mg/dL.
a. What is his approximate bladder capacity?
b. What is the volume considered to be significant for post void urine?
c. You suspect a renal tract abnormality, what is the investigation of choice to rule out scarring?
d. Calculate his GFR using Schwartz formula.
Answer
- a. Bladder capacity
- b.
(or ; for this 22 kg child) - c.
-DMSA (Dimercaptosuccinic acid) renal scan - d.
VVK19-003
Fractional excretion of sodium. Given below is the serum and urinary electrolyte report of a 6-year-old child:
| Investigation | Value |
|---|---|
| 100 mEq/L | |
| 90 mg/dL | |
| 90 mEq/L | |
| 25 mEq/L | |
| 135 mEq/L | |
| 1 mg/dL | |
| 100 mEq/L | |
| 4 mEq/L |
a. Calculate
b.
c.
d.
e.
f.
Answer
- a.
(or ) - b. Greater
- c. Greater
- d. Less
- e. Less
- f. Less
VVK19-004
Serum osmolality. Attached are serum reports of a 7-year-old child:
a. Calculate his serum osmolality.
b. What is the normal range?
Answer
- a.
(or ) - b. 275–290 mOsm/kg (or 275–295 mOsm/kg)
VVK19-005
Serum
a. What is the anion gap?
b. What is the normal anion gap?
c. What is the likely anion gap in following (normal or increased)?
- i. Diarrhea
- ii. Lactic acidosis
- iii. DKA
- iv. ARF
- v. RTA
- vi. Salicylate poisoning
- vii. Urinary tract diversion
- viii. IEM
- ix. Septic shock
- x. Post hypocapnea
Answer
- a.
- b. 8–16 mEq/L (or 10–14 mEq/L)
- c.
- i. Diarrhea — Normal
- ii. Lactic acidosis — Increased
- iii. DKA — Increased
- iv. ARF — Increased
- v. RTA — Normal
- vi. Salicylate poisoning — Increased
- vii. Urinary tract diversion — Normal
- viii. IEM — Increased
- ix. Septic shock — Increased
- x. Post hypocapnea — Normal
VVK19-006
A 9-month-old male infant is admitted in PICU with bacterial meningitis. His mean BP is 38 mm Hg. His laboratory reports are as follows:
- Serum sodium: 126 mEq/L
- Serum potassium: 4.2 mEq/L
- Urine output: 4.7 mL/kg/h
- Urinary sodium: 151 mEq/L
a. What is the cause of hyponatremia in this child?
b. List 2 investigations which will help in confirming the diagnosis.
c. How will you correct the electrolyte imbalance?
d. List two symptoms of hyponatremia.
Answer
- a. Cerebral salt wasting (CSW)
- b. Serum uric acid, serum vasopressin (ADH) level, central venous pressure / volume status assessment
- c. 3% NaCl (Hypertonic saline) infusion. Treatment consists of restoring intravascular volume with sodium chloride and water, replacing ongoing urinary sodium losses (volume-for-volume), and treating the underlying acute brain injury.
- d. Convulsions/seizures, irritability, altered sensorium/lethargy
VVK19-007
Given below are the reports of a 4-year-old male child admitted with a diagnosis of severe pneumonia. He is neurologically normal and has a urine output of 1.2 mL/kg/hr. His laboratory reports are as follows:
- Serum sodium: 129 mEq/L
- Serum potassium: 4.1 mEq/L
- Urinary sodium: 31 mEq/L
- Urinary potassium: 12 mEq/L
a. What is the most likely condition causing this electrolyte abnormality?
b. List 4 causes other than pneumonia which can lead into this condition.
c. How will you treat this condition?
Answer
- a. SIADH (Syndrome of Inappropriate Antidiuretic Hormone Secretion)
- b. Any 4 of:
-
- Excessive administration of vasopressin in the treatment of central diabetes insipidus
-
- Encephalitis
-
- Brain tumors
-
- Head trauma
-
- Psychiatric disease
-
- Postictal period after generalized seizures
-
- Prolonged nausea
-
- Tuberculous meningitis
-
- AIDS
-
- Hypothalamic-pituitary surgery
-
- Drugs: Oxcarbazepine, carbamazepine, chlorpropamide, vinblastine, vincristine, and tricyclic antidepressants
-
- c. Fluid restriction (restrict fluid intake to 50–75% of maintenance). SIADH is characterized by hyponatremia, inappropriately concentrated urine (>100 mOsm/kg), normal or slightly elevated plasma volume, normal-to-high urine sodium, and low serum uric acid.
VVK19-008
A 3-year-old male child presented in pediatric OPD with a history of 1 episode of abnormal movement 2 hours back. Parents also give history of oliguria and irritability for past 36 hours. He also has a 3-day history of bloody stools which stopped 3 days back. Parents were giving ORS for past 3 days. On examination, he is pale, edematous, has hepatomegaly, and has petechiae all over the body. His HR is 140/min, BP is 100/60 mm Hg. His arterial blood gas shows mild metabolic acidosis.
a. What is the most likely diagnosis?
b. What is the most likely etiology/pathogen involved in the above diagnosis?
c. List two differential diagnoses.
d. List 2 electrolyte abnormalities which can be associated with this diagnosis.
Answer
- a. Hemolytic Uremic Syndrome (HUS)
- b. E. coli O157:H7 (Enterohemorrhagic E. coli / Shiga toxin-producing E. coli) or Shigella dysenteriae type 1
- c. Any 2:
-
- Acute glomerulonephritis (PSGN)
-
- Dyselectrolytemia
-
- Intussusception
-
- Thrombotic thrombocytopenic purpura (TTP) / DIC
-
- d. Hyponatremia, hyperkalemia (or hypernatremia, hypocalcemia, hyperphosphatemia)
VVK19-009
Study the DTPA scan shown below and answer the questions.
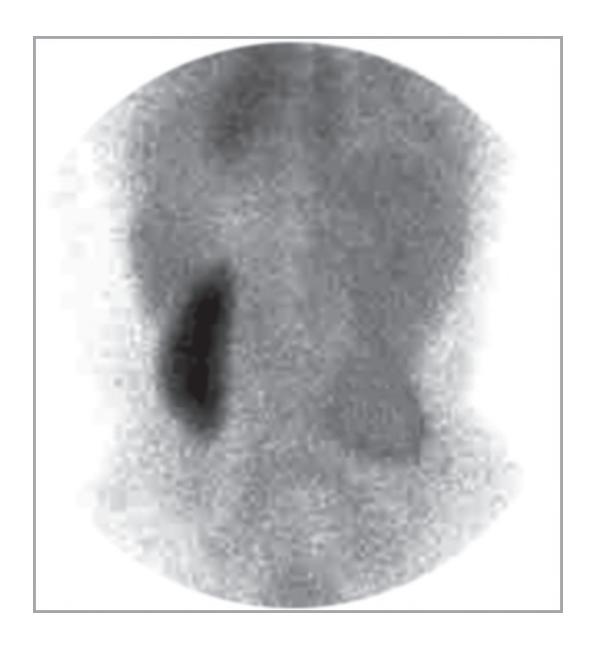
a. What is the diagnosis on this DTPA scan?
b. What do DTPA and DMSA stand for?
Answer
- a. Absent left-sided kidney perfusion / Non-functioning left kidney
- b.
- DTPA:
-labeled Diethylenetriaminepentaacetic acid scan - DMSA: Dimercaptosuccinic acid scan
- DTPA:
VVK19-010
A 12-year-old boy is brought to the clinic with recurrent cramps. On examination, his growth is normal. He is normotensive and has no evidence of rickets. His systemic examination is normal. His laboratory reports are as follows:
- Hb: 12.1 g/dL
- BUN: 8 mg/dL
- Serum creatinine: 0.4 mg/dL
- Serum sodium: 141 mEq/L
- Serum potassium: 2.5 mEq/L
- Serum chloride: 90 mEq/L
- Serum magnesium: 0.5 mmol/L (low)
- Urinary chloride: 35 mEq/L
- Blood gas: pH 7.52,
30 mEq/L
a. What is the most probable diagnosis?
b. What is the mode of inheritance?
c. What is the treatment?
Answer
- a. Gitelman's syndrome
- b. Autosomal recessive
- c. Potassium and magnesium supplements
VVK19-011
Match the following:
| Histology / Glomerular Pathology | Disease |
|---|---|
| a. Diffuse mesangial proliferative | 1. Alport syndrome |
| b. Focal segmental | 2. IgA nephropathy |
| c. With crescents | 3. RPGN |
| d. Foam cells | 4. Poststreptococcal glomerulonephritis |
Answer
- a. Diffuse mesangial proliferative — 4. Poststreptococcal glomerulonephritis (or 2. IgA nephropathy)
- b. Focal segmental — 2. IgA nephropathy (or FSGS)
- c. With crescents — 3. RPGN (Rapidly progressive glomerulonephritis)
- d. Foam cells — 1. Alport syndrome
VVK19-012
A 16-year-old female, known case of SLE presents to pediatric OPD with intermittent hemoptysis and hematuria. On examination, she is noted to be pale and hypertensive. On investigation, her complement levels were normal. Further investigation revealed antibodies to lung and glomerular basement membrane.
a. What is the most likely diagnosis?
b. What is the most likely cause of hemoptysis in this patient?
c. List 2 treatment options.
Answer
- a. Goodpasture disease (Anti-GBM disease)
- b. Pulmonary hemorrhage (diffuse alveolar hemorrhage)
- c.
- Pulsed methylprednisolone
- Immunosuppression (e.g., Cyclophosphamide)
- Plasmapheresis (plasma exchange)
VVK19-013
A 3-year-old female child is reviewed in pediatric OPD for failing to thrive and abdominal pain. Her investigation revealed Hb 10 g/dL, serum sodium of 136 mEq/L, serum potassium of 2.9 mEq/L and metabolic acidosis. Her urinary pH was 6.1. On further evaluation, she is diagnosed to have renal stones.
a. What is the most likely diagnosis including the subtype of the pathology?
b. What is the underlying pathogenesis?
c. What is the treatment?
Answer
- a. Type I (Distal) Renal Tubular Acidosis (RTA)
- b. Impaired distal urinary acidification / defective
ion secretion in the collecting duct - c. Bicarbonate supplementation, potassium replacement, thiazide diuretics
VVK19-014
A 2-year-old female child is reviewed in pediatric OPD for short stature. She also complains of polyuria and polydipsia. Her examination revealed signs of rickets. Her investigation showed serum sodium of 137 mEq/L, serum potassium of 2.8 mEq/L and metabolic acidosis. Her urinary pH was 4.9.
a. What is the most likely diagnosis including the subtype of the pathology?
b. What is the underlying pathogenesis?
c. What is the treatment?
Answer
- a. Type II (Proximal) Renal Tubular Acidosis (RTA)
- b. Impaired proximal tubular
reabsorption - c. High-dose oral bicarbonate supplementation (and potassium supplementation, vitamin D / phosphate if rickets is present)
VVK19-015
Given below is the photograph of an 8-day-old male neonate. He is also diagnosed to have undescended testis and urinary tract abnormality.
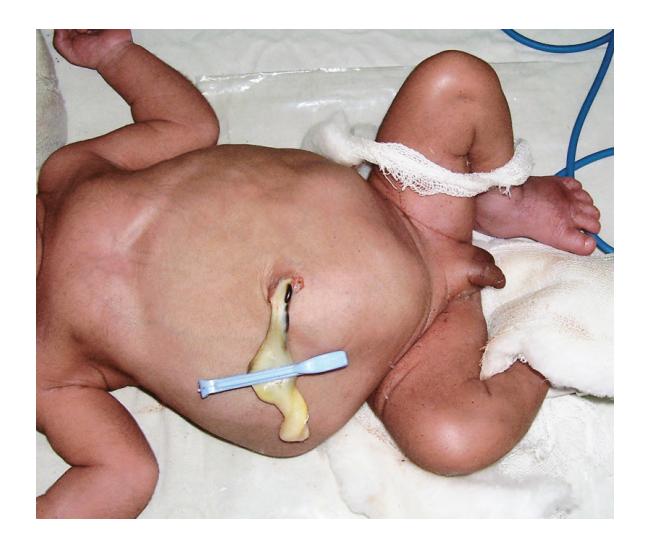
a. What is the diagnosis?
b. What are the associated urinary tract abnormalities with this condition?
c. Give 1 pulmonary complication associated with this condition.
Answer
- a. Prune-Belly syndrome (Eagle-Barrett syndrome / Triad syndrome)
- b. Dilated ureters (megaureter), megalourethra, large hypoplastic bladder, hydronephrosis, vesicoureteral reflux (VUR)
- c. Pulmonary hypoplasia / pneumothorax
VVK19-016
A 4-year-old child with nephrotic syndrome presents with fever, vomiting, severe abdominal pain and abdominal distension. On examination, his HR is 160/min along with shallow and rapid breathing. His blood tests reveal peripheral leucocytosis with a marked predominance of polymorphonuclear cells.
a. What is the diagnosis?
b. How would you confirm the diagnosis?
c. What is the most likely cause/pathogen/organism for the same?
d. What is the immediate treatment?
Answer
- a. Spontaneous bacterial peritonitis (SBP)
- b. Diagnostic ascitic tap: PMN count
(with PMNs ) and ascitic fluid culture - c. Streptococcus pneumoniae (Pneumococci), followed by E. coli
- d. Parenteral antibiotic therapy (e.g., IV cefotaxime / 3rd generation cephalosporin with or without an aminoglycoside)
VVK19-017
A
a. What is your interpretation of the ABG?
b. List 4 clinical conditions in which this ABG finding can be seen.
On further investigation, he was noted to have hypokalemia.
c. List 2 possible diagnoses.
His urine shows hypercalciuria.
d. What is the diagnosis?
e. How do you treat this patient?
Answer
- a. Metabolic alkalosis (uncompensated / partially compensated)
- b. Any 4 of:
- Gastric losses (emesis or nasogastric suction)
- Diuretic use
- Gitelman syndrome
- Bartter syndrome
- Exogenous base/alkali administration
- Autosomal dominant hypoparathyroidism
- Adrenal adenoma or hyperplasia / Primary hyperaldosteronism
- Glucocorticoid-remediable aldosteronism
- Renovascular disease
- Renin-secreting tumor
- Cushing syndrome
- c. Gitelman syndrome, Bartter syndrome
- d. Bartter syndrome (characterized by hypokalemic metabolic alkalosis and hypercalciuria)
- e. Potassium supplementation, adequate hydration, sodium chloride supplementation, nutritional support, and indomethacin / NSAIDs / potassium-sparing diuretics (spironolactone / amiloride).
VVK19-018
A 3-year-old female presented to pediatric OPD with complaint of irritability and lethargy. On examination, she appears pale. On further questioning mother gave history of URTI 1 week back for which she consulted a local physician who conservatively treated it as viral URI. She also gave history of decreased urine output. After a week of the above illness, she became irritable and lethargic. Child's blood investigations revealed a BUN of 81 mg/dL and serum creatinine of 4.2 mg/dL. Her blood gas shows pH of 7.18 and serum K of 5.6 mmol/L with tall T waves in the ECG. Her platelet count is 85,000/mm³.
a. What is the diagnosis?
b. What are the possible findings on the peripheral smear of this child?
c. What is the most common organism associated with this disease?
d. List 2 indications of dialysis in this child.
Answer
- a. Hemolytic Uremic Syndrome (HUS) — atypical presentation (more commonly presents following gastroenteritis, but occasionally can follow URI/pneumococcal infection).
- b. Microangiopathic hemolytic anemia with schistocytes (fragmented RBCs, burr cells, helmet cells), thrombocytopenia, and leukocytosis.
- c. E. coli O157:H7 (~70–80% of D+ HUS) / Streptococcus pneumoniae (for D- / atypical post-URI HUS).
- d. Indications for dialysis in this child:
- Severe refractory hyperkalemia (
with ECG changes) - Severe metabolic acidosis (
) refractory to medical management - Uremic encephalopathy / seizures / fluid overload / severe oliguria-anuria
- Severe refractory hyperkalemia (
VVK19-019
Given below is the picture of a 6-year-old boy presenting in OPD with complaint of severe abdominal pain of 1 day duration. On examination, he is noted to have similar rash over buttocks and thighs. His CBC and clotting profile is normal.
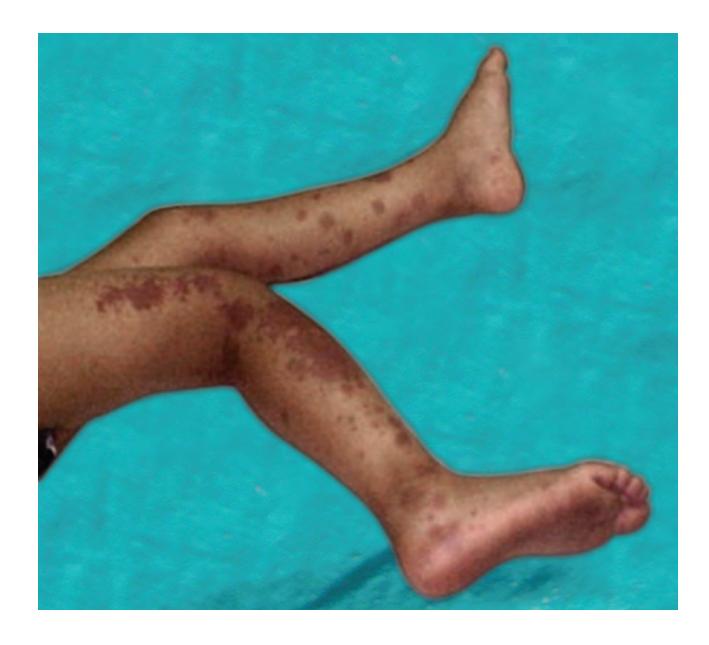
a. What is the most likely diagnosis?
b. What is the prognosis?
c. What are the factors associated with worst prognosis?
d. List 2 possible long-term complications.
Answer
- a. Henoch-Schönlein purpura (IgA vasculitis)
- b. Generally favorable (97–98% resolve completely)
- c. Factors associated with worse renal prognosis:
- Acute nephritic and/or nephrotic syndrome at presentation
- Severe renal involvement (crescents on
of glomeruli on renal biopsy) - Persistent heavy proteinuria
- Older age at onset
- d. Any 2:
- Chronic renal failure / chronic kidney disease
- Persistent hypertension
- Microscopic or gross hematuria / persistent proteinuria
- Pregnancy-induced hypertension later in life
VVK19-020
What is the dietary requirement for a child with acute renal failure in terms of:
a. Calorie requirement.
b. Protein requirement.
c. Sodium requirement.
d. Potassium intake.
e. Phosphorus.
Answer
- a. Calories: Maximized — at least the daily requirement of 100 kcal/kg/day (or age-appropriate requirement).
- b. Protein: Restrict moderately (0.6–1.0 g/kg/day of high biological value protein to minimize azotemia).
- c. Sodium: Restrict, no added salt (1–2 mEq/kg/day).
- d. Potassium: Restrict, avoid potassium-containing food (<1 mEq/kg/day or eliminate during oliguria).
- e. Phosphorus: Restrict (avoid dairy and high-phosphate foods, use phosphate binders).