THG23-001
An 8-year-old male child presents with episodic headache for the past 6 months. The headache frequency is approximately three episodes per month and each episode lasts for 30 minutes to 2 hours. The headache is associated with nausea, photophobia, phonophobia, and occasional vomiting during the episodes. The headache is prominent usually in the evening and it is relieved with rest. There is family history of intermittent headache in mother.
a. What is the diagnosis?
b. How do you objectively assess the severity of headache in this condition?
c. How will you treat the headache episodes?
d. What investigation would you like to do to confirm the diagnosis?
Answer
- a. Migraine without aura
- b. PedMIDAS score (Pediatric Migraine Disability Assessment Score)
- c. Lifestyle modifications (regular sleep, hydration, trigger avoidance) and acute abortive analgesics (Paracetamol / Ibuprofen, or Triptans like sumatriptan/zolmitriptan)
- d. No investigation indicated (diagnosis is clinical; neuroimaging is not required in typical migraine with normal neurological exam).
THG23-002
A 10-year-old obese female child presented with intermittent headache for the past 6 months. The headache episode was also associated with often blurring of vision and vomiting. There was no photophobia or phonophobia. The headache was aggravated in the morning once the child woke up. There was no family history of headache. Fundus evaluation revealed papilledema bilaterally. Magnetic resonance imaging (MRI) brain with magnetic resonance venography (MRV) was normal.
a. What is the diagnosis?
b. How would you confirm the diagnosis?
c. How will you treat this condition?
Answer
- a. Idiopathic intracranial hypertension (Pseudotumor cerebri)
- b. Lumbar puncture with CSF manometry to measure CSF opening pressure (>25–28 cm H₂O with normal CSF composition)
- c. Therapeutic lumbar puncture, oral Acetazolamide (carbonic anhydrase inhibitor), weight reduction, and surgical options (optic nerve sheath fenestration / lumboperitoneal shunt) if vision is threatened.
THG23-003
A 6-year-old female child presented with swaying while walking from 2 years of age. The child was having intention tremors and unsteady gait and it has been gradually progressive. The child was noted to have oculomotor apraxia on examination. The child also has history of frequent respiratory tract infections.
a. What is the likely diagnosis?
b. What specific general examination finding can help you diagnose this condition?
c. What biochemical maker in serum is elevated in this condition?
d. What is the mode of inheritance of this condition?
Answer
- a. Ataxia–telangiectasia (Louis–Bar syndrome)
- b. Oculocutaneous telangiectasia (especially over bulbar conjunctiva, bridge of nose, pinnae, and extensor surfaces of extremities)
- c. Serum alpha-fetoprotein (AFP)
- d. Autosomal recessive (ATM gene mutation)
THG23-004
A 7-year-old male child presented with failure to thrive, anemia, and progressive swaying, unsteady gait, and intention tremors. The child also has frequent loose stools and bulky sticky stools.
a. What is the likely diagnosis?
b. What hematological abnormality would you expect?
c. What biochemical investigation will give you a clue toward the diagnosis?
d. What ophthalmological abnormality would you expect?
e. Mention the compound used in treatment of this condition?
Answer
- a. Abetalipoproteinemia (Bassen–Kornzweig syndrome)
- b. Acanthocytes (burr cells/spur cells) on peripheral blood smear
- c. Fasting lipid profile (markedly reduced/undetectable serum cholesterol, triglycerides, and absent ApoB-containing lipoproteins)
- d. Retinitis pigmentosa (atypical pigmentary retinopathy)
- e. High-dose fat-soluble vitamins (particularly Vitamin E / alpha-tocopherol) along with Vitamin A, D, and K
THG23-005
A 12-year-old boy presented with unsteady gait, frequent falls, and intention tremors and it was gradually progressive over the past 6 months. The child had pyramidal signs but bilateral knee and ankle jerks were sluggish and bilateral plantar was extensor. Echo done in view of exertional dyspnea revealed evidence of cardiomyopathy.
a. What is the likely diagnosis?
b. What is the mode of inheritance?
c. What triplet repeat disease is implicated in this condition?
d. Mention the skeletal abnormalities that occur in this condition.
e. What endocrine abnormality has to be screened in this condition?
f. What is the most common cause of mortality in this disorder?
Answer
- a. Friedreich's ataxia
- b. Autosomal recessive (FXN gene mutation encoding frataxin)
- c. GAA trinucleotide repeat expansion in intron 1 of FXN gene
- d. Pes cavus, hammer toes, and progressive kyphoscoliosis
- e. Diabetes mellitus / impaired glucose tolerance
- f. Hypertrophic cardiomyopathy leading to arrhythmias and congestive cardiac failure
THG23-006
A 9-year-old female child presented with abnormal involuntary jerky dance like movements of limbs and they are absent during sleep. The child was noted to have emotional lability. Investigations revealed elevated C-reactive protein (CRP), erythrocyte sedimentation rate (ESR), and significant ASO (antistreptolysin O) titer.
a. What is the diagnosis?
b. What is the triad of this condition?
c. What are the signs you would like to elicit?
d. What investigations would you do?
e. How would you treat?
Answer
- a. Sydenham's chorea (Chorea minor / St. Vitus dance)
- b. Triad: Chorea, hypotonia, and emotional lability / behavioral changes
- c. Pronator sign, Darting / Jack-in-the-box tongue (trombone tongue), milkmaid's grip, and spooning of hands
- d. ASO titer, Anti-DNase B, ESR, CRP, throat swab culture, ECG, and 2D-Echocardiography (to rule out carditis)
- e. Long-term secondary penicillin prophylaxis (Benzathine penicillin G every 3–4 weeks); symptomatic control with Sodium valproate, Carbamazepine, or Haloperidol; oral corticosteroids for severe/refractory chorea.
THG23-007
A 12-year-old female child presented with handwriting change and gradually worsening behavioral change over the past 6 months associated with intermittent abnormal twisting posture of limbs and rapid involuntary jerky dance like movements of limbs.
a. What is the likely diagnosis?
b. What finding in ophthalmological evaluation would help in clinching the diagnosis?
c. What is the mode of inheritance?
d. What is the gene implicated in this condition?
e. What are the expected findings in MRI brain?
f. What investigations would you do?
g. How would you treat the primary illness?
Answer
- a. Neuro-Wilson disease (Hepatolenticular degeneration)
- b. Kayser–Fleischer (KF) ring on slit-lamp biomicroscopy
- c. Autosomal recessive
- d. ATP7B gene (chromosome 13q14)
- e. Symmetrical T2 hyperintensities in lentiform nuclei (putamen, globus pallidus), caudate, and brainstem; "Face of the giant panda" sign in midbrain.
- f. Serum ceruloplasmin (<20 mg/dL), 24-hour urinary copper excretion (>100 µg/day), liver function tests, and ATP7B genetic mutation analysis.
- g. Copper chelators (D-penicillamine or Trientine), oral Zinc salts (to block intestinal absorption), and low-copper diet.
THG23-008
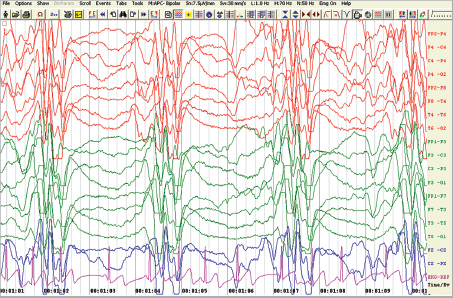
An 8-year-old male child with gradually worsening behavioral problems and cognitive decline for past 5 months. The child has frequent fall due to sudden jerks for the past 3 months. The child is currently admitted with generalized tonic–clonic seizure (GTCS). Electroencephalogram (EEG) was done and it is given in image below.
a. What is your provisional diagnosis?
b. What specific past history can give you a clue for diagnosis?
c. What investigations would you send to diagnose this condition?
d. What does the EEG reveal?
e. How would you treat?
Answer
- a. Subacute sclerosing panencephalitis (SSPE)
- b. History of primary measles infection at an early age (<2 years)
- c. CSF and serum anti-measles IgG antibody titers (elevated with high CSF:serum ratio), EEG, and MRI brain.
- d. Periodic, generalized, synchronous, high-voltage slow-wave complexes (Radermecker complexes) recurring every 4–10 seconds.
- e. No curative treatment; supportive therapy, antiseizure medications, and experimental antiviral/immunomodulatory agents (Oral Isoprinosine/Inosiplex and intrathecal/intraventricular Interferon-alpha).
THG23-009
A 7-year-old female child presented with gradually progressive oromandibular and limb dystonia from 4 years of age. The child is now nonambulatory. The child does not have any myoclonic jerks or any seizures. Fundus examination revealed evidence of pigmentary retinopathy. MRI brain helped in clinching the diagnosis.
a. What is the most likely provisional diagnosis?
b. What is the gene implicated in the condition?
c. What is the mode of inheritance?
d. What is the expected neuroimaging finding which may have helped in clinching the diagnosis?
e. How would you confirm the diagnosis?
Answer
- a. Pantothenate kinase-associated neurodegeneration (PKAN / NBIA type 1)
- b. PANK2 gene
- c. Autosomal recessive
- d. "Eye-of-the-tiger" sign on T2-weighted MRI (central T2 hyperintensity due to gliosis surrounded by hypointense rim of iron deposition in the globus pallidus).
- e. Genetic testing (PANK2 gene mutation analysis by next-generation sequencing).
THG23-010
A 10-month-old with prior normal development presented with afebrile encephalopathy for 2 days preceded by two episodes of vomiting and running nose for 1 days. The child was noted to have frequent dystonic posturing during the admission. MRI brain revealed symmetrical basal ganglia and brainstem T2 hyperintensities with diffusion restriction. Magnetic resonance spectroscopy (MRS) which was done along with MRI brain gave a further etiological clue.
a. What is the most likely provisional diagnosis?
b. What is the expected MRS finding which has given the etiological clue?
c. How would you confirm the diagnosis?
d. How would you treat?
Answer
- a. Leigh syndrome (Subacute necrotizing encephalomyelopathy)
- b. Double inverted lactate peak at 1.33 ppm (on intermediate/long TE MRS)
- c. Genetic testing (nuclear DNA and mitochondrial DNA sequencing / whole exome sequencing) and elevated blood/CSF lactate.
- d. Mitochondrial cocktail (Thiamine, Riboflavin, Coenzyme Q10, L-carnitine, Biotin), management of dystonia (trihexyphenidyl), and supportive physiotherapy.
THG23-011
A 2-year-old male child with background of developmental delay born to third-degree consanguineous parents presented with seizures and encephalopathy. Perinatal history was uneventful. The child was noted to have alopecia, oral candidiasis, and seborrheic dermatitis. There was history of elder sibling death at 5 months of age with refractory seizures. Retroviral serology was negative.
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What investigations would you do in confirming the diagnosis?
d. How would you treat?
e. What is the possible risk of recurrence in the next pregnancy?
Answer
- a. Biotinidase deficiency
- b. Autosomal recessive
- c. Quantitative serum biotinidase enzyme activity assay and BTD gene mutation analysis
- d. Oral pharmacological Biotin supplementation (5–20 mg/day lifelong)
- e. 25% recurrence risk in each subsequent pregnancy
THG23-012
A 5-year-old child was brought with history of getting up in sleep followed by excessive salivation followed by gurgling sounds, then clonic jerking of right side of the body followed by a brief generalized tonic–clonic seizure. After regaining consciousness, he was not able to speak for few minutes.
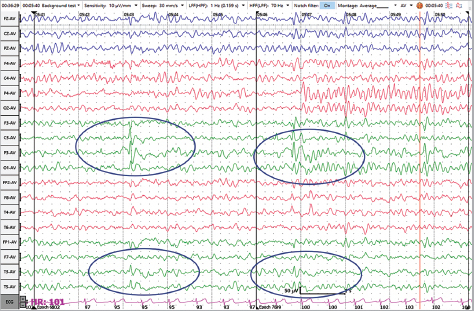
EEG 1 (Awake state)
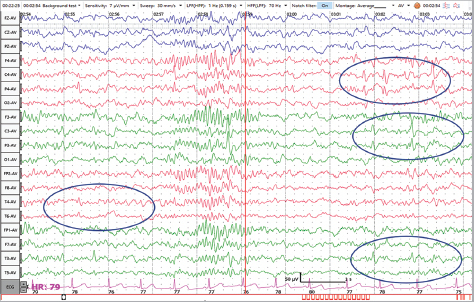
EEG 2 (Sleep state)
a. What is the diagnosis?
b. What does EEG1 (as shown in image) show?
c. What does EEG2 (as shown in image) show?
d. What type of epilepsy is it?
e. What is the treatment for this child?
f. What are the drugs used in this condition?
Answer
- a. Self-limiting epilepsy with centrotemporal spikes (SeLECTS) / Benign childhood epilepsy with centrotemporal spikes (BECTS / Benign Rolandic Epilepsy)
- b. High-voltage sharp spike-and-wave discharges localized to the centrotemporal regions (predominantly unilateral) during awake state.
- c. Markedly increased frequency, amplitude, and bilateral generalization/activation of centrotemporal spike-wave complexes during sleep.
- d. Focal epilepsy (benign / self-limiting pediatric focal epilepsy)
- e. Parental reassurance regarding benign nature and spontaneous remission by adolescence; home seizure management counseling.
- f. Levetiracetam, Oxcarbazepine, Carbamazepine, or Sodium valproate (if antiepileptic therapy is indicated due to frequent nocturnal events).
THG23-013
A 6-year-old boy brought by parents after teacher complained episodes of staring in the classroom.
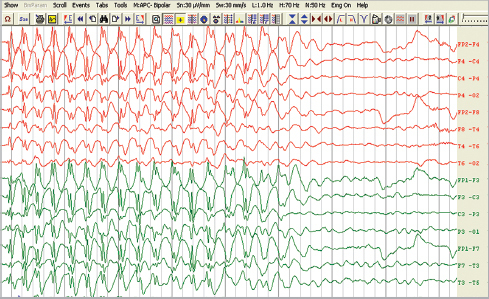
a. What does the EEG (shown in image) show?
b. What is the diagnosis?
c. What are types?
d. If this type of seizure occurs in toddler age group, which disease has to be ruled out?
e. What are the drugs used to treat this condition?
f. What are the drugs avoided in this condition?
g. Which is the bedside provocative test to aid in diagnosis?
Answer
- a. Generalized, synchronous, symmetrical 3 Hz spike-and-slow-wave discharges on a normal background.
- b. Childhood absence epilepsy (Pyknolepsy)
- c. Types of absence seizures: Typical absence, atypical absence, and juvenile absence.
- d. Glucose transporter 1 (GLUT1) deficiency syndrome
- e. Ethosuximide (first-line), Sodium valproate, and Lamotrigine
- f. Sodium channel blockers (Carbamazepine, Oxcarbazepine, Phenytoin, Vigabatrin, and Tiagabine—may aggravate absence seizures).
- g. Hyperventilation (for 3 minutes) or intermittent photic stimulation
THG23-014
A 9-month-old infant brought by mother with multiple episodes of sudden forward bending of body, arms, and legs lasting for 1 per 2 seconds, followed by a pause of 5–10 seconds followed by similar episode in clusters. Identify the EEG given here.
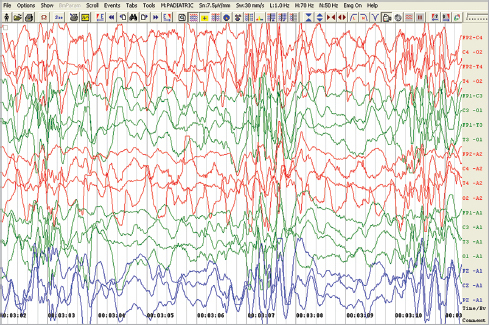
a. Identify the EEG (as shown in image) abnormality.
b. What is the diagnosis? What are its types?
c. What is the treatment?
d. What is the clinical manifestation?
Answer
- a. Hypsarrhythmia (chaotic, high-voltage, disorganized background slowing with multifocal sharp waves and spikes)
- b. Diagnosis: West syndrome (Infantile epileptic spasms syndrome)
- Types: Etiological classification—Structural, genetic, metabolic, or unknown (previously symptomatic, cryptogenic, idiopathic).
- c. Hormonal therapy (Adrenocorticotropic hormone [ACTH] or oral high-dose Prednisolone); Vigabatrin (first-line if associated with Tuberous Sclerosis Complex).
- d. Epileptic spasms (flexor, extensor, or mixed lightning spasms occurring in clusters on awakening), developmental arrest/regression, and hypsarrhythmia.
THG23-015
A 3-year-old male child presented with status epilepticus. The child has cognitive issues and behavioral problems. The child had his first seizure which was fever provoked at 14 weeks of life following vaccination. Subsequently the child used to have fever provoked focal seizures every 2 months followed by GTCS after 1.5 years of age. The child has seizures once in every 2 months and started to have unprovoked seizures after 2 years of age along with fever provoked seizures intermittently. The child has intermittent brief blank episodes which last few seconds. Perinatal history is uneventful. MRI brain is normal.
a. What is the most likely diagnosis?
b. What is the most common gene implicated in this condition?
c. What is the most common mode of inheritance?
d. What antiseizure medications are used to control seizures in this condition?
e. What antiseizure medications are to be avoided in this condition?
Answer
- a. Dravet syndrome (Severe myoclonic epilepsy of infancy - SMEI)
- b. SCN1A gene (voltage-gated sodium channel alpha subunit)
- c. Autosomal dominant (mostly de novo mutations in >90%)
- d. Clobazam, Sodium valproate, Stiripentol, Cannabidiol, Fenfluramine, Topiramate, and Levetiracetam
- e. Sodium channel blockers (Phenytoin, Carbamazepine, Oxcarbazepine, Lamotrigine, and Vigabatrin)
THG23-016
A 4-year-old child presented with developmental delay, multiple seizure types in the form of jerks, vacant stares, and recurrent head drops and falls. EEG was done.
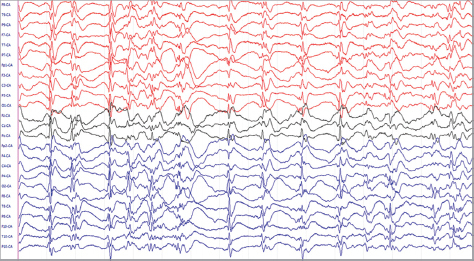
a. What does the EEG show in above image?
b. What is the diagnosis?
c. What is the triad of this condition?
Answer
- a. Generalized slow spike-and-wave discharges (<2.5 Hz, typically 1.5–2 Hz) on a slowed, disorganized background.
- b. Lennox–Gastaut syndrome (LGS)
- c. Triad:
- i. Multiple intractable seizure types (atonic/drop attacks, tonic seizures, atypical absence)
- ii. Cognitive impairment / neurodevelopmental delay
- iii. Characteristic EEG showing diffuse slow spike-and-wave discharges (<2.5 Hz) and paroxysmal fast activity (10–20 Hz) in sleep
THG23-017
A 9-month-old female child with macrocephaly and motor predominant delay started to have predominant motor neuroregression following a febrile illness along with significant dystonia. The child has refractory dystonia, retrocollis, and opisthotonic posturing. The child is born to second-degree consanguineously married parents.
a. What is the likely diagnosis?
b. What is the classical neuroimaging finding which you would expect in this condition?
c. How will you confirm the diagnosis?
d. How will you treat?
Answer
- a. Glutaric aciduria type 1 (GA-1 / Glutaryl-CoA dehydrogenase deficiency)
- b. "Batwing" appearance / widened sylvian fissures with frontotemporal atrophy, open opercula, bilateral striatal (putamen/caudate) T2 hyperintensities, and subdural hygromas/hematomas.
- c. Tandem mass spectrometry (TMS: elevated glutarylcarnitine C5DC), urine GC-MS (elevated glutaric acid and 3-hydroxyglutaric acid), and GCDH gene sequencing.
- d. Low-lysine diet, L-carnitine supplementation, emergency sick-day high-glucose/insulin protocol during catabolism, and antidystonia medications.
THG23-018
A 9-year-old girl with decreased scholastic performance presented with seizures. The picture below displays what you have noticed in general examination.
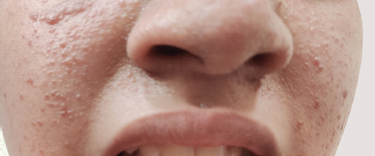
a. What is the likely diagnosis?
b. What is the mode of inheritance?
c. What does the above image show?
d. Which skin finding can be present from birth?
e. Mention two ophthalmological manifestations of this condition.
f. Mention two renal manifestations of this condition.
g. How many major and minor criteria are required for diagnosis?
h. What are the neuroimaging findings in this condition?
i. What drug is used to treat subependymal giant cell astrocytoma (SEGA)?
Answer
- a. Tuberous Sclerosis Complex (TSC / Bourneville disease)
- b. Autosomal dominant (TSC1 on chr 9q34, TSC2 on chr 16p13)
- c. Facial angiofibromas (adenoma sebaceum) in a butterfly malar distribution
- d. Hypomelanotic macules (Ash-leaf spots / confetti macules)
- e. Retinal hamartomas (mulberry lesions) and retinal achromatic patches
- f. Renal angiomyolipomas and renal cysts
- g. Definite diagnosis requires 2 major criteria OR 1 major criterion +
minor criteria. - h. Cortical tubers, subependymal nodules (SEN), and subependymal giant cell astrocytomas (SEGA)
- i. mTOR inhibitors: Everolimus / Sirolimus
THG23-019
A 7-year-old boy presented with seizures. You notice this during your general examination which is displayed in the image. The father also has similar skin findings.
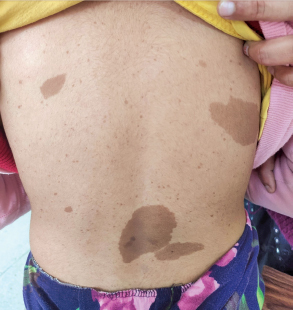
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What do you observe in the above image? When do you consider it significant?
d. What ophthalmological finding would you expect?
e. Name two skeletal manifestations of this condition.
f. Name two endocrine manifestations of this condition.
g. How many criteria need to be present to diagnose this condition?
Answer
- a. Neurofibromatosis type 1 (NF1 / von Recklinghausen disease)
- b. Autosomal dominant (NF1 gene on chromosome 17q11.2)
- c. Café-au-lait macules (CALMs); significant when
CALMs with diameter in prepubertal or in postpubertal individuals. - d. Lisch nodules (iris hamartomas) and optic pathway glioma
- e. Sphenoid wing dysplasia, pseudoarthrosis (anterolateral tibial bowing), and scoliosis
- f. Precocious puberty (due to hypothalamic optic pathway gliomas) and pheochromocytoma
- g. At least 2 out of the 7 standard NIH diagnostic criteria
THG23-020
A 2-year-old female child with background history of developmental delay and cognitive issues presented with status epilepticus. The image below displays what you have noticed in general examination.
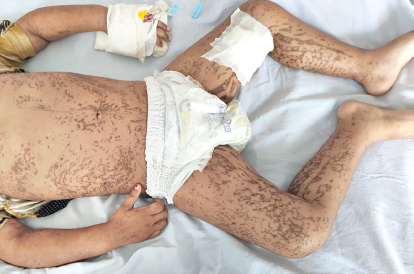
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What are the neurological manifestations?
d. What are the non-neurological manifestations?
Answer
- a. Incontinentia pigmenti (Bloch–Sulzberger syndrome)
- b. X-linked dominant (IKBKG / NEMO gene mutation; lethal in most hemizygous males)
- c. Seizures, developmental delay / intellectual disability, spastic hemiplegia/paresis, and microcephaly
- d. Whorled/swirling hyperpigmentation along Blaschko's lines, hypodontia/pegged teeth, cicatricial alopecia, retinal neovascularization / detachment, and dystrophic nails.
THG23-021
A 4-year-old child presented with right focal seizure. Child was noted to have port-wine stain on the left side of the face.
a. What is the most likely diagnosis?
b. What is the triad?
c. Where do you usually find the port-wine stain on the face?
d. How do you confirm the diagnosis?
e. What finding do you expect in the computed tomography (CT) brain?
f. Why ophthalmological evaluation is required in this condition?
g. Mention any two neurological manifestations of this condition other than seizure.
Answer
- a. Sturge–Weber syndrome (Encephalotrigeminal angiomatosis)
- b. Triad: Facial port-wine stain (capillary malformation), ipsilateral leptomeningeal angiomatosis, and glaucoma / ocular vascular malformations.
- c. Distribution of the ophthalmic (
) division of the trigeminal nerve (upper eyelid and forehead) - d. Contrast-enhanced MRI brain with gadolinium (demonstrating leptomeningeal angioma and choroid plexus enlargement)
- e. "Tram-track" cortical gyriform calcifications with ipsilateral cerebral hemiatrophy
- f. To screen for and detect congenital/early glaucoma and choroidal hemangioma
- g. Contralateral hemiparesis/stroke-like episodes, cognitive impairment, and migraine-like headaches
THG23-022
A 3-week-old neonate presented with encephalopathy, refractory seizures since day 8 of life and baby is hypotonic. The baby has intractable hiccups and myoclonic jerks. MRI brain done revealed dysgenesis of corpus callosum. EEG done revealed suppression burst pattern.
a. What is the most likely diagnosis?
b. What investigation would help you in identifying this disorder and what is the cut-off?
c. What investigation can confirm the diagnosis?
d. What is the mode of inheritance?
e. What antiseizure medication must be avoided when you suspect this condition?
Answer
- a. Nonketotic hyperglycinemia (NKH / Neonatal glycine encephalopathy)
- b. Simultaneous CSF and plasma glycine levels; CSF:plasma glycine ratio
(normal ) is diagnostic. - c. Genetic testing (GLDC, AMT, or GCSH gene mutations)
- d. Autosomal recessive
- e. Sodium valproate (inhibits glycine cleavage system and worsens hyperammonemia/hyperglycinemia)
THG23-023
A 2-year-old female child presented with autistic features and microcephaly. The child had normal development till 8 months of age. Gradually after that the child started to develop cognitive regression, autistic features, decline in head circumference, loss of purposeful hand movements, and an abnormal gait.
a. What is the most likely diagnosis?
b. What is the most common gene implicated in this condition?
c. What is the most common mode of inheritance?
d. What is the common cause of death?
Answer
- a. Rett syndrome
- b. MECP2 gene (Methyl-CpG-binding protein 2)
- c. X-linked dominant (primarily in females; usually de novo)
- d. Sudden unexpected death in epilepsy (SUDEP) / cardiac arrhythmias (prolonged QTc) / respiratory complications (aspiration pneumonia)
THG23-024
A 2-year-old female child presented with cognitive regression and multiple episodes of seizures and repeated myoclonic jerks from the age of 8 months. The child was also noted to have visual disturbance. Fundus done revealed retinal pigmentary change and retinal artery attenuation. MRI brain done revealed diffuse cerebral atrophy and cerebellar atrophy.
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What skin biopsy finding would you expect?
d. What are the two investigations which can help to confirm the diagnosis?
Answer
- a. Neuronal ceroid lipofuscinosis (NCL / Batten disease - infantile/late-infantile form)
- b. Autosomal recessive
- c. Electron microscopy showing autofluorescent lipopigment inclusion bodies (granular osmiophilic deposits - GRODs, curvilinear bodies, or fingerprint profiles)
- d. Lysosomal enzyme assays (PPT1 / TPP1 activity) and next-generation genetic sequencing (CLN gene panel)
THG23-025
A 3-year-old male child with normal development till 15 months of age started to have gradual motor neuroregression, stopped walking, standing, and sitting and became nonambulatory by 2.5 years of age. The child was noted to have spasticity and pyramidal signs. However, the ankle jerk was diminished. The child did not have any seizures. MRI brain was done and it is given below.
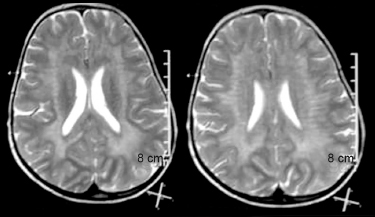
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What is the enzyme deficient?
d. What does the MRI brain image reveal?
e. What could be the reason for the possible diminished ankle jerk?
f. What is the recurrent risk in next pregnancy?
Answer
- a. Metachromatic leukodystrophy (MLD - late infantile form)
- b. Autosomal recessive (ARSA gene)
- c. Arylsulfatase A (cerebroside sulfatase)
- d. Symmetrical, confluent periventricular white matter T2 hyperintensities sparing subcortical U-fibers, with a characteristic "tigroid" or leopard-skin radial striping pattern.
- e. Associated demyelinating peripheral sensorimotor neuropathy (MLD is a leukodystrophy with peripheral nerve involvement).
- f. 25% recurrence risk in each subsequent pregnancy
THG23-026
A 16-month-old male child presented with developmental stagnation since 7 months of age and cognitive regression since 10 months of age. Child was tremulous and was noted to have pallor and hypopigmented sparse hair. Child is predominantly on breastfeeds.
a. What is the most likely diagnosis?
b. What general examination in limbs would you specifically look for (other than what is mentioned in the question)?
c. What hematological abnormality would you expect?
d. How would you treat?
Answer
- a. Infantile Tremor Syndrome (ITS) secondary to nutritional Vitamin B₁₂ deficiency
- b. Knuckle hyperpigmentation (hyperpigmentation over dorsal aspect of interphalangeal joints)
- c. Macrocytic megaloblastic anemia (elevated MCV), hypersegmented neutrophils, and pancytopenia on peripheral blood smear.
- d. Intramuscular Vitamin B₁₂ (Cyanocobalamin / Methylcobalamin), nutritional rehabilitation, maternal Vitamin B₁₂ supplementation, and iron/folate support.
THG23-027
A 7-year-old male child presented with behavioral disturbance for past 8 months, progressive gait abnormality, and increasing stiffness along with vision and hearing disturbance. The child is currently bedbound with significant spasticity, pyramidal signs, unable to speak, on tube feeds, and lost bladder control. MRI brain done is given further.
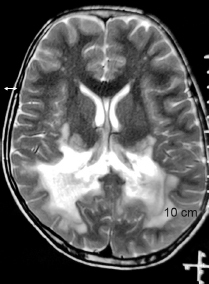
a. What is the likely diagnosis?
b. What is the mode of inheritance?
c. What is the gene implicated in this condition?
d. What general examination finding in skin should one specifically look for?
e. What is the endocrine manifestation of the disease which one should screen for?
Answer
- a. X-linked adrenoleukodystrophy (X-ALD)
- b. X-linked recessive
- c. ABCD1 gene (ATP-binding cassette transporter subfamily D member 1)
- d. Cutaneous hyperpigmentation (generalized bronzing, especially in palmar creases and pressure points due to elevated ACTH)
- e. Primary adrenal insufficiency (Addison disease / elevated ACTH with low cortisol)
THG23-028
An 8-month-old male infant presented with delayed head control, epileptic spasms from 5 months of age, and vision impairment. The child was noted to have central hypotonia and macrocephaly. Fundus revealed optic atrophy. MRI brain was done and the image is given below.
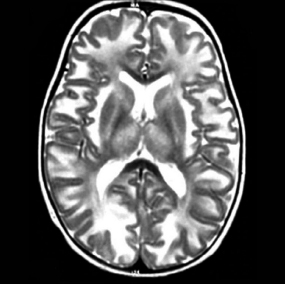
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What is the enzyme deficient?
d. What is the classical pattern of white matter involvement seen in MRI brain?
e. What is the MRI sequence which is displayed in the image?
f. What classical finding is expected in the MRS?
Answer
- a. Canavan disease (Spongy degeneration of central nervous system)
- b. Autosomal recessive (ASPA gene)
- c. Aspartoacylase
- d. Diffuse, symmetrical cerebral white matter T2 hyperintensity with prominent early involvement of subcortical U-fibers and deep gray nuclei.
- e. Axial T2-weighted MRI
- f. Markedly elevated giant N-acetylaspartate (NAA) peak at 2.02 ppm on MR spectroscopy
THG23-029
A 15-month-old male child presented with motor and cognitive neuroregression noted since 6 months of age. The child was also noted to have seizures and vision regression since 8 months of age along with gradually increasing dystonia. The child was noted to have exaggerated startle to noise and was noted to have mild coarseness. There was no organomegaly.
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What fundus examination finding would you expect?
d. How will you confirm the diagnosis?
Answer
- a. Tay–Sachs disease (
gangliosidosis) - b. Autosomal recessive (HEXA gene mutation)
- c. Cherry-red spot at the macula (with surrounding pale retinal ganglion cells) and optic atrophy
- d. Serum/leukocyte Beta-hexosaminidase A enzyme assay and HEXA gene sequencing
THG23-030
A 9-month-old male child presented with delayed head control, neuroregression, opisthotonic posturing, strabismus, and massive splenomegaly.
a. What is the most likely diagnosis?
b. What is the mode of inheritance?
c. What enzyme is deficient in this condition?
d. What are the three types this disorder is classified into?
e. How will you confirm the diagnosis?
Answer
- a. Gaucher disease Type 2 (Acute infantile neuronopathic Gaucher disease)
- b. Autosomal recessive (GBA gene mutation)
- c. Beta-glucocerebrosidase (acid
-glucosidase) - d. Types:
- Type 1: Non-neuronopathic (chronic visceral form)
- Type 2: Acute infantile neuronopathic form
- Type 3: Chronic / subacute juvenile neuronopathic form
- e. Leukocyte
-glucocerebrosidase enzyme assay, elevated chitotriosidase/glucosylsphingosine, and GBA1 gene mutation analysis.
THG23-031
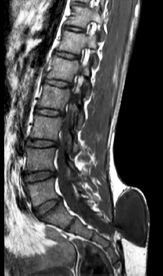
Above image is the sagittal section of MRI of the spine showing a neural tube defect:
a. Spot the abnormality (diagnosis).
b. List a few risk factors for development of this condition.
c. What are the indications and timing of surgery?
d. List two long-term complications (neurologic and non-neurologic).
e. What is Chiari crisis? Enlist symptoms of this condition and its management.
Answer
- a. Lumbosacral myelomeningocele with Chiari II malformation
- b. Maternal periconceptional folic acid deficiency, maternal diabetes mellitus, antiepileptic exposure (valproate, carbamazepine), maternal hyperthermia, and family history of neural tube defects.
- c. Surgical closure within 24–48 hours of birth (immediate closure if leaking CSF / ruptured placode) to prevent meningitis and preserve neural function; antenatal fetal repair between 19–26 weeks gestation in selected cases.
- d. Long-term complications:
- Neurologic: Hydrocephalus, neurogenic bladder/bowel, lower limb paraparesis/contractures, tethered cord syndrome.
- Non-neurologic: Kyphoscoliosis, clubfoot (talipes equinovarus), hip dislocation, and chronic pressure ulcers.
- e. Chiari Crisis: Acute brainstem compression due to downward herniation of cerebellar vermis and medulla in Chiari II malformation.
- Symptoms: Inspiratory stridor, vocal cord paralysis, central apnea, dysphagia/feeding difficulty, weak cry, and spastic quadriparesis.
- Management: Emergent VP shunt revision (if hydrocephalus/shunt malfunction) or posterior fossa decompression surgery.
THG23-032
A 10-year-old boy comes with acute onset right-sided weakness with aphasia while he was playing on the ground, he also reports two similar such self-improving episodes in the last month.
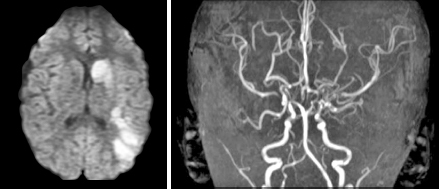
a. Identify the MRI sequences in above image.
b. What is the most likely diagnosis?
c. What is the radiological sign in angiography?
d. What are the conditions associated?
e. What are the treatment options?
Answer
- a. Diffusion-weighted MRI (DWI) showing acute left basal ganglia/cerebral infarction, and Magnetic Resonance Angiography (MRA) showing supraclinoid internal carotid artery occlusion with collateralization.
- b. Moyamoya disease / Moyamoya syndrome
- c. "Puff of smoke" appearance on catheter angiography/MRA (network of basal collateral telangiectatic vessels).
- d. Sickle cell disease, Down syndrome (Trisomy 21), Neurofibromatosis type 1, cranial irradiation, and Post-TB meningitis vasculopathy.
- e. Treatment Options:
- Medical: Low-dose Aspirin (antiplatelet) and adequate hydration.
- Surgical revascularization: Direct (STA-MCA bypass) or Indirect (Encephaloduroarteriosynangiosis [EDAS] / Encephalomyosynangiosis [EMS]).
THG23-033
Analyze the case vignette, read the MRI (as shown in below image) and answer the questions below:
A term male baby born to primigravida, antenatal and perinatal transition—uneventful; On exclusive breastfeeds; presents on day 7 of life, poor feeding, profound lethargy, seizures, irregular respiratory pattern, hypertonia. His blood sugar is 30 mg/dL, calcium is normal; Sepsis screen is negative, urine ketones are positive, and pH is 7.28.
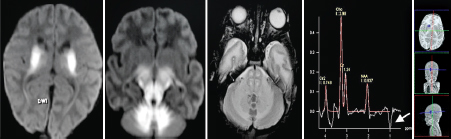
a. Describe the MRI findings.
b. What MRS finding you look for in this case?
c. What characteristic EEG finding is described in this disease?
d. Name the metabolic testing findings in this disorder.
e. What are the four clinical phenotypes of this disorder?
f. What is the treatment (long-term) (do not mention acute crisis treatment)?
Answer
- a. Symmetrical restricted diffusion (hyperintensity on DWI / low ADC) in the cerebellar white matter, posterior brainstem, globus pallidus, and thalami (classical MSUD edema pattern).
- b. Broad branched-chain amino acid and branched-chain alpha-ketoacid peak at 0.9–1.0 ppm on MRS.
- c. "Comb-like" rhythm (biphasic 5–7 Hz sharp-wave activity over central regions in sleep).
- d. Elevated branched-chain amino acids (Leucine, Isoleucine, Valine) and pathognomonic presence of alloisoleucine on plasma amino acid chromatography; positive 2,4-dinitrophenylhydrazine (DNPH) urine test.
- e. Phenotypes: Classic, Intermediate, Intermittent, and Thiamine-responsive.
- f. Long-term dietary restriction of BCAAs (leucine-restricted medical formula), daily thiamine supplementation (trial for thiamine-responsive form), regular plasma amino acid monitoring, and elective orthotopic liver transplantation.
THG23-034
A 13-year-old boy presents with a few months of progressively worsening urinary urgency and frequency of insidious onset with few months of low back pain and difficulty in walking. He is found to have asymmetry in feet with calf atrophy and arching of feet and clawing of tows on the right with absent right ankle jerk. Past history is remarkable for spine surgery during the neonatal period.
a. What is the possible diagnosis?
b. Name two spinal congenital malformations that increase the risk of development of this condition.
c. List three cutaneous manifestations/markers associated with this condition.
d. What is management of this condition?
Answer
- a. Tethered cord syndrome
- b. Myelomeningocele / spina bifida occulta, lipomyelomeningocele, diastematomyelia, tight/fatty filum terminale, and dermal sinus tract.
- c. Cutaneous markers: Hypertrichosis (faun-tail tuft of hair), sacral dimple / dermal sinus pit, hemangioma / port-wine stain, subcutaneous lipoma, and deviated gluteal cleft.
- d. Surgical lumbosacral exploration and detethering of the spinal cord (microsurgical cord untethering).
THG23-035
An 8-month-old boy is brought for concern of abnormal head shape. He is a preterm neonatal intensive care unit (NICU) graduate and has motor developmental delay. His head circumference and anterior fontanel are normal for age with an unremarkable neurological examination.
a. Mention two other risk factors for development of deformational plagiocephaly in an infant.
b. Mention two techniques for prevention.
c. How do you differentiate between deformational plagiocephaly and craniosynostosis (list three points)?
d. What are the treatment options available for this condition?
Answer
- a. Supine sleep position, congenital muscular torticollis, male sex, prematurity, multiple births, and developmental motor delay / limited neck mobility.
- b. Supervised tummy time during awake periods (>30 min/day in intervals), alternating head position in crib, and minimizing prolonged time in car seats/swings.
- c. Differentiating Deformational Plagiocephaly vs Craniosynostosis:
| Feature | Deformational Plagiocephaly | Craniosynostosis (Lambdoid) |
|---|---|---|
| Head shape from vertex | Parallelogram shape | Trapezoid shape |
| Ipsilateral ear position | Displaced anteriorly | Displaced posteriorly |
| Forehead asymmetry | Ipsilateral frontal bossing | Contralateral frontal bossing |
| Palpable ridge along suture | Absent | Present (raised bony ridge) |
- d. Physical therapy (neck stretching for torticollis), counter-positioning strategies, cranial molding orthosis (helmet therapy between 4–12 months), and surgery (rarely indicated unless true craniosynostosis).
THG23-036
An 18-month-old developmentally normal child develops a first episode of generalized tonic–clonic convulsion with fever, lasting for 10 minutes. His neurological examination is normal.
a. What are the indications to perform a lumbar puncture in such a situation?
b. Is an MRI scan of the brain indicated?
c. What are the indications for febrile seizure prophylaxis?
d. What are the major risk factors for recurrence?
e. What are the risk factors for epilepsy (development of unprovoked seizures in the future)?
Answer
- a. Indications for Lumbar Puncture in Febrile Seizure:
- Any child with meningeal signs (neck stiffness, Kernig/Brudzinski sign) or altered consciousness/lethargy
- Infants
months of age - Strongly consider in infants 6–12 months who are unvaccinated against Hib/Pneumococcus or pre-treated with antibiotics
- b. No, neuroimaging is NOT indicated for simple febrile seizures.
- c. Indications for intermittent prophylaxis (oral clobazam/diazepam at fever onset): Frequent recurrent febrile seizures, severe parental anxiety, prolonged febrile seizures/status, or remote access to medical care.
- d. Risk factors for recurrence:
- Age of onset
months - Duration of fever
hour before seizure onset - Low-grade temperature at seizure onset (
) - Family history of febrile seizures
- Age of onset
- e. Risk factors for future epilepsy:
- Complex febrile seizures (focal,
minutes, or within 24 hours) - Neurodevelopmental abnormality / baseline neurological deficit
- Family history of unprovoked epilepsy in first-degree relatives
- Complex febrile seizures (focal,
THG23-037
A 2-year-old boy presents with a 2-day history of high-grade fever, focal seizures, and altered sensorium with signs of meningeal irritation.
a. What are the contraindications to perform a lumbar puncture in this patient?
b. What are the indications for neuroimaging in this scenario?
c. What are the clinical and radiological features to suspect herpes simplex virus (HSV) encephalitis in this patient?
d. List few neurological complications of acute pyogenic meningitis.
e. How does antibiotic pretreatment affect results of cerebrospinal fluid (CSF) analysis?
f. How does a traumatic lumbar puncture influence interpretation of CSF analytes?
Answer
- a. Signs of raised ICP / impending brain herniation (cranial nerve palsies, sluggish pupils, posturing, Cushing triad), severe hemodynamic/respiratory instability, localized skin infection at puncture site, and severe thrombocytopenia/coagulopathy.
- b. Focal neurological deficits, new-onset focal seizures, papilledema, comatose state, or signs of brain herniation prior to LP.
- c. HSV Encephalitis Clues:
- Clinical: Focal temporal lobe seizures, acute behavioral/personality changes, fever, dysphasia.
- Radiological (MRI): Asymmetric T2/FLAIR hyperintensity with diffusion restriction in the temporal lobes, insular cortex, and inferior frontal lobes.
- d. Subdural effusion/empyema, hydrocephalus, cerebral infarction/vasculitis, sinovenous thrombosis, sensorineural hearing loss, and brain abscess.
- e. Rapidly sterilizes CSF culture (within 2–4 hours) and reduces Gram stain sensitivity, but CSF pleocytosis (neutrophilic), elevated protein, and low glucose usually persist for 48–72 hours.
- f. Introduces peripheral RBCs and WBCs: corrected by subtracting 1 WBC for every 500–700 RBCs; protein increases by approximately 1 mg/dL for every 1000 RBCs.
THG23-038
A 6-month-old infant presents with history of rapidly enlarging head size since birth.
a. Name the two most common causes of communicating hydrocephalus in infants.
b. List any two causes of noncommunicating hydrocephalus.
c. What is the mechanism of setting-sun sign in infants with hydrocephalus?
d. In an infant with hydrocephalus and prominent scalp veins, which diagnosis does an audible cranial bruit suggest?
e. Mention two findings on eye examination you will look for while examining an infant with hydrocephalus.
Answer
- a. Post-hemorrhagic hydrocephalus (following neonatal IVH) and post-infectious hydrocephalus (following bacterial meningitis).
- b. Aqueductal stenosis, Chiari II malformation, Dandy–Walker malformation, and posterior fossa tumors.
- c. Upward gaze palsy due to aqueductal distension and compression of the tectal plate (dorsal midbrain / Perlia's nucleus) from raised ICP.
- d. Vein of Galen aneurysmal malformation (VGAM) / intracranial arteriovenous malformation
- e. Papilledema, optic atrophy, sixth nerve (abducens) palsy (convergent squint), and chorioretinitis.
THG23-039
A 12-year-old boy is rushed to the emergency room (ER) after sustaining a road traffic accident and injury to the back. His Glasgow Coma Scale (GCS) is 15/15, cranial nerve examination is unremarkable with normal upper extremity power, but is noted to have a power of 0/4 in both lower extremities with ankle and knee areflexia and total loss of all sensation up to the umbilicus. On attempting to rise up from supine, his umbilicus moves upward.
a. To which spinal level do you localize the lesion?
b. What is clinical sign described called?
c. List two important steps of management (treatment) of this patient.
d. In spinal cord lesions above T6 level, what important complication (other than cervical spine/brainstem injury and resulting respiratory failure) is to be anticipated? What are its symptoms and signs?
e. If this child also has weakness in shoulder abduction and flexion, what would you monitor the patient for?
Answer
- a. T10 spinal cord level (umbilical sensory level)
- b. Beevor sign (upward deflection of umbilicus on abdominal flexion due to selective lower abdominal wall muscle weakness [T10–T12])
- c. Spinal immobilization (cervical/thoracic backboard and rigid collar), emergent spine MRI, high-dose IV methylprednisolone within 8 hours, and urgent neurosurgical spinal decompression/stabilization.
- d. Autonomic Dysreflexia: Exaggerated sympathetic response to noxious stimuli below lesion (e.g., bladder distension).
- Signs/Symptoms: Severe paroxysmal hypertension, throbbing headache, reflex bradycardia, facial flushing/sweating above lesion, and cold clammy skin below lesion.
- e. Monitor for diaphragmatic paralysis and acute respiratory failure (C3–C5 involvement innervating the diaphragm via phrenic nerve).
THG23-040
A 5-year-old developmentally normal boy presents with sudden onset of weakness of left side of the face and limbs since the past 4 hours. This occurred suddenly in school while he was seated in class. He reported having such an episode earlier in the morning but it had resolved in few minutes. The parents note a history of a self-limiting viral upper respiratory infection (URI) 1 week back. He does not complain of a headache or vomiting and is in a clear sensorium walking with a limp. He has never had any neurological concerns in the past.
a. Which imaging modality is preferred to identify the pathology in this patient?
b. What are the investigations you would like to perform?
c. Give two other differential diagnoses for acute onset hemiparesis in a child.
d. What is the most likely etiology in this child?
e. What are the treatment options?
Answer
- a. MRI brain with Diffusion-Weighted Imaging (DWI) and MR Angiography (MRA)
- b. Complete blood count, coagulation profile, thrombophilia screen (Protein C, S, Antithrombin III, Factor V Leiden, APLA), echocardiography, and intracranial/extracranial vascular imaging.
- c. Todd's paresis (postictal paralysis), hemiplegic migraine, acute disseminated encephalomyelitis (ADEM), intracranial hemorrhage, and focal cerebritis.
- d. Focal cerebral arteriopathy of childhood (FCA) / post-varicella or post-viral transient cerebral arteriopathy.
- e. Neuroprotective measures (hydration, normothermia, normoglycemia), antiplatelet therapy (Aspirin 3–5 mg/kg/day), short-course oral corticosteroids for inflammatory arteriopathy, and physical neurorehabilitation.
THG23-041
A 6-year-old girl presents with sudden onset weakness of the left side of the face with deviation of the angle of mouth to the right. She recovers with treatment in 3 weeks.
a. What is the most likely diagnosis?
b. How would you differentiate a lower motor neuron (LMN) lesion from an upper motor neuron (UMN) lesion in this case?
c. Treatment of this condition and specific precaution to be observed.
d. Mention the most important complication that may occur occasionally during recovery.
Answer
- a. Bell's palsy (Idiopathic acute lower motor neuron facial nerve palsy)
- b. In LMN facial palsy, both upper and lower quadrants of the face are paralyzed (inability to wrinkle forehead, close eye, or smile on affected side). In UMN lesion, forehead wrinkling is spared due to bilateral corticobulbar innervation.
- c. Treatment: Oral Prednisolone (1–2 mg/kg/day for 7–10 days with tapering); Precaution: Eye care (artificial tears by day, eye ointment and eye taping at night to prevent exposure keratitis).
- d. Aberrant facial nerve regeneration (Synkinesis / Crocodile tears syndrome - gustatolacrimal reflex).
THG23-042
A 6-month-old male infant is admitted with second episode of pneumonia in the last 2 months. He has a history of motor developmental delay with complete lack of head control, her social and language milestones are normal. He is found to be floppy without any elicitable deep tendon reflexes. He is the firstborn child to consanguineous parents with an unremarkable antenatal, perinatal, and family history.
a. Which important physical examination finding would support a diagnosis of spinal muscular atrophy (SMA) in this child?
b. What is the diagnostic test?
c. Mention three new drugs approved for this condition.
d. Name the gene that determines prognosis in SMA.
e. Mention two muscle groups selectively spared in SMA.
f. Mention two long-term complications.
Answer
- a. Tongue fasciculations and paradoxical (bell-shaped) breathing due to intercostal weakness with diaphragmatic sparing.
- b. SMN1 gene deletion testing by Multiplex Ligation-dependent Probe Amplification (MLPA)
- c. Disease-Modifying Therapies:
- Nusinersen (Spinraza) - intrathecal antisense oligonucleotide
- Risdiplam (Evrysdi) - oral SMN2 splicing modifier
- Onasemnogene abeparvovec (Zolgensma) - IV AAV9 gene therapy
- d. SMN2 gene copy number (higher copy numbers correlate with milder clinical phenotypes).
- e. Extraocular muscles and anal/urethral sphincters
- f. Progressive respiratory failure, severe kyphoscoliosis, feeding difficulty/aspiration, and joint contractures.
THG23-043
An 8-year-old boy presents with 1 day of lethargy and seizures following 3 days of an acute self-limited viral URI.
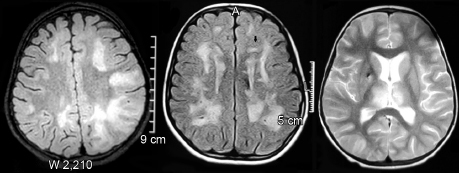
a. What is the diagnosis?
b. Name the antibody associated with this entity.
c. Mention two common neurological structures affected other than brain.
d. What are the treatment options?
Answer
- a. Acute disseminated encephalomyelitis (ADEM)
- b. Anti-Myelin Oligodendrocyte Glycoprotein (anti-MOG) antibodies
- c. Optic nerves (optic neuritis) and spinal cord (acute transverse myelitis)
- d. High-dose IV Methylprednisolone (30 mg/kg/day for 3–5 days), IV Immunoglobulin (IVIG, 2 g/kg), and therapeutic plasma exchange (plasmapheresis) for steroid-refractory cases.
THG23-044
A 1-year-old boy presents with fever, seizures, and altered sensorium.
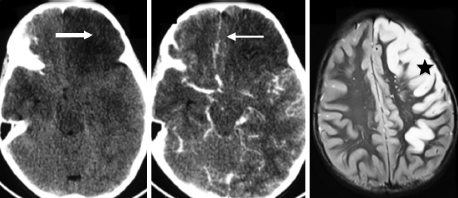
a. What is the diagnosis?
b. What is the confirmatory test?
c. What is the EEG finding?
d. What is the treatment?
Answer
- a. Herpes simplex virus (HSV-1) encephalitis
- b. CSF HSV-1 DNA PCR
- c. Periodic lateralized epileptiform discharges (PLEDs) / frontotemporal sharp and slow wave complexes
- d. Intravenous Acyclovir (500 mg/m² or 20 mg/kg every 8 hours) for 14–21 days.
THG23-045
A 10-year-boy with chronic kidney disease (CKD) presents with seizures and altered sensorium.
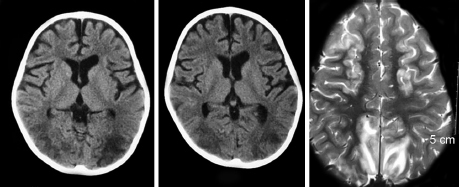
a. What is the diagnosis?
b. What are the radiological differential diagnoses?
c. Discuss the pathophysiology.
d. What are the risk factors?
e. What is the treatment?
Answer
- a. Posterior reversible encephalopathy syndrome (PRES)
- b. Acute ischemic stroke (posterior circulation / basilar artery occlusion), cerebral venous sinus thrombosis, acute hypoglycemic brain injury, and infectious encephalitis.
- c. Acute severe hypertension overcomes cerebral autoregulation, leading to hyperperfusion, breakdown of blood-brain barrier, and vasogenic edema predominantly in parieto-occipital white matter.
- d. Severe hypertension, renal disease/CKD, immunosuppressants (tacrolimus, cyclosporine), chemotherapy, systemic lupus erythematosus (SLE), and sepsis.
- e. Gradual BP reduction with IV antihypertensives (Labetalol, Nicardipine, Sodium nitroprusside), removal of offending toxic drugs, and antiseizure therapy.
THG23-046
Read the case vignette and MRI and answer the questions below:
A 1-year-old boy presenting with fever, URI × 1 day followed by seizures, and deep altered sensorium on day 1. On examination: Comatose—intubated, raised intracranial pressure (ICP)—posturing. Investigations: CSF—normal cells, high protein, normal sugar, culture, polymerase chain reaction (PCR) panel negative; Nasopharyngeal swab—influenza positive
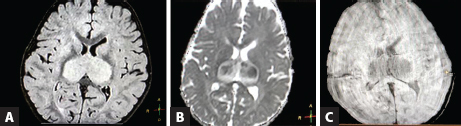
a. Identify the sequences given in image A to C
b. What is the diagnosis?
c. Name the serum biochemical markers of this disorder.
d. Mention two important viruses causing similar clinical and radiological picture
e. What is the treatment?
Answer
- a. Image A: FLAIR; Image B: Apparent Diffusion Coefficient (ADC); Image C: Gradient Recalled Echo (GRE) / Susceptibility Weighted Imaging (SWI) showing tricolor / hemorrhage pattern.
- b. Acute necrotizing encephalopathy of childhood (ANEC)
- c. Markedly elevated serum transaminases (AST/ALT), thrombocytopenia, hyperferritinemia, and elevated serum/CSF Interleukin-6 (IL-6).
- d. Influenza A/B virus and Human Herpesvirus 6 (HHV-6) (also SARS-CoV-2, enteroviruses).
- e. High-dose IV pulse Methylprednisolone, IV Immunoglobulin (IVIG), and anti-IL-6 therapy (Tocilizumab) within 24 hours of onset.
THG23-047
A 14-year-old girl with fever and headache of 1 week duration.
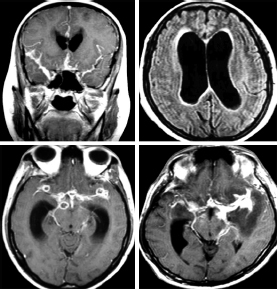
a. What are the imaging findings (as shown in above image)?
b. What is the diagnosis?
c. Explain the complete treatment plan.
Answer
- a. Hydrocephalus with ventricular dilatation, thick enhancing basal meningeal exudates, tuberculomas, and left basal ganglia / middle cerebral artery territory infarction (tubercular vasculitis).
- b. Tuberculous meningitis (TBM) with complications (Stage II/III TBM)
- c. Treatment Plan:
- Anti-tubercular therapy (ATT) for 12 months (2HRZE + 10HRE)
- Systemic corticosteroids: IV Dexamethasone (0.4 mg/kg/day) or oral Prednisolone (2–4 mg/kg/day) tapered over 6–8 weeks
- Neurosurgical management: Ventriculoperitoneal (VP) shunt or external ventricular drain for communicating/obstructive hydrocephalus.
THG23-048
Spot the MRI findings and diagnosis given in image A to C:
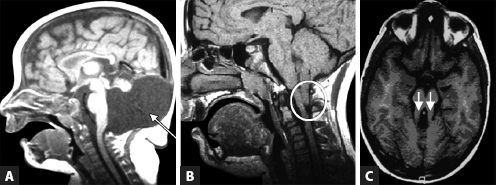
Answer
- Image A: Large posterior fossa cyst communicating with 4th ventricle, cerebellar vermian hypoplasia/agenesis, and elevated tentorium
Dandy–Walker malformation - Image B: Herniation of cerebellar tonsils
through foramen magnum into cervical canal Chiari I / II malformation - Image C: Thickened and horizontally oriented superior cerebellar peduncles with deep interpeduncular fossa ("Molar tooth sign")
Joubert syndrome
THG23-049
Read the following MRI of a 2-year-old boy with seizures and developmental delay and answer the questions below:
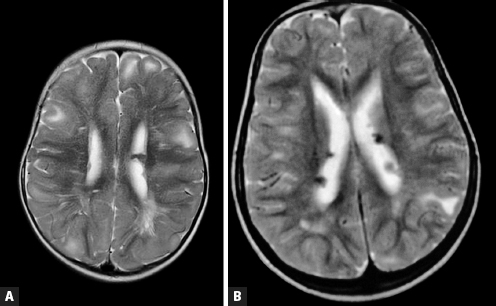
a. Identify the findings in image A and B.
b. What is the diagnosis?
c. What are the cutaneous manifestations?
d. Name two non-neurological manifestations.
e. What is the targeted pharmacologic treatment available?
Answer
- a. Image A: Cortical and subcortical tubers; Image B: Subependymal nodules (SEN) along the lateral ventricular walls.
- b. Tuberous Sclerosis Complex (TSC)
- c. Ash-leaf hypomelanotic macules, shagreen patches (connective tissue nevi), facial angiofibromas, ungual fibromas (Koenen tumors), and fibrous cephalic plaques.
- d. Cardiac rhabdomyoma, renal angiomyolipoma / cysts, and pulmonary lymphangioleiomyomatosis (LAM).
- e. mTOR inhibitors: Everolimus / Sirolimus
THG23-050
Below is the noncontrast CT (image A) and contrast MRI brain of a 14-year-old boy who presented with progressive headache for 2 months:
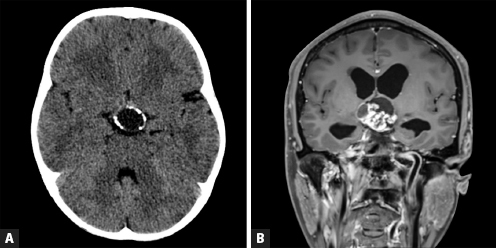
a. Describe the imaging features in above image.
b. What is the diagnosis?
c. Explain the common clinical symptoms at presentation.
d. What is the treatment option?
Answer
- a. Suprasellar heterogeneous mass with solid nodular enhancing components, cystic non-enhancing areas, and prominent calcifications on non-contrast CT.
- b. Craniopharyngioma (adamantinomatous type)
- c. Symptoms of raised ICP (headache, vomiting), visual disturbances (bitemporal hemianopia due to optic chiasm compression), and neuroendocrine deficiencies (growth failure, delayed puberty, central diabetes insipidus).
- d. Surgical resection (gross total or subtotal via transsphenoidal/craniotomy approach), adjuvant stereotactic radiotherapy/proton beam therapy, and hormone replacement therapy.