VVK06-001
Answer the following questions regarding acute abdomen:
a. What is the age of peak incidence of appendicitis?
b. What is the classic triad for intussusception?
c. What laboratory tests are satisfactory as an initial screen in patients with abdominal pain?
d. What is the treatment of choice for intussusception?
e. Name three causes of abdominal pain arising from a gonad in a young girl.
f. What is the classic finding on appendicitis?
g. How do you test for peritoneal irritation?
Answer
- a. Teenage and young adult years (12–18 years); males slightly more than females.
- b. Severe episodic pain, "currant jelly" stool, transverse tubular abdominal mass.
- c. CBC, BUN, creatinine, electrolytes, blood sugar, urine analysis. Serum amylase, lipase, aminotransferase. Examination of stool. Chest X-ray and flat and upright film of abdomen.
- d. Hydrostatic reduction. However, in patients with prolonged intussusception with signs of shock, peritoneal irritation, intestinal perforation, or pneumatosis intestinalis, reduction should not be attempted.
- e. Ovarian tumor, torsion of an ovary, ruptured ovarian cyst.
- f. Right lower quadrant tenderness.
- g. Rebound tenderness.
VVK06-002
A 3-year-old infant presented with failure to thrive, recurrent diarrhea, irritability and pain abdomen. On examination, he was found to be wasted with edema and finger clubbing. His tTG ELISA for both IgA and IgG was positive.
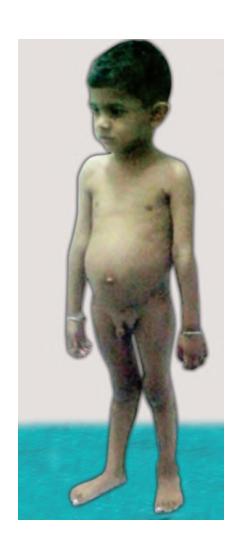
a. What is this condition?
b. Name other serological tests done to diagnose this condition.
c. What will you do to confirm the diagnosis?
d. Name three conditions associated with high frequency of this disease.
Answer
- a. Celiac disease.
- b. Antigliadin and anti-endomysial antibodies.
- c. Small bowel biopsy.
- d. Down's syndrome, Turner's syndrome, Williams syndrome, thyroiditis, selective IgA deficiency.
VVK06-003
A 15-year-old girl presents to the emergency department with sudden onset of watery diarrhea tinged with blood. The girl was previously healthy. She has been on topical benzoyl peroxide and oral clindamycin for acne vulgaris for past 4 weeks. Physical examination reveals a slightly distended abdomen that is diffusely tender. Her temperature is 38.1°C (100.5°F). She has not been exposed to any uncooked meat and has not eaten any unusual foods.
a. What is the most likely diagnosis?
b. What is the other name for such type of diarrhea?
c. What drugs can be given to cure this? Give the doses and duration of treatment also.
Answer
- a. Pseudomembranous enterocolitis (caused by the toxins produced by Clostridium difficile. It occurs in some patients after treatment with antibiotics, especially clindamycin, cephalosporins, and amoxicillin. Patients develop fever and abdominal pain with diarrhea containing leukocytes and blood).
- b. Antibiotic-associated diarrhea.
- c. Most essential step is to discontinue the current antibiotic, if possible.
- Oral metronidazole 20–40 mg/kg/day divided q 6–8 hourly for 7–10 days.
- Oral/Intravenous vancomycin 25–40 mg/kg/day divided q 6 hourly for 7–10 days.
VVK06-004
A mother is being counselled for prevention of allergy. She wants to know which of the following could be (A) food intolerance (B) food hypersensitivity:
i. Lactose intolerance
ii. Urticaria
iii. Heiner syndrome (cow's milk hypersensitivity)
iv. Celiac disease
v. Irritable bowel syndrome
Answer
- i. A (Food intolerance)
- ii. B (Food hypersensitivity)
- iii. B (Food hypersensitivity)
- iv. B (Food hypersensitivity)
- v. A (Food intolerance)
VVK06-005
Match the following allergens with their foods:
| Food | Allergen |
|---|---|
| a. Cow's milk | 1. Paralbumin |
| b. Egg | 2. Vicilin |
| c. Peanut | 3. Ovomucoid |
| d. Fish | 4. Casein |
Answer
- a. Cow's milk — Casein (4)
- b. Egg — Ovomucoid (3)
- c. Peanut — Vicilin (2)
- d. Fish — Paralbumin (1)
VVK06-006
A 15-month-old chubby male child is admitted with regression of motor milestones since 3 months, rhythmic involuntary movements of (distal > proximal) the upper limbs, tremulous cry and generalized hypotonia. He is having loose stools for the last 7–8 days. He has brownish hair, reticular pigmentation of the skin particularly of the dorsum of the hands. There is pallor and mild hepatosplenomegaly. The involuntary movement stops once patient sleeps.
a. What is your most likely diagnosis?
b. What do you expect in peripheral smear and CT head for this patient?
c. What are the changes in liver if you go for liver biopsy?
d. What is the treatment for involuntary movements?
Answer
- a. Nutritional tremor syndrome.
- b. Peripheral smear: Megaloblastic anemia; CT head: Cerebral atrophy.
- c. Liver biopsy: Fatty changes.
- d. Carbamazepine and propranolol.
VVK06-007
DRUG-ORS SALT:
a. Write the composition of WHO ORS in grams per liter.
b. Write the composition of WHO ORS in mmol per liter.
c. In which diarrhea is hypo-osmolar ORS used?
Answer
- a. Composition in g/L:
- Standard WHO ORS: NaCl = 3.5 g/L, KCl = 1.5 g/L, Trisodium citrate = 2.9 g/L (or NaHCO3 = 2.5 g/L), Glucose = 20 g/L.
- Reduced osmolarity ORS: NaCl = 2.6 g/L, Glucose = 13.5 g/L, KCl = 1.5 g/L, Trisodium citrate = 2.9 g/L. Total = 20.5 g/L.
- b. Composition in mmol/L (Reduced Osmolarity ORS):
- Na+ = 75 mmol/L (90 mEq/L in standard)
- K+ = 20 mmol/L
- Cl– = 65 mmol/L (80 mEq/L in standard)
- Citrate = 10 mmol/L
- Glucose = 75 mmol/L (111 mmol/L in standard)
- Total osmolarity = 245 mOsm/L (311 mOsm/L in standard)
- c. Rotavirus-induced diarrhea (and acute non-cholera watery diarrhea in children).
VVK06-008
Study the photograph and answer the following questions:
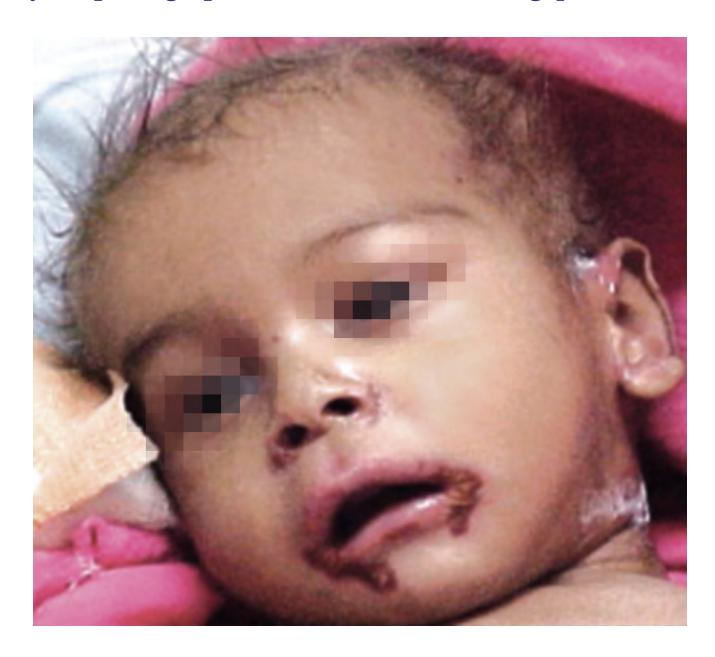
a. Identify this condition which is caused by zinc deficiency.
b. What is the dose of zinc for this condition?
c. Name two other diseases where zinc supplements are indicated.
Answer
- a. Acrodermatitis enteropathica.
- b. 50–150 mg/day (elementary zinc 1–3 mg/kg/day).
- c. Acute or persistent diarrhea, Wilson's disease.
VVK06-009
An 8-month-old girl has been crying and pulling up her legs as if she has abdominal pain. She has vomited several times and is not interested in taking her bottle. She has a fever of 100.5°F. She has not passed stool today. Her parents think that she looks pale and lethargic.
a. Give 2 most likely differential diagnoses.
b. What additional differential diagnosis will you think if this was a male child?
Answer
- a. Intussusception, gastroenteritis, obstructed hernia.
- b. Testicular torsion.
VVK06-010
An 8-year-old girl has periumbilical pain that began 8 hours ago; since then she has vomited once and has had one small, loose, bowel movement. Her last meal was 12 hours ago, and she is not hungry. She denies dysuria and urinary frequency. On examination, she is lying quietly in bed with temperature of 101.5°F. Her other vital signs are normal. Her abdominal examination reveals few bowel sounds, rectus muscle rigidity, and tenderness to palpation, particularly periumbilically. There is some abdominal tenderness with gentle bimanual palpation. She has pain on digital rectal examination. Breath sounds are clear and she has no rashes.
a. What is the most likely diagnosis?
b. What is the single most reliable clinical finding for diagnosing this?
c. What are the sonographic criteria to diagnose this condition?
Answer
- a. Acute appendicitis.
- b. Localized abdominal tenderness (especially right lower quadrant / McBurney's point tenderness) is the single most reliable finding.
- c. Ultrasound criteria for appendicitis:
- Outer diameter > 6 mm (wall thickness increased)
- Luminal distention
- Lack of compressibility
- Complex mass in right lower quadrant
- Appendicolith / Fecalith
- Findings suggestive of advanced/perforated appendicitis: Asymmetric wall thickening, abscess formation, free intraperitoneal fluid, surrounding hyperechoic mesentery/edema, decreased local tenderness to compression.
VVK06-011
A 5-year-old female with severe abdominal pain feels nauseated but has not vomited. She has noticed a faint rash on her feet, legs and buttocks. The temperature is 101°F.
a. What is the most likely diagnosis?
b. What intestinal complications can occur in this condition?
c. What is the medical management for this?
Answer
- a. Henoch-Schönlein purpura (Anaphylactoid purpura / IgA vasculitis).
- b. Hemorrhage, obstruction, intussusception (typically ileo-ileal).
- c. Supportive care with hydration and analgesia. Therapy with oral or intravenous corticosteroids (prednisolone 1–2 mg/kg/day) is indicated for severe gastrointestinal pain, bleeding, or complications.
VVK06-012
An 8-month-old female has recent onset of diarrhea. Further history reveals recurrent periods of loose stools, frequent otitis media, and upper respiratory infections. She is being followed for failure to thrive. There has been no vomiting or fever. Her celiac serology and HIV ELISA are negative.
a. What is the most likely condition?
b. What is its mode of inheritance?
c. Which intestinal protozoal infection is commonly associated with this condition?
Answer
- a. Selective IgA deficiency (or Common Variable Immunodeficiency / X-linked agammaglobulinemia).
- b. Autosomal dominant with variable expression (or autosomal recessive / polygenic).
- c. Intestinal giardiasis (Giardia lamblia).
VVK06-013
An 18-month-old boy is receiving 'Augmentin' for otitis media. Now he has diarrhea and a diaper rash. There is no fever or vomiting.
a. What is the most likely cause for the diarrhea?
b. Define persistent diarrhea.
c. How do you differentiate between osmotic and secretory diarrhea?
Answer
- a. Antibiotic-induced diarrhea due to 'Augmentin' (amoxicillin-clavulanate).
- b. Diarrhea of acute onset that lasts for 14 days or beyond, typically associated with nutritional deterioration.
- c. Comparison:
| Parameter | Osmotic Diarrhea | Secretory Diarrhea |
|---|---|---|
| Volume of stool | < 200 mL/24 h | > 200 mL/24 h |
| Response to fasting | Diarrhea stops | Diarrhea continues |
| Stool Na+ | < 70 mEq/L | > 70 mEq/L |
| Reducing substances | Positive | Negative |
| Stool pH | < 5.0 | > 6.0 |
| Stool Osmotic Gap | High (> 100 mOsm/kg) | Normal / Low (< 50 mOsm/kg) |
VVK06-014
A marriage dinner was followed by the majority of attendees developing vomiting and watery diarrhea with streaks of blood on the next day. Unaffected attendees did not eat the kheer (milk based sweet). A few ill family members are mildly febrile.
a. What is the most likely etiology for this condition?
b. What is the incubation period of this causative organism?
c. What antibiotics will you prescribe to the affected members?
d. What advice will you give to family members to prevent person-to-person transmission?
Answer
- a. Salmonella food poisoning (Salmonellosis / non-typhoidal Salmonella).
- b. 6–72 hours (mean ~24 hours).
- c. Antibiotics are not generally recommended for uncomplicated Salmonella gastroenteritis because they may prolong the excretion of Salmonella, alter gut microbiota, and risk creating a chronic carrier state. (Reserved for infants <3 months, bacteremia, immunocompromised).
- d. Safe and clean water supply, meticulous hand hygiene (washing hands with soap before eating and after defecation), safe food preparation and storage (refrigeration of milk/dairy products).
VVK06-015
A 12-year-old female has had diarrhea, abdominal pain and flatulence. She often notices some abdominal pain in the late mornings and early afternoon. She has not noticed blood in her stool. The situation worsens on taking milk.
a. What is the likely cause?
b. How do you make a diagnosis in this case?
c. Name 2 conditions where this condition can occur transiently?
Answer
- a. Lactose intolerance (Lactase deficiency).
- b. Diagnosis:
- Stool test for reducing substances using Clinitest reagent (acidic stool pH < 5.5 and reducing substances > 0.5% / 2+).
- Hydrogen breath test (rise in breath H2 > 20 ppm after lactose ingestion).
- Small bowel mucosal biopsy for lactase enzyme assay.
- c. Acute viral gastroenteritis (e.g. Rotavirus) and Celiac disease.
VVK06-016
Match the pathophysiological mechanism of diarrhea with the condition:
| Mechanism | Condition |
|---|---|
| a. Secretory diarrhea | 1. Laxative abuse |
| b. Osmotic diarrhea | 2. Irritable bowel disease |
| c. Increased motility | 3. Celiac disease |
| d. Altered mucosal surface area | 4. Cholera |
| e. Invasiveness | 5. Amebiasis |
Answer
- a. Secretory diarrhea — 4. Cholera
- b. Osmotic diarrhea — 1. Laxative abuse
- c. Increased motility — 2. Irritable bowel disease
- d. Altered mucosal surface area — 3. Celiac disease
- e. Invasiveness — 5. Amebiasis
VVK06-017
You are managing a case of persistent diarrhea by taking him to diet plan A (reduced lactose). Three to four days later you are not satisfied with the response and you want to change over to diet B (lactose free).
a. What are the indications for changing diet from A to B or B to C?
b. What are the causes for ineffective ORS therapy while managing a case of acute watery diarrhea?
Answer
- a. Indications for changing diet (treatment failure):
- Stool frequency > 10 watery stools/day after 48 hours of starting a particular diet.
- Return/reappearance of signs of dehydration anytime after starting diet.
- Failure to establish weight gain by the 7th day of dietary management.
- b. Causes for ineffective ORS therapy:
- High purge rate (> 5 mL/kg/hour).
- Persistent severe vomiting (> 3 vomits/hour).
- Paralytic ileus or marked abdominal distension.
- Incorrect preparation / hyperosmolar ORS formulation.
- Severe glucose malabsorption.
VVK06-018
A 2-month-old male, "fussy", baby comes with flatulence, diarrhea and vomiting. He is on breast-feeds. He had viral gastroenteritis 10 days back. Before the infection, mother's milk was well tolerated. Body weight is within normal limits. He is moderately dehydrated. Stool shows presence of reducing sugars with no reaction for glucose. You make a diagnosis of lactose intolerance and start him on reduced lactose diet.
a. What are the indications for changing diet in case of non or poor response?
b. What are diet A, B and C?
Answer
- a. Indications for changing diet:
- Stool frequency > 10 watery stools/day even after 48 hours of starting diet.
- Return of signs of dehydration anytime after starting diet.
- Failure to establish weight gain by 7th day of dietary management.
- b. Types of diet:
- Diet A: Reduced lactose diet (e.g. milk-cereal mixture, half milk + half puffed rice / rice gruel).
- Diet B: Lactose-free diet (e.g. egg-white based diet, soy-based formula, or commercial lactose-free formula).
- Diet C: Monosaccharide-based diet (e.g. glucose/galactose based, comminuted chicken feed, amino-acid based elemental formula).
VVK06-019
A 2-year-old male child presented with diarrhea of 3 weeks duration with failure to thrive. He was started with nutrition rich feeds (Simyl-MCT drops, HMF sachet and pediasure powder) and antibiotics at a peripheral health center 7 days back. Since then diarrhoea has increased and patient is losing weight. He was moderately dehydrated at admission. His daily stool output is around 185 ml and his stool Na+ is 42 mEq/L and K+ is 3.8 mEq/L. His stool was not yet examined for pH and reducing substance.
a. What is the diagnosis based on these investigations?
b. Calculate the osmotic gap.
c. What is the next line of management for this child?
Answer
- a. Chronic osmotic diarrhea (secondary to carbohydrate / lactose intolerance or enteral feed hyperosmolarity).
- b. Osmotic gap calculation:
(A gap > 100 mOsm/kg confirms osmotic diarrhea). - c. Remove the osmotic load from the diet, stop current concentrated feeds for 24 hours while maintaining hydration with ORS/IV fluids, and then restart with a low-lactose or lactose-free diet.
VVK06-020
An 18-month-old male infant manifests failure to thrive, poor appetite, abdominal distension, diarrhea and irritability. He has been well till 9 months of age. Thereafter, he was weaned from breast milk to regular foods. He was diagnosed as a case of celiac disease and started on gluten free diet and was symptom free since then. 3 days back parents had gone for a marriage party and there they fed something to the child. 24 hours later, this child started having protracted vomiting, abdominal distension and was brought to casualty in very sick general condition in shock and had to be ventilated.
a. What is the patient suffering from presently?
b. What is the treatment of choice for this patient (Other than symptomatic support)?
c. Write the conditions in which the celiac disease is more prevalent?
Answer
- a. Celiac crisis.
- b. Systemic corticosteroids (e.g. IV methylprednisolone / hydrocortisone).
- c. Selective IgA deficiency, Down syndrome, Turner syndrome, Williams syndrome, autoimmune thyroiditis, Type 1 Diabetes Mellitus.
VVK06-021
Answer the following questions:
a. Enlist ingredients, calories/100 mL and protein/100 mL of following diet:
- F75
- F100
b. What are the time frames for initial treatment, rehabilitation and follow up for the management of severe acute malnutrition (SAM)?
Answer
- a. SAM Starter & Catch-up Feeds:
- F75 (Starter diet):
- Ingredients (per 1000 mL): Dried skim milk 25 g, sugar 70 g, cereal flour 35 g, vegetable oil 27 g, mineral-vitamin mix 20 mL, water to make 1000 mL.
- Energy: 75 kcal/100 mL
- Protein: 0.9 g/100 mL
- F100 (Catch-up growth diet):
- Ingredients (per 1000 mL): Dried skim milk 80 g, sugar 50 g, vegetable oil 60 g, mineral-vitamin mix 20 mL, water to make 1000 mL.
- Energy: 100 kcal/100 mL
- Protein: 2.9 g/100 mL
- F75 (Starter diet):
- b. Time frames for SAM management:
- Initial stabilization phase: Days 1–7
- Rehabilitation phase: Weeks 2–6
- Follow-up phase: Weeks 7–26
VVK06-022
A 10-years-old girl known to have cystic fibrosis presents with a 4 day history of increasing abdominal pain and vomiting which on the last two occasions had contained bile. On examination she has a distended abdomen with palpable loops of bowel. There is also some tenderness in the left iliac fossa but no guarding. Plain abdominal films show dilated bowel loops with fluid levels.
a. Give 2 possible diagnosis.
b. Give one investigation which might help to make a diagnosis.
c. Mention 2 neonatal GI complications of cystic fibrosis.
d. How is cystic fibrosis inherited?
Answer
- a. Distal intestinal obstruction syndrome (DIOS) and intussusception.
- b. Abdominal ultrasonography or Gastrografin / water-soluble contrast enema.
- c. Meconium ileus, meconium plug syndrome, meconium peritonitis.
- d. Autosomal recessive (CFTR gene mutation on chromosome 7q31.2).
VVK06-023
A 11-year-old girl with cystic fibrosis (CF) is found to be pale on routine general examination. On systemic examination, presence of enlarged liver and spleen is noted. She is investigated and found to have Hb-9 g/dL, TLC 2,000/cumm and platelet count of 56,000/cumm. Liver enzymes are moderately raised.
a. What complication of CF has this girl developed?
b. What is the likely cause for this thrombocytopenia?
c. What proportion of patients affected with CF develop this complication?
Answer
- a. Focal biliary cirrhosis / hepatic cirrhosis with portal hypertension.
- b. Hypersplenism (secondary to splenomegaly from portal hypertension).
- c. < 10% (approx. 2–5%).
VVK06-024
State TRUE/ FALSE with regards to infant nutrition:
a. Bottle fed infants put weight on a faster rate than breast fed infants.
b. Breast fed infants spend less time in REM sleep than bottle fed infants.
c. Breast and formula milk fed infants have identical amino acid profiles.
d. Breast milk and formula milk contain identical quantities of PUFA.
Answer
- a. True
- b. True
- c. False
- d. False
VVK06-025
An 8-month-old infant is admitted with one day history of persistent crying and not taking his feeds. Crying is episodic and is associated with leg and hip flexion. On abdominal examination, a centrally placed 'sausage-shaped' mass is palpable.
a. Give the most likely diagnosis.
b. What finding is noted on rectal examination of this child?
c. What relevant investigation would you like to do for this child?
d. What would be the diagnosis if, in addition to the above, the infant was lethargic and pale with abdominal tenderness and absent bowel sounds?
e. What would be the next two steps in management in order of priority?
Answer
- a. Intussusception (ileocolic intussusception).
- b. Blood or "currant jelly" bloody mucus on examining finger.
- c. Abdominal ultrasonography (Target/doughnut sign, pseudokidney sign), plain abdominal X-ray, serum electrolytes and BUN/creatinine.
- d. Peritonitis / intestinal perforation / bowel gangrene.
- e.
- Aggressive IV fluid resuscitation, bowel rest, NG decompression, and IV broad-spectrum antibiotics.
- Urgent open reduction / laparotomy (contraindicated for pneumatic/hydrostatic reduction).
VVK06-026
A 4-week-old male baby presents with a history of vomiting for 3 days. Despite this, he is eager to feed. On examination there is dehydration but no fever. His investigations are shown below:
Na+ — 128 mEq/L ; K+ — 3.0 mEq/L; Cl– — 86 mEq/L ; HCO3 — 36 mmol/L; pH 7.50.
a. Describe these results.
b. Give 3 differential diagnoses for this condition.
c. What is the most likely diagnosis?
d. Give 3 most useful investigations you will carry out for this child.
Answer
- a. Hypochloremic, hyponatremic, hypokalemic metabolic alkalosis.
- b. Congenital hypertrophic pyloric stenosis (CHPS), Gastroesophageal reflux (GERD), Urinary tract infection (UTI), Congenital adrenal hyperplasia (salt-wasting).
- c. Congenital hypertrophic pyloric stenosis (CHPS).
- d.
- Test feed to palpate the 'pyloric olive / tumour' and observe visible peristaltic waves.
- Abdominal ultrasonography (pyloric muscle thickness > 3 mm, length > 14-16 mm).
- Serum electrolytes and blood gas analysis (plus urine routine/microscopy).
VVK06-027
A 12-month-old infant presents with bilious vomiting and abdominal distention for 10 hours. His mother states that the infant has been constipated since birth and failed to pass meconium during the first 48 hours of life. On examination, he is very irritable. His length and weight are both below the 5th percentile according to his age. His abdomen is moderately distended. After a digital rectal examination, a fair amount of stool ejects out from the anus.
a. What is the most likely diagnosis?
b. Give an alternative name for this condition.
c. What are the common conditions associated with this condition?
d. What is the recent treatment strategy used for this condition?
Answer
- a. Hirschsprung disease.
- b. Congenital aganglionic megacolon.
- c. Hirschsprung disease may be associated with:
- Down syndrome (Trisomy 21)
- Smith-Lemli-Opitz syndrome
- Waardenburg syndrome
- Cartilage-hair hypoplasia syndrome
- Congenital central hypoventilation syndrome (Ondine curse)
- Urogenital or cardiovascular malformations
- Microcephaly and abnormal facies
- Cleft palate, hydrocephalus, micrognathia
- d. Transanal endorectal pull-through (TEPT) / Laparoscopic-assisted endorectal pull-through (Swenson, Duhamel, or Soave procedure).