VVK15-001
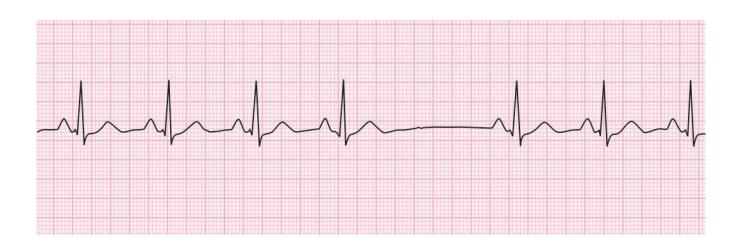
Calculate the heart rate
Answer
60/minute.
VVK15-002
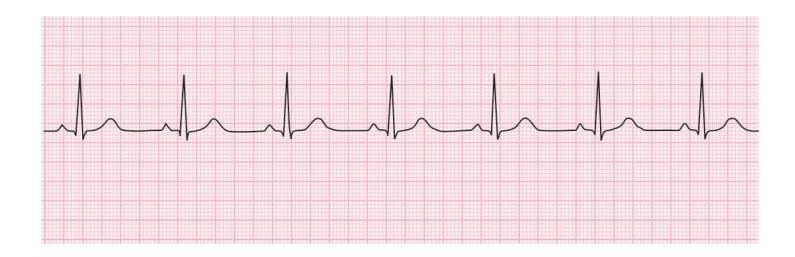
Is this ECG normal or not? If not why?
Answer
It's a normal ECG (depends on which lead it represents).
VVK15-003
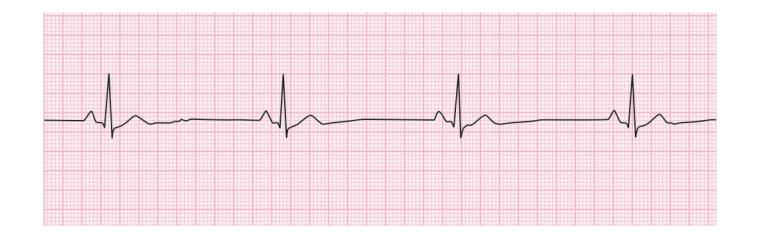
What is your management?
Answer
Sinus bradycardia—medical management. Rule out hypothyroidism.
VVK15-004
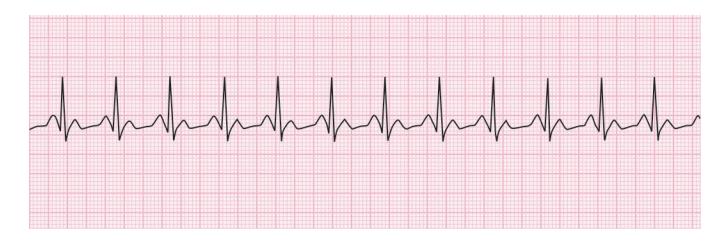
What is your management?
Answer
Sinus tachycardia—rule out hyperthyroidism, febrile illness, anemia and myocarditis.
VVK15-005
What is your management?
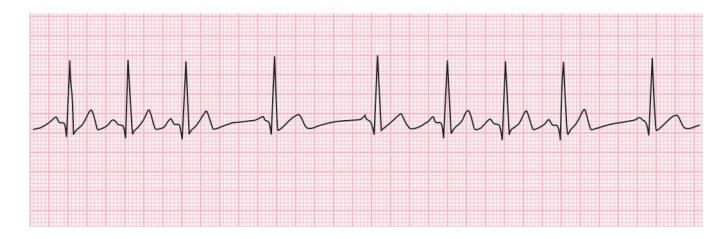
Answer
Medical management—beta blockers if symptomatic with palpitations.
VVK15-006
What is your diagnosis?
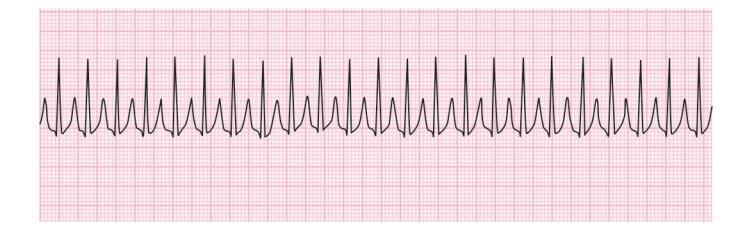
Answer
Narrow QRS tachycardia—supraventricular tachycardia.
VVK15-007
What is your diagnosis?
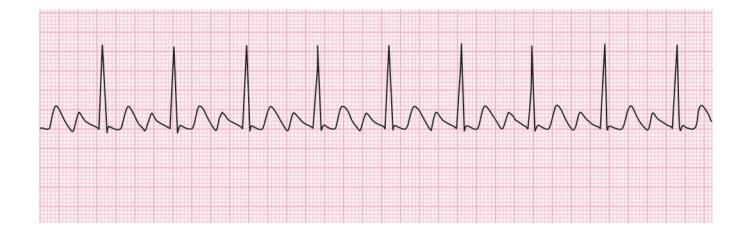
Answer
Sinus tachycardia.
VVK15-008
What is your diagnosis?
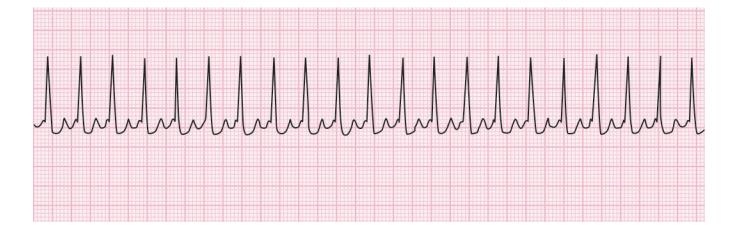
Answer
Supraventricular tachycardia—? atrial flutter.
VVK15-009
What is your diagnosis?
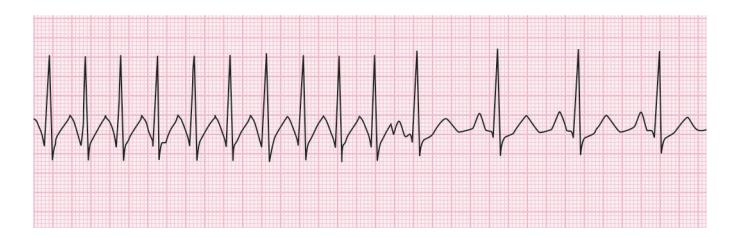
Answer
Termination of narrow QRS supraventricular tachycardia.
VVK15-010
What is your diagnosis?
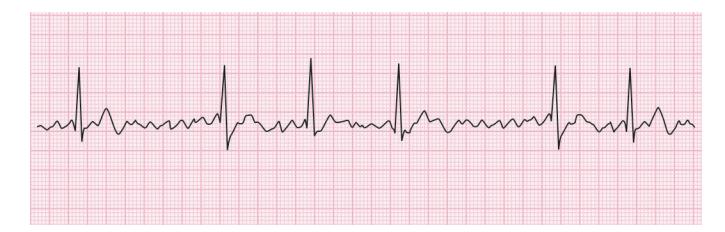
Answer
Atrial fibrillation.
VVK15-011
What is your diagnosis?
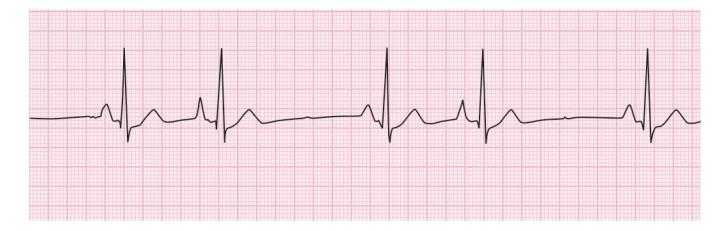
Answer
Atrial ectopic with pause.
VVK15-012
What is your diagnosis?
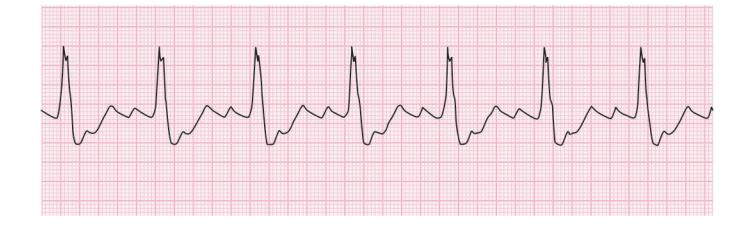
Answer
Broad QRS rhythm—needs complete 12 lead ECG
VVK15-013
What is your diagnosis?
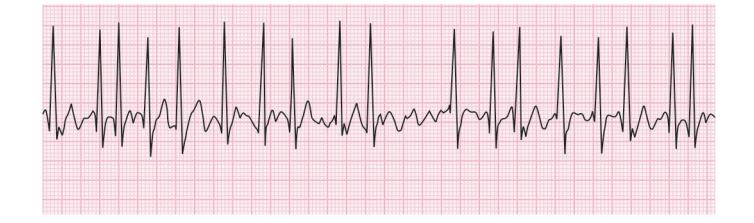
Answer
Atrial fibrillation.
VVK15-014
What is your diagnosis?
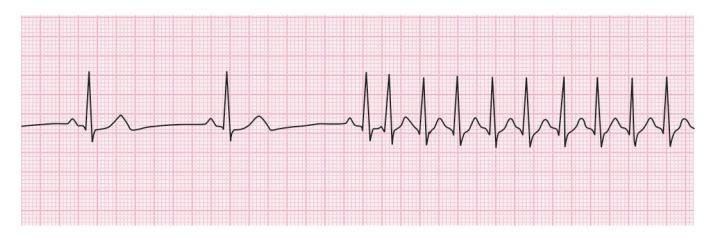
Answer
Onset of atrial fibrillation.
VVK15-015
What is your diagnosis?
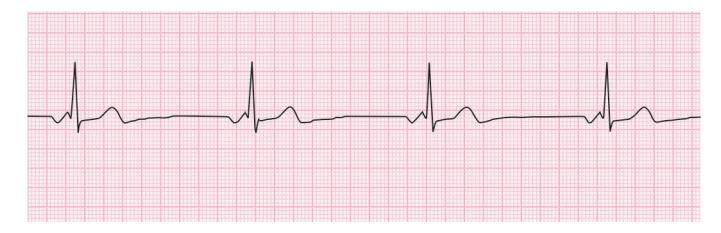
Answer
Low atrial rhythm (negative P waves).
VVK15-016
What is your diagnosis?
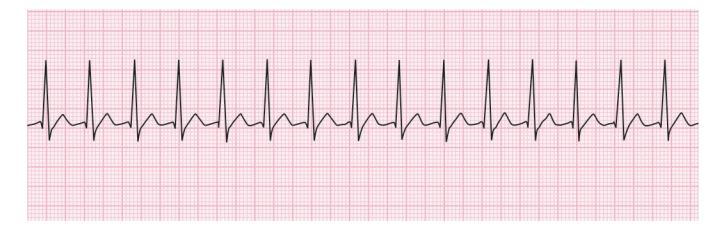
Answer
Supraventricular tachycardia.
VVK15-017
What does this indicate?
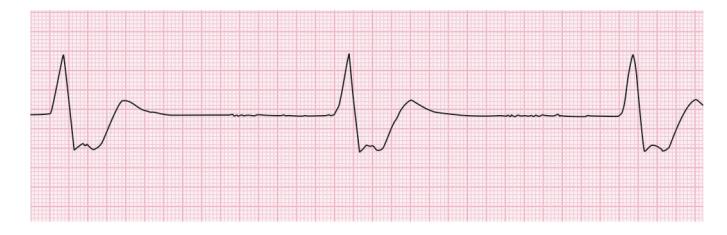
Answer
Sinus arrest with broad QRS complex.
VVK15-018
What is the most common cause?
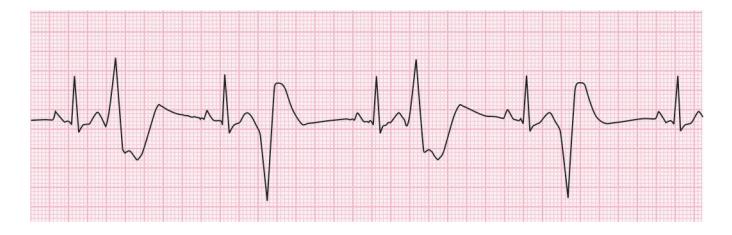
Answer
Polymorphic ventricular bigeminy.
VVK15-019
What is the diagnosis?
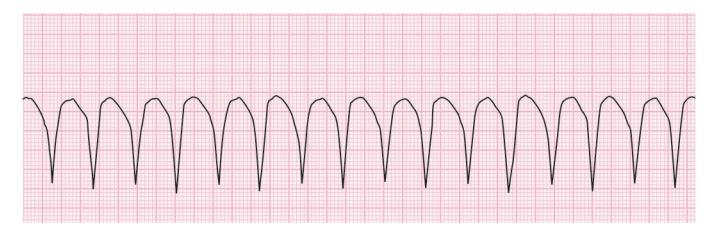
Answer
Broad QRS tachycardia—D/D ventricular tachycardia or Supraventricular tachycardia with aberrancy.
VVK15-020
What is the diagnosis?
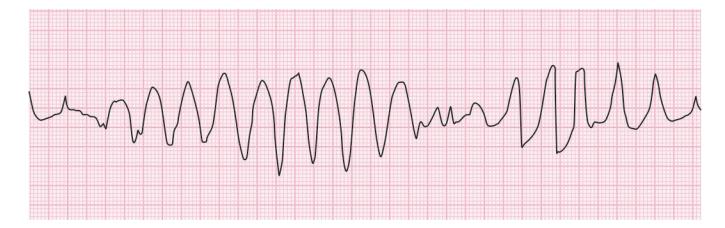
Answer
Torsades de pointes.
VVK15-021
What is the treatment?
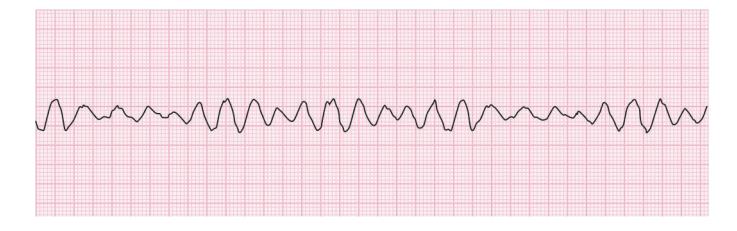
Answer
Immediate cardioversion and CPR.
VVK15-022
Could the child be alive?
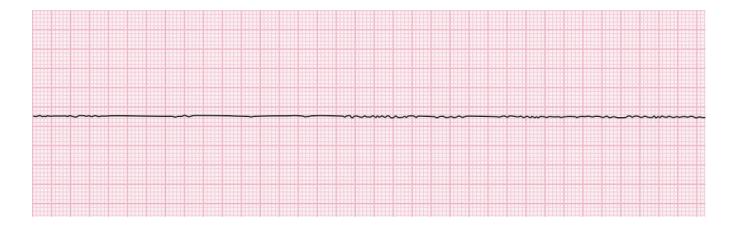
Answer
Yes, Hypothermia.
VVK15-023
Is this ECG normal? Why?
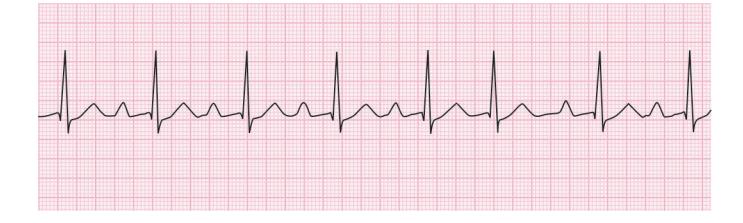
Answer
First degree heart block prolonged PR.
VVK15-024
What is the diagnosis?
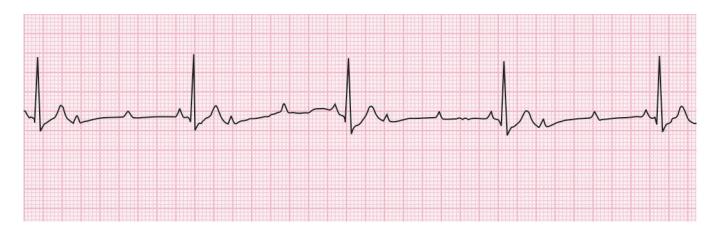
Answer
3:1 AV block with narrow QRS escape.
VVK15-025
What is the diagnosis?
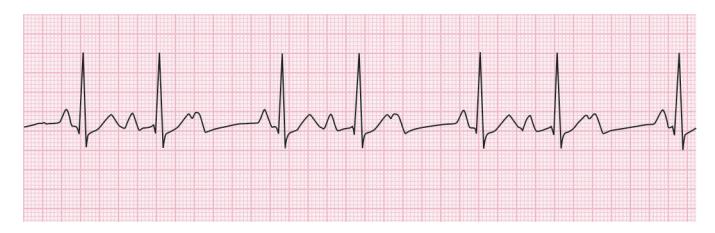
Answer
AV Wenckebach phenomenon.
VVK15-026
What is the diagnosis?
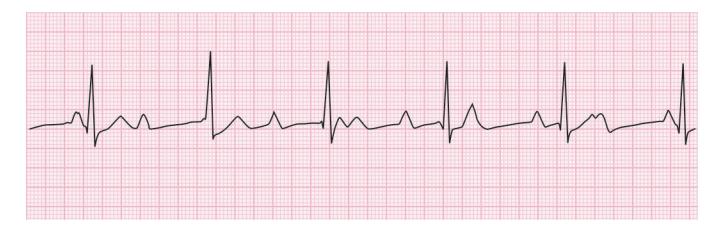
Answer
Type 2, IInd degree AV block.
VVK15-027
What is the diagnosis?
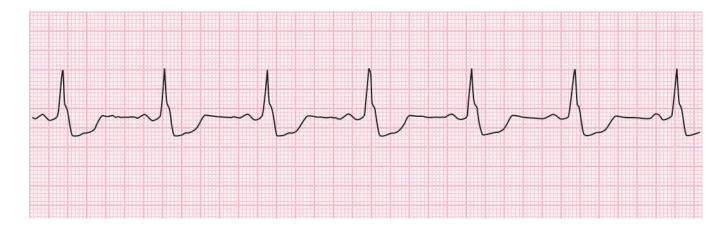
Answer
Horizontal ST depression
VVK15-028
What is abnormal with this ECG?
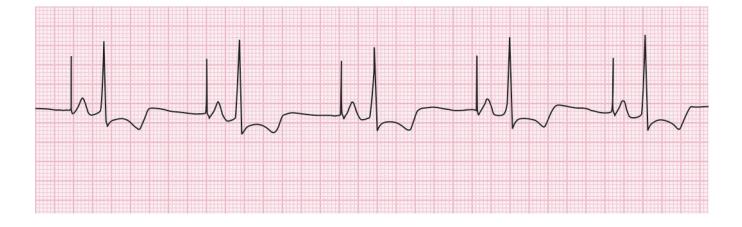
Answer
Atrial pacing.
VVK15-029
What is the diagnosis?
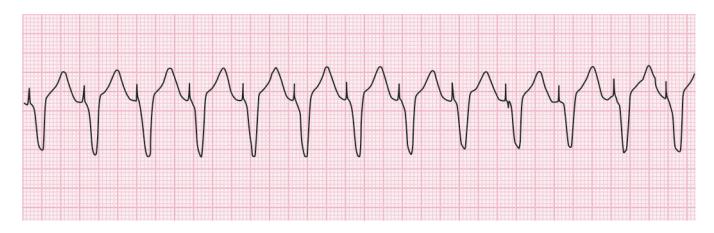
Answer
Ventricular paced rhythm.
VVK15-030
Healthy child has this ECG. What is the possible cause?
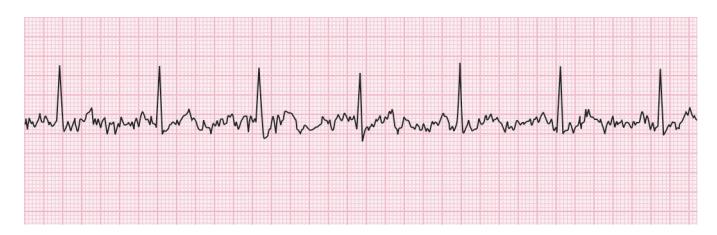
Answer
Muscle artefact: DDs—improper contact, hypothermia, shivering.
VVK15-031
A 8-year-old male is brought with history of sudden onset giddiness and fall, from which he recovered in a few seconds. His clinical examination was noted to be normal and his ECG is attached below.
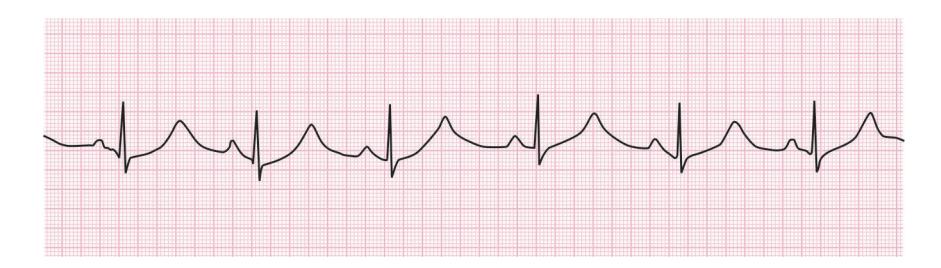
- a. Identify this ECG.
- b. What is the complication associated with this condition?
- c. What is the drug of choice for this diagnosis?
- d. Enlist 2 non-pharmacological treatments for the same.
Answer
- a. Prolonged QT syndrome.
- b. Torsades de pointes (polymorphic ventricular tachycardia).
- c. β blocker-propranolol
- d. Pacemaker, Implanted defibrillator.
VVK15-032
Match the following.
| Inherited condition | Heart abnormality |
|---|---|
| a. Down syndrome | i. Supravalvular aortic stenosis |
| b. Turner syndrome | ii. Hypertrophic cardiomyopathy |
| c. DiGeorge syndrome | iii. Cardiac rhabdomyoma |
| d. Marfan syndrome | iv. AVSD |
| e. William syndrome | v. Coarctation of aorta |
| f. Tuberous sclerosis | vi. Dissecting aortic aneurysm |
| g. Pompe disease | vii. Aortic arch abnormality |
Answer
| Inherited Condition | Heart abnormality |
|---|---|
| a. Down syndrome | • AVSD (iv) |
| b. Turner syndrome | • Coarctation of aorta (v) |
| c. DiGeorge syndrome | • Aortic arch abnormality (vii) |
| d. Marfan syndrome | • Dissecting aortic aneurysm (vi) |
| e. William syndrome | • Supravalvular aortic stenosis (i) |
| f. Tuberous sclerosis | • Cardiac rhabdomyoma (iii) |
| g. Pompe disease | • Hypertrophic cardiomyopathy (ii) |
VVK15-033
ECG diagnosis.
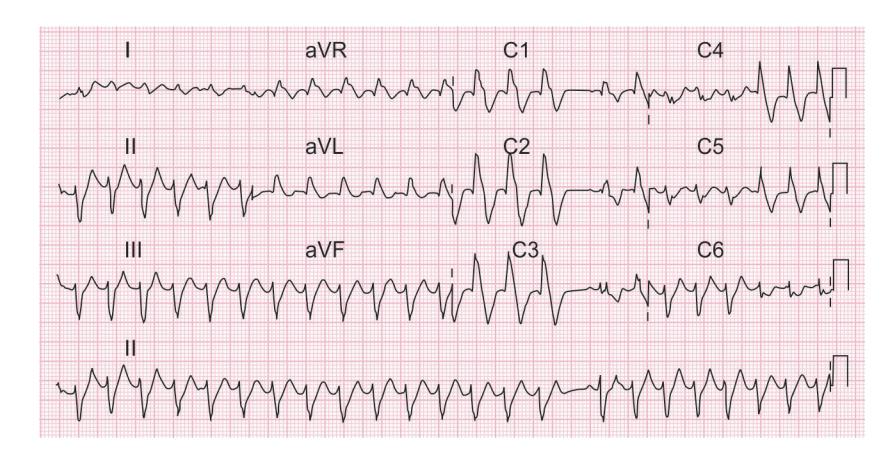
- a. What is the ECG diagnosis? Patients' pulse cannot be palpated
- b. What is the immediate management after initial stabilization?
- c. List four etiological causes of pulseless electrical activity (electricalmechanical-dissociation).
Answer
- a. Ventricular tachycardia, immediate treatment.
- b. Defibrillation.
- c. Hyperkalemia, hypothermia, hypovolemia, tension pneumothorax, hypoxia, pericardial tamponade, toxins, pulmonary thromboembolism.
VVK15-034
Please write the ECG event (waves and intervals) related to following cardiac event.
For example, p wave—atrial depolarization:
- a. Ventricular depolarization.
- b. Ventricular repolarization.
- c. Start of atrial depolarization to start of ventricular depolarization.
- d. Pause in ventricular activity before repolarization.
- e. Total time taken by ventricular depolarization and repolarization.
Answer
- a. QRS complex
- b. T wave
- c. PR interval
- d. ST segment
- e. QT interval.
VVK15-035
You examine a 4-month-old infant in your OPD. Baby was born at term to a primigravida mother with no antenatal concerns. The pediatrician hears a continuous murmur at the upper left sternal border. The peripheral pulses in all extremities are full and show widened pulse pressure.
- a. Which is the most likely diagnosis?
- b. Name a congenital infection which may be associated with this problem.
- c. What is the treatment for this infant?
- d. List two other causes of continuous murmur.
Answer
- a. Patent ductus arteriosus (PDA)
- b. Congenital rubella infection
- c. Surgical / coil ligation
- d. Other causes of continuous murmur:
- Aortico-pulmonary window defect
- Cervical venous hum
- Ruptured sinus of Valsalva aneurysm
- Coronary AV fistula
- Truncus arteriosus with increased pulmonary flow
VVK15-036
Match the following.
| Heart sounds | Associated disease / Cardiac abnormality |
|---|---|
| a. Loud S1 | i. Pulmonary valve stenosis |
| b. Soft S1 | ii. Aortic regurgitation |
| c. Loud P2 | iii. Aortic stenosis |
| d. Soft P2 | iv. Thyrotoxicosis |
| e. Reverse splitting of S2 | v. Pulmonary hypertension |
| f. S3 | vi. Mitral stenosis |
Answer
| Heart sounds | Associated disease / Cardiac abnormality |
|---|---|
| a. Loud S1 | • Thyrotoxicosis (iv) |
| b. Soft S1 | • Mitral stenosis (vi) |
| c. Loud P2 | • Pulmonary hypertension (v) |
| d. Soft P2 | • Pulmonary valve stenosis (i) |
| e. Reverse splitting of S2 | • Aortic stenosis (iii) |
| f. S3 | • Aortic regurgitation (ii) |
VVK15-037
A 6-week-old male infant is seen in pediatric emergency with an episode of cyanosis. Mother complains of similar episodes when the child wakes up in the morning or while crying. On examination the child is still cyanosed and has an ejection murmur heard over upper left sternal border and a single second heart sound.
- a. What is the most likely diagnosis?
- b. List three common syndrome/associations which can be associated with this condition.
- c. What is the characteristic ECG finding of this condition? The child has been stabilized in the emergency room.
- d. What is the surgical treatment for this abnormality?
Answer
- a. Tetralogy of Fallot (cyanotic spells / Tet spells).
- b. Down syndrome, DiGeorge syndrome, CHARGE, VACTERL.
- c. RAD (Right Axis Deviation), RVH (Right Ventricular Hypertrophy).
- d. Palliative BT shunt within few months of life; Corrective surgery at 4 to 12 months age.
VVK15-038
Study the ECG and answer the questions.
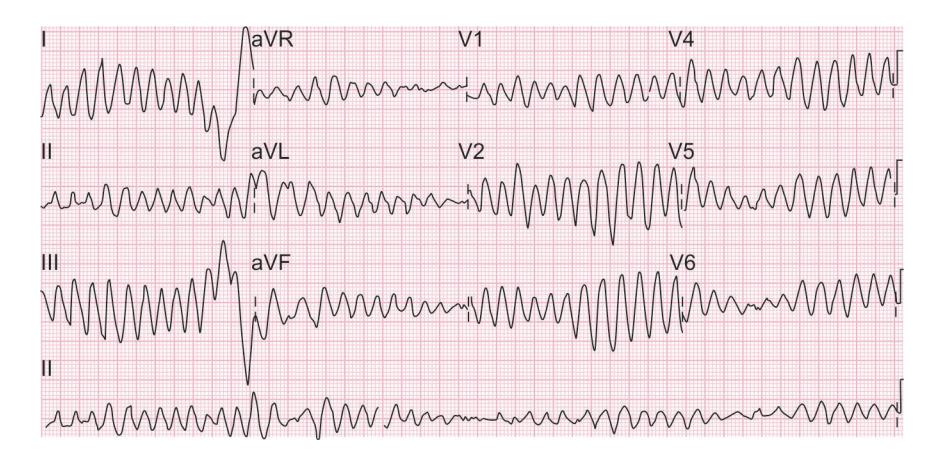
- a. What is the diagnosis?
- b. What is the treatment?
Answer
- a. Torsades de pointes
- b. β-blocker (propranolol), Pacemaker, Implanted defibrillator, IV Magnesium sulfate.
VVK15-039
A 10-year-old female child presents to pediatric OPD with decreased exercise tolerance. She is noted to have a grade three ejection systolic murmur best heard at the left upper sternal border and a grade three mid diastolic murmur at the lower left sternal border. The second heart sound is widely split and fixed. A right ventricular impulse is palpated.
- a. What is the most likely diagnosis?
- b. List 3 ECG finding of the commonest type of this abnormality.
- c. What is the definitive treatment of this abnormality?
- d. Is prophylaxis for infective endocarditis indicated?
- e. Name the syndrome associated with this heart condition caused by abnormality of the chromosomal 12.
Answer
- a. ASD (Atrial Septal Defect - ostium secundum).
- b. RAD, RSR' pattern in right precordial leads (or RBBB), RVH.
- c. Device closure / surgical closure.
- d. Not indicated.
- e. Holt-Oram syndrome.
VVK15-040
An 8-year-old child is seen by a pediatrician for a murmur. The pediatrician hears a loud systolic ejection murmur with a prominent systolic ejection click. The murmur decreases with the Valsalva maneuver. Both murmurs are heard best at the upper right sternal border.
- a. What is the most likely diagnosis?
- b. What is the ECG finding of this condition?
- c. What is the treatment for this abnormality?
- d. Name two conditions in which the murmur increases with the Valsalva maneuver.
Answer
- a. Aortic valve stenosis.
- b. LVH with strain pattern (inverted T wave in left precordial leads).
- c. Balloon valvuloplasty or aortic valve replacement.
- d. Hypertrophic obstructive cardiomyopathy (HOCM) and mitral valve prolapse (MVP).
VVK15-041
A sick 4-year-old is admitted in PICU for bilateral pneumonia. He is nil by mouth and is on ringer lactate. His electrolytes reveal Na 132 and K 8.5. An ECG is ordered.
- a. Enlist 4 ECG findings you would expect in this child.
- b. Enlist 3 steps in managing this patient.
- c. Outline the importance of interpretation of trans tubular potassium gradient (TTKG).
Answer
- a. Peaking / tenting of the T waves, Increased P-R interval, Flattening of the P wave, Widening of the QRS complex.
- b. Management steps:
- Stop all sources of additional potassium
- IV Calcium gluconate
- Combination of insulin and glucose
- Sodium bicarbonate (most efficacious in metabolic acidosis)
- Sodium polystyrene sulfonate (K exchange resin)
- Dialysis
- c.
. If TTKG in a hyperkalemic patient is , the likely cause is renal.
VVK15-042
An 8-month-old female infant presents to pediatric OPD with complaint of poor weight gain. She had 3 episodes of LRTI in past 3months. On examination, there is a pansystolic murmur heard over the left lower sternal border accompanied by a thrill.
-
a. What is the most likely cardiac diagnosis?
-
b. Enlist two differential diagnosis of pansystolic murmur.
-
c. What is the most common type based on location of the defect?
-
d. If this baby develops an associated early diastolic murmur with bounding pulses, what is the most likely location of the lesion?
-
e. Is a loud harsh, holosystolic murmur with thrill along the left lower sternal border suggestive of a large lesion in the diagnosis given above?
-
f. Lack of cardiac enlargement in a left to right shunt signifies the shunt is:
-
i. <2:1
-
ii. <1.75:1
-
iii. <1.5:1
-
iv. <1.2:1
-
g. A mid diastolic murmur at the mitral area suggests a shunt of:
-
i. >1.2:1
-
ii. >1.5:1
-
iii. >1.75:1
-
iv. >2:1
Answer
- a. VSD (Ventricular Septal Defect)
- b. Mitral Regurgitation (MR), Tricuspid Regurgitation (TR)
- c. Membranous (Perimembranous)
- d. Supracristal region (Subpulmonic VSD with aortic valve prolapse/regurgitation)
- e. No (Maladie de Roger - smaller defect produces louder murmur)
- f. ii. < 1.75:1
- g. iv. > 2:1
VVK15-043
Match the following:
| Cardiac abnormality | JVP abnormality |
|---|---|
| a. Pulmonary stenosis | i. Cannon a wave |
| b. Complete heart block | ii. Giant a wave |
| c. Tricuspid regurgitation | iii. Steep y descent |
| d. Constrictive pericarditis | iv. Large v wave |
Answer
| Cardiac abnormality | JVP abnormality |
|---|---|
| a. Pulmonary stenosis | • Giant a wave (ii) |
| b. Complete heart block | • Cannon a wave (i) |
| c. Tricuspid regurgitation | • Large v wave (iv) |
| d. Constrictive pericarditis | • Steep y descent (iii) |
VVK15-044
Given below is the chest X-ray of a neonate.
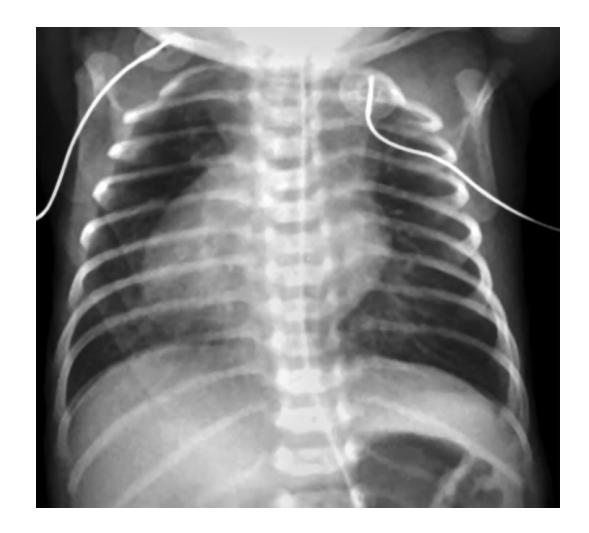
- a. What is the most likely radiological diagnosis?
- b. List two ECG findings associated with this diagnosis.
- c. What should be the placement of pads while defibrillating this patient?
Answer
- a. Dextrocardia with situs solitus.
- b. Inverted P wave in lead I, Inverted T wave in lead I, QRS complex is negative in lead I, Leads II and III are reversed.
- c. Instead of upper right and lower left, pads should be placed upper left and lower right (reversed placement).
VVK15-045
True false
Physiological (innocent) murmurs.
- a. Are heard in a small minority of children.
- b. Characteristically change in intensity with the position of the patient.
- c. Are more common in infants, who are small for their gestational age.
- d. May be associated with a thrill.
Answer
- a. False
- b. True
- c. False
- d. False
VVK15-046
Cardiac device.
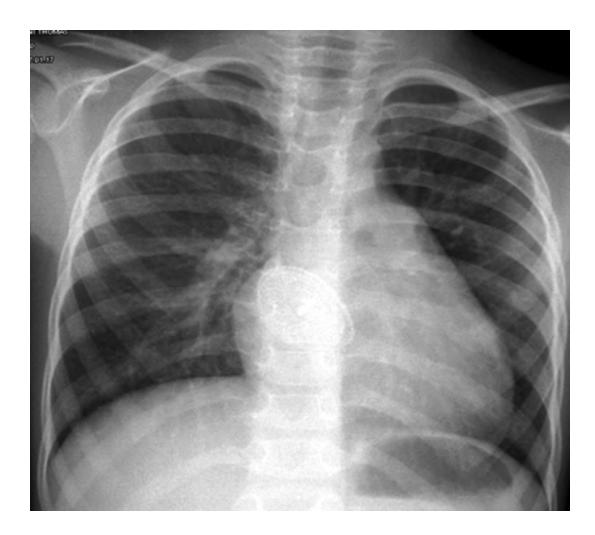
- a. Identify the procedure, where the device shown in this X-ray is used.
- b. List two indications of this procedure.
- c. What is the long-term non-cardiac complication, which may occur, if the device is not placed in asymptomatic children?
Answer
- a. ASD device closure (Amplatzer septal occluder).
- b. All symptomatic patients; Asymptomatic patients with a Qp : Qs ratio of at least 2 : 1.
- c. Paradoxical (right to left) systemic embolization (stroke / TIA).
VVK15-047
Cardiac device.
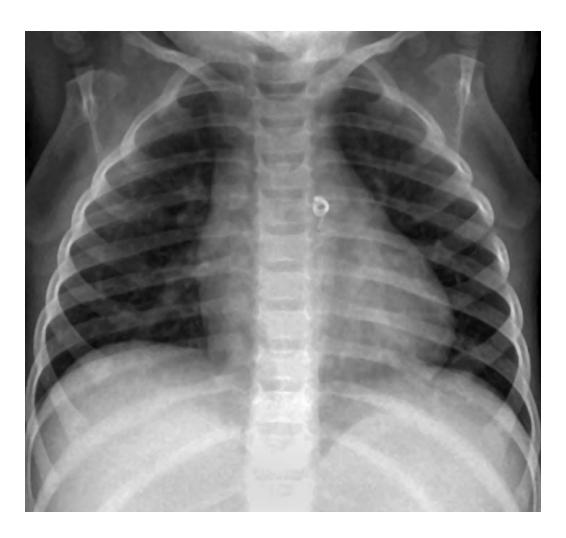
- a. Identify the procedure, where the device shown in this X-ray is used.
- b. List five complications, which may occur, if the device is not placed in children with the above diagnosis.
Answer
- a. PDA coil closure (or transcatheter PDA closure).
- b. Complications if not treated:
- Cardiac failure
- Infective endarteritis
- Aneurysmal dilatation of the pulmonary artery or ductus
- Calcification of the ductus
- Non-infective thrombosis with embolization
- Paradoxical emboli
- Pulmonary hypertension (Eisenmenger syndrome)