THG24-001
Fill in the blanks:
a. Visual acuity of newborn is ______.
b. Visual acuity reaches 6/6 or 6/9 by ______ years.
c. Eye coordination is usually achieved by ______ of age.
d. Tears are not present while crying until ______ of age.
e. Baby can fixate near objects by ______ of age.
Answer
- a. 6/120 (or 20/400)
- b. 2–3 years (reaches adult 6/6 by 5–6 years)
- c. 3–6 months of age
- d. 1–3 months of age
- e. 3 months of age (can fixate and follow 90°–180°)
THG24-002
Key developmental milestones in vision—match the following:
| No. | Age | Code | Visual Milestone |
|---|---|---|---|
| 1 | Birth | a | Follow rapidly moving objects |
| 2 | 4 weeks | b | Adjusts position to see objects |
| 3 | 12 weeks | c | Establishment of binocular vision |
| 4 | 16 weeks | d | Fixate somewhat and move 45° |
| 5 | 5 months | e | Fixate and move 90° |
| 6 | 6 months | f | Fixate intently and move 180° |
| 7 | 12 months | g | Excites when food is prepared |
Answer
- 1 — d (Birth: Fixate somewhat and move 45°)
- 2 — e (4 weeks: Fixate and move 90°)
- 3 — f (12 weeks: Fixate intently and move 180°)
- 4 — c (16 weeks: Establishment of binocular vision)
- 5 — g (5 months: Excites when food is prepared)
- 6 — b (6 months: Adjusts position to see objects)
- 7 — a (12 months: Follow rapidly moving objects)
THG24-003
Acuity of vision in various age groups and testing tools:
a. Acuity of vision—fill in the blanks:
- 1. 3 months ______
- 2. 12 months ______
- 3. 3 years ______
- 4. 4 years ______
- 5. 5–6 years ______
b. What are the usual testing methods?
- 1. 3–5 years
- 2. Above 6 years
Answer
- a. Visual Acuity by Age:
-
- 3 months: 6/60 (20/200)
-
- 12 months: 6/18 (20/60)
-
- 3 years: 6/12 (20/40)
-
- 4 years: 6/9 (20/30)
-
- 5–6 years: 6/6 (20/20)
-
- b. Testing Methods:
-
- 3–5 years: Tumbling E chart, HOTV test, Allen pictures, and Lea symbols.
-
- Above 6 years: Standard Snellen letters chart, Snellen numbers, and Landolt C chart.
-
THG24-004
Two children attending the neurology clinic were discovered to have visual field defects.

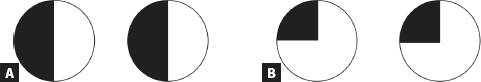
a. Damage to what part of the visual pathways would produce the visual field defect in 1?
b. Damage to what part of the visual pathways would produce the visual field defect in 2?
c. Damage to what part of the visual pathways would produce the visual field defect in A?
d. Damage to what part of the visual pathways would produce the visual field defect in B?
Answer
- a. Lesion at right optic nerve (produces total ipsilateral right eye blindness with loss of direct light reflex).
- b. Lesion at central optic chiasm (produces bitemporal hemianopia, e.g., craniopharyngioma / pituitary adenoma).
- c. Lesion at left optic tract / optic radiation (produces right homonymous hemianopia).
- d. Lesion in the temporal lobe optic radiation / Meyer's loop (produces superior homonymous quadrantanopia - "pie in the sky").
THG24-005
With respect to the extraocular muscles of the eye answer the following:
| Sl. no | Muscle | Nerve supply | Action with eye abducted | Action with eye adducted |
|---|---|---|---|---|
| 1. | Lateral rectus | |||
| 2. | Inferior rectus | |||
| 3. | Inferior oblique | |||
| 4. | Medial rectus | |||
| 5. | Superior rectus | |||
| 6. | Superior oblique |
Answer
| Sl. no | Muscle | Nerve Supply | Action with Eye Abducted | Action with Eye Adducted |
|---|---|---|---|---|
| 1. | Lateral rectus | VI (Abducens) | Abduction | Abduction |
| 2. | Inferior rectus | III (Oculomotor) | Depression | Extorsion |
| 3. | Inferior oblique | III (Oculomotor) | Extorsion | Elevation |
| 4. | Medial rectus | III (Oculomotor) | Adduction | Adduction |
| 5. | Superior rectus | III (Oculomotor) | Elevation | Intorsion |
| 6. | Superior oblique | IV (Trochlear) | Intorsion | Depression |
THG24-006
A 9-month-old female infant brought to family physician with parents having noticed that her eyes do not always seem to be looking in the same direction.
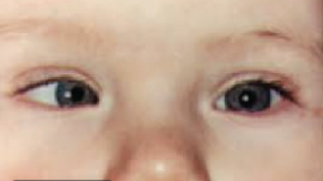
a. What does the child have?
b. Name screening tests of clinical examination.
c. What are its types?
Answer
- a. Right esotropia (Right convergent strabismus / squint)
- b. Hirschberg corneal light reflex test, cover-uncover test, alternate cover test, and Bruckner red reflex test.
- c. Concomitant (non-paralytic, angle of deviation constant in all directions) and Incomitant (paralytic, angle varies with gaze direction).
THG24-007
An ocular condition is shown:
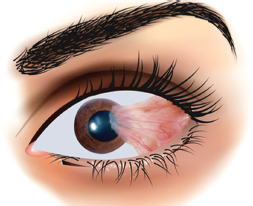
a. What is the diagnosis?
b. What is the typical area where it occurs?
c. What are the pathologic findings?
d. What is the risk factor?
e. What is the treatment?
Answer
- a. Pterygium
- b. Nasal interpalpebral bulbar conjunctiva extending onto the cornea
- c. Elastotic and hyaline degenerative changes in the subconjunctival connective tissue with fibrovascular proliferation
- d. Chronic exposure to ultraviolet (UV) radiation, sunlight, wind, and dry dusty environments
- e. Lubricating eye drops, UV protection sunglasses; surgical excision with conjunctival autograft if encroaching visual axis or causing astigmatism.
THG24-008
An ocular lesion is shown:
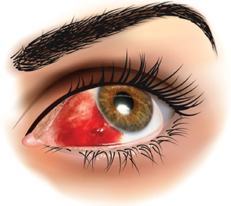
a. What is the diagnosis?
b. What are the causes (any four)?
c. What is the treatment?
Answer
- a. Subconjunctival hemorrhage
- b. Eye trauma/rubbing, Valsalva maneuvers (severe coughing, sneezing, vomiting, straining), acute conjunctivitis, bleeding disorders/thrombocytopenia, and systemic hypertension.
- c. Reassurance; cold compresses acutely; self-limiting condition resolving spontaneously within 1–2 weeks without active medication.
THG24-009
An inflammatory condition of the conjunctiva is shown:
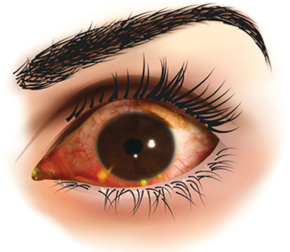
a. What is the diagnosis?
b. What is the pathogenesis behind this?
c. What are the causative factors?
d. What is the treatment?
Answer
- a. Phlyctenular keratoconjunctivitis
- b. Type IV (delayed-type) cell-mediated hypersensitivity reaction to foreign bacterial microbial antigens
- c. Staphylococcus aureus (blepharitis), Mycobacterium tuberculosis, and less commonly Chlamydia or intestinal parasites
- d. Short-course topical corticosteroids, topical antibiotic coverage, eyelid hygiene, and treatment of underlying systemic infection (e.g., anti-TB therapy if tubercular).
THG24-010
An ocular manifestation of a nutritional deficiency is shown:
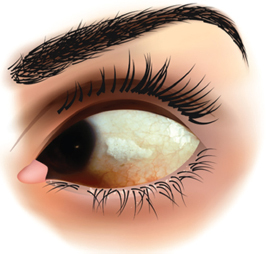
a. What do you see?
b. What is the diagnosis?
c. Name the earliest symptom of this condition.
d. How will you treat?
e. What are the prevention strategies?
Answer
- a. Bitot's spot (triangular, foamy, silvery-white keratinized patch on the bulbar conjunctiva near the limbus).
- b. Vitamin A deficiency (Xerophthalmia stage X1B)
- c. Night blindness (Nyctalopia - stage XN)
- d. Treatment Protocol: Oral Vitamin A (200,000 IU for
, 100,000 IU for 6–12 months, 50,000 IU for ): - Day 1: First dose immediately at diagnosis
- Day 2: Second dose next day
- Day 14–28: Third dose 2–4 weeks later
- e. Prevention Strategies: Promotion of vitamin A-rich foods (green leafy vegetables, yellow-orange fruits, dairy), universal biennial mega-dose vitamin A supplementation in children 9–59 months, and food fortification.
THG24-011
Around 50 children in neighborhood have similar symptoms of pain, redness, and tearing of eyes with findings of subconjunctival hemorrhages, follicles, and chemosis.
a. What is the diagnosis?
b. What are the usual causative organisms?
c. What is the treatment?
Answer
- a. Acute hemorrhagic conjunctivitis (Epidemic conjunctivitis)
- b. Enterovirus 70 (EV70) and Coxsackievirus A24 variant (CA24v) (also Adenovirus)
- c. Supportive care (cold compresses, preservative-free artificial tears, hygiene to prevent spread); self-limiting over 5–7 days.
THG24-012
A 4-year-old girl presented with right red eye, and matting of eyelids on awakening; No history of fever, rhinorrhea; on examination there is right bulbar and tarsal conjunctival erythema with a small amount of mucopurulent discharge at the corner of the right eye. There is purulent fluid visible behind her right tympanic membrane.
a. What is the probable diagnosis?
b. What is the most common organism?
c. What are the other organisms?
d. ______ and ______ are helpful in differentiating specific types.
e. What is the treatment outline?
Answer
- a. Acute purulent conjunctivitis with otitis media (Conjunctivitis–otitis syndrome)
- b. Nontypeable Haemophilus influenzae (causes >70–80% of conjunctivitis-otitis syndrome)
- c. Streptococcus pneumoniae and Moraxella catarrhalis (also Staphylococcus aureus)
- d. Conjunctival smear and culture are helpful in differentiating specific types.
- e. Systemic oral antibiotics (oral Co-amoxiclav / Amoxicillin to cover both otitis media and conjunctivitis) along with warm compresses and topical antibiotic eye drops.
THG24-013
A 7-month-old infant brought to emergency room (ER) with inconsolable crying, rubbing of eyes, photophobia, and on examination mild injection of his left conjunctiva and focal haze of cornea of left eye.
a. What is the diagnosis?
b. What are the causative factors?
c. Most serious infection is due to which organism?
d. What are the complications?
e. What is the treatment?
Answer
- a. Corneal ulcer (Microbial keratitis) / Corneal abrasion
- b. Accidental ocular trauma (fingernail scratch, foreign body), contact lens use, and eyelid malposition.
- c. Pseudomonas aeruginosa
- d. Corneal perforation, endophthalmitis, anterior segment synechiae, dense corneal scarring (leukoma), and permanent visual loss.
- e. Urgent ophthalmology consult, intensive broad-spectrum fortified topical antibiotics (e.g., fortified tobramycin + cefazolin/vancomycin or fluoroquinolones), cycloplegic eye drops (cyclopentolate) for pain relief, and strictly avoiding patching.
THG24-014
Child brought to outpatient department with a 3-day history of low-grade fever and a rash around the right eye.
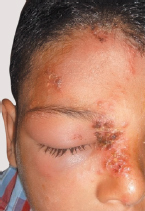
a. What is the most likely diagnosis? What is the causative organism?
b. What is the mechanism?
c. Severe manifestation and recurrence seen in which conditions (any two)?
d. What are the complications in eye (any two)?
e. What is the treatment, drug of choice, and dosage?
Answer
- a. Herpes zoster ophthalmicus (HZO); Causative organism: Varicella-Zoster Virus (VZV).
- b. Reactivation of latent VZV residing in the trigeminal ganglion involving the ophthalmic (
) branch. - c. Immunocompromised states (HIV infection, hematological malignancies, post-transplant, or high-dose systemic immunosuppression).
- d. Neurotrophic keratopathy / dendritic keratitis, anterior uveitis, secondary glaucoma, scleritis, optic neuritis, and post-herpetic neuralgia.
- e. Oral Acyclovir
(maximum ) 4–5 times daily for 7 days (or IV Acyclovir if severe/disseminated).
THG24-015
An 8-year-old male presented with 3 days of fever and increased swelling of the eyelid. Physical examination revealed a warm and violaceous discoloration and swelling of the left eyelid which extended to the nose and limited movement of the left eyeball and decreased visual acuity and proptosis of left eye.
a. What is the diagnosis?
b. What is the triad of this condition?
c. What is the most common cause?
d. Which organisms are responsible?
e. What are the complications?
f. What is the imaging of choice?
Answer
- a. Orbital cellulitis (Postseptal cellulitis)
- b. Triad: Proptosis, painful limitation of extraocular eye movements (ophthalmoplegia), and decreased visual acuity.
- c. Direct extension from bacterial acute/chronic ethmoid sinusitis (via thin lamina papyracea).
- d. Staphylococcus aureus (including MRSA), Streptococcus pneumoniae, Streptococcus pyogenes (Group A Strep), and anaerobes.
- e. Subperiosteal/orbital abscess, cavernous sinus thrombosis, optic neuritis with permanent blindness, meningitis, and brain abscess.
- f. Contrast-enhanced CT (CECT) of the orbit and paranasal sinuses.
THG24-016
A 16-month-old male, woke up with a temperature of 37.7°C. Physical examination revealed erythema and swelling of the right eyelid. There was no evidence of ophthalmoplegia, proptosis, or decreased visual acuity.
a. What is the diagnosis?
b. What are the causes (any two)?
c. Which organisms are responsible (any two)?
Answer
- a. Preseptal cellulitis (Periorbital cellulitis)
- b. Superficial skin trauma/insect bite, local skin infections (hordeolum/chalazion, dacryocystitis), and upper respiratory tract infections / sinusitis.
- c. Staphylococcus aureus, Streptococcus pyogenes (Group A Strep), and Streptococcus pneumoniae (also Haemophilus influenzae type b in unvaccinated).
THG24-017
A 6-year-old boy presented with proptosis, painful limitation of movement of right eye, and decreased visual acuity.
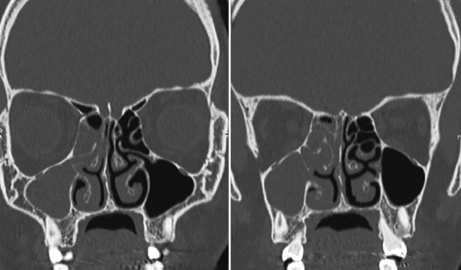
a. What is the CT scan finding?
b. What is the diagnosis?
c. What is the most common cause?
d. What are the causative pathogenic organisms (any three)?
e. What are the complications (any three)?
f. What is the investigation of choice?
g. What are the principles of management?
Answer
- a. Opacification of right maxillary and ethmoid sinuses with soft-tissue inflammatory subperiosteal collection/abscess in the medial orbital wall.
- b. Orbital cellulitis with subperiosteal abscess secondary to paranasal sinusitis.
- c. Paranasal sinusitis (ethmoid and maxillary sinusitis).
- d. Staphylococcus aureus (MSSA/MRSA), Streptococcus pneumoniae, Group A Streptococcus (S. pyogenes), and mixed anaerobes.
- e. Cavernous sinus thrombosis, intracranial abscess / meningitis, subperiosteal orbital abscess, and permanent loss of vision from compressive optic neuropathy.
- f. Contrast-enhanced CT scan (CECT) of orbit, brain, and paranasal sinuses.
- g. Inpatient hospital admission, empirical broad-spectrum IV antibiotics (e.g., Ceftriaxone + Vancomycin
Metronidazole), ENT/ophthalmology evaluation, and surgical drainage of sinus/subperiosteal abscess if indicated.
THG24-018
Tender swelling:
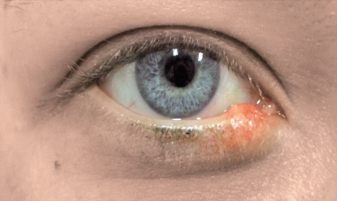
a. What is the diagnosis?
b. Mention the usual agent.
c. What are the types?
d. What is the treatment?
e. What is the complication if left untreated?
Answer
- a. Hordeolum (Stye)
- b. Staphylococcus aureus
- c. External hordeolum (infection of glands of Zeis or Moll at eyelash follicle) and Internal hordeolum (suppurative infection of Meibomian gland).
- d. Warm compresses for 10–15 minutes 3–4 times daily, topical antibiotic eye ointment/drops (e.g., Erythromycin, Bacitracin, Tobramycin), and incision and drainage if pointing/refractory.
- e. Progression to preseptal cellulitis or secondary chronic chalazion formation.
THG24-019
Nontender swelling:
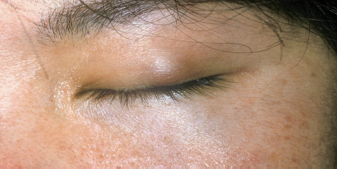
a. What is the diagnosis?
b. This occurs due to?
c. What is the usual outcome?
d. What is the indication for surgery—excision?
e. What is the indication for systemic macrolide?
Answer
- a. Chalazion
- b. Chronic non-infectious granulomatous lipogranulomatous inflammation caused by obstruction of a Meibomian gland duct.
- c. Spontaneous resolution over weeks to months in many cases.
- d. Cosmetic disfigurement, persistent large lesions failing conservative management, or lesions causing induced astigmatism and visual distortion.
- e. Associated underlying chronic blepharitis, acne rosacea, or recurrent multiple chalazia.
THG24-020
An ocular congenital anomaly is shown:
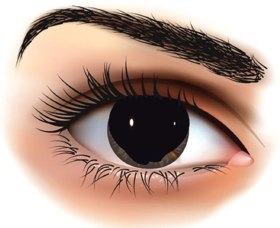
a. What is the defect?
b. What are the two forms?
c. Caused by defect in ______ gene on chromosome ______.
d. What are the associated ocular defects (any four)?
e. What is the tumor associated with this condition and in which form?
Answer
- a. Aniridia (congenital absence/hypoplasia of the iris)
- b. Familial (autosomal dominant, ~two-thirds) and Sporadic (isolated or part of WAGR syndrome, ~one-third).
- c. PAX6 gene on chromosome 11p13.
- d. Foveal/macular hypoplasia, nystagmus, optic nerve hypoplasia, congenital/juvenile cataract, secondary glaucoma, and keratopathy/pannus.
- e. Wilms tumor (in sporadic aniridia associated with WAGR syndrome: Wilms tumor, Aniridia, Genitourinary anomalies, and Range of developmental delay).
THG24-021
A 2-year-old toddler boy has symptoms of increased tearing, increased sensitivity to light (photophobia), and eyelid squeezing (blepharospasm) of right eye. On examination right cornea is enlarged and edematous.
a. What is the diagnosis?
b. Symptoms are attributed to ______.
c. What are the ocular signs?
d. What are the other associated ocular anomalies?
e. What are the predisposing causes of this condition?
f. What is the treatment modality of choice?
Answer
- a. Primary congenital / infantile glaucoma (Buphthalmos)
- b. Corneal epithelial edema and irritation from elevated intraocular pressure.
- c. Triad of epiphora, photophobia, and blepharospasm; enlarged corneal diameter (
), cloudy/hazy cornea, Haab's striae (horizontal breaks in Descemet's membrane), and pathologically increased optic disc cupping. - d. Aniridia, Sturge–Weber syndrome, Neurofibromatosis type 1, Peters anomaly, and Axenfeld–Rieger syndrome.
- e. Dysgenesis of trabecular meshwork (trabeculodysgenesis) causing impaired aqueous outflow.
- f. Surgical intervention (Goniotomy or Trabeculotomy
Trabeculectomy).
THG24-022
Infant’s eye viewed through ophthalmoscope:
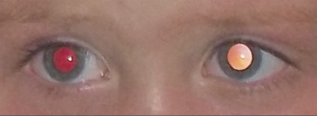
a. What is this test called?
b. How do you perform the test?
c. What do you observe in this infant?
d. What is your interpretation?
e. Mention the likely causes for what you observe in left eye (any four).
Answer
- a. Red reflex examination (Bruckner test)
- b. In a darkened room, view both eyes simultaneously through a direct ophthalmoscope set at "0" diopter from a distance of approximately 18 inches (45 cm).
- c. Normal symmetrical red-orange reflex in the right eye, and an abnormal white/opaque reflex in the left eye.
- d. Leukocoria (white pupillary reflex / amaurotic cat's eye reflex) of the left eye.
- e. Causes of Leukocoria:
- Retinoblastoma
- Congenital cataract
- Persistent fetal vasculature (PFV / PHPV)
- Retinopathy of prematurity (Stage 5 cicatricial ROP)
- Coats disease
- Ocular toxocariasis (larval granulomatosis)
- Retinal detachment / Coloboma
THG24-023
Systemic conditions and eye disorders—match the following:
| No. | Systemic Condition | Code | Ocular Manifestation |
|---|---|---|---|
| 1 | Wilms tumor | a | Lisch nodules |
| 2 | Neurofibromatosis | b | Cataract |
| 3 | Marfan syndrome | c | Aniridia |
| 4 | Galactosemia | d | Ectopia lentis |
Answer
- 1 — c (Wilms tumor: Aniridia in WAGR syndrome)
- 2 — a (Neurofibromatosis: Lisch nodules)
- 3 — d (Marfan syndrome: Ectopia lentis - superotemporal subluxation)
- 4 — b (Galactosemia: Oil-drop cataract)
THG24-024
Hereditary pattern and eye conditions—match the following:
| No. | Eye Condition | Code | Inheritance / Epidemiology |
|---|---|---|---|
| 1 | Congenital cataract | a | Mostly sporadic and nearly 10% autosomal recessive |
| 2 | Retinitis pigmentosa | b | Most common is autosomal dominant |
| 3 | Glaucoma | c | Usually X-linked |
| 4 | Oculocutaneous albinism | d | Nonheritable forms 60% and heritable forms 40% |
| 5 | Ocular albinism | e | Autosomal recessive |
| 6 | Retinoblastoma | f | Sporadic, autosomal dominant, autosomal recessive, and X-linked |
Answer
- 1 — b (Congenital cataract: Most common inherited form is autosomal dominant)
- 2 — f (Retinitis pigmentosa: Heterogeneous—sporadic, AD, AR, and X-linked)
- 3 — a (Congenital glaucoma: Mostly sporadic, ~10% autosomal recessive [CYP1B1])
- 4 — e (Oculocutaneous albinism: Autosomal recessive [TYR, OCA2])
- 5 — c (Ocular albinism: Usually X-linked recessive [GPR143])
- 6 — d (Retinoblastoma: Non-heritable somatic 60%, heritable germline 40%)
THG24-025
A 7-year-old child came with clumsiness in walking and history of recurrent sinopulmonary infections.
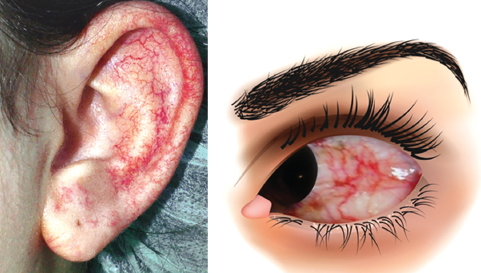
a. What do you see?
b. What is the probable diagnosis?
c. What is the mode of inheritance?
d. Which chromosomal is involved?
e. What is the usual clinical presentation?
f. What are the laboratory abnormalities?
g. What are the complications?
Answer
- a. Bulbar conjunctival and pinna cutaneous telangiectasias (dilated venules).
- b. Ataxia–telangiectasia (Louis–Bar syndrome)
- c. Autosomal recessive
- d. Chromosome 11q22.3 (ATM gene)
- e. Progressive cerebellar ataxia in toddler years, followed by oculocutaneous telangiectasia by 3–6 years, oculomotor apraxia, choreoathetosis, and recurrent sinopulmonary infections.
- f. Markedly elevated serum alpha-fetoprotein (AFP), low/undetectable serum IgA, IgG2, and IgE, lymphopenia, and increased chromosomal breakage upon radiation.
- g. Severe bronchiectasis, respiratory failure, and high risk of malignancies (lymphomas, leukemias).
THG24-026
This is the eye of a 7-year-old boy admitted with acute liver cell failure with hemolytic anemia.
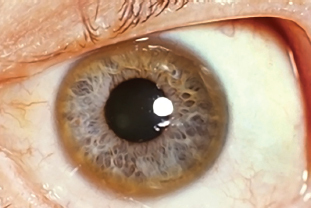
a. What abnormality is seen?
b. What is the most likely clinical diagnosis?
c. Mention other conditions in which this abnormality is seen (any four).
d. What is the mode of inheritance for the most likely clinical diagnosis?
e. What are the relevant investigations you will do to usually confirm diagnosis?
f. What action would you take regarding the rest of family?
Answer
- a. Kayser–Fleischer (KF) ring (brownish-green copper deposition in Descemet's membrane at corneal periphery).
- b. Wilson disease (Hepatolenticular degeneration)
- c. Primary biliary cholangitis, chronic cholestatic liver disease/cirrhosis, neonatal cholestasis, autoimmune hepatitis, and intraocular copper foreign body (chalcosis lentis).
- d. Autosomal recessive (ATP7B gene)
- e. Slit-lamp biomicroscopy, serum ceruloplasmin (<20 mg/dL), 24-hour urinary copper excretion (>100 µg/day), liver function tests, and ATP7B genetic testing.
- f. Screen all first-degree siblings with clinical exam, slit-lamp exam, serum ceruloplasmin, and urinary copper excretion (or targeted genetic testing).
THG24-027
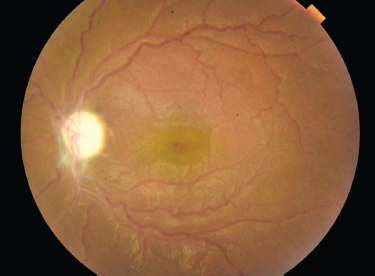
Describe the fundus images. In what condition it is seen?
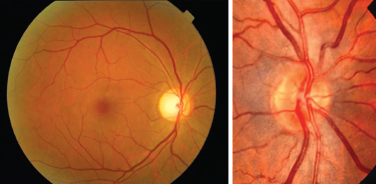
Answer
- Optic Disc: Sharp, well-demarcated margins; normal pinkish-orange color; healthy neural rim with normal physiological cup (cup-to-disc ratio <0.3).
- Retinal Vessels: Normal course, caliber, and branching; normal arteriovenous ratio (2:3); absence of AV crossing changes, copper-wiring, or vascular tortuosity.
- Macula & Background: Distinct foveal reflex; uniform orange-red background; absence of hemorrhages, hard/soft exudates, drusen, or pigmentation.
- Interpretation: Normal fundus.
THG24-028
A fundus finding is shown:
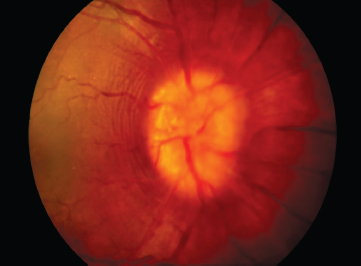
a. Identify the image.
b. What may be the accompanying clinical manifestations?
c. What are common causes (at least four)
d. What is the differential diagnosis?
Answer
- a. Papilledema (bilateral optic disc edema secondary to raised intracranial pressure).
- b. Headache (worse in morning), nausea, vomiting, transient visual obscurations, horizontal diplopia (6th nerve palsy), and altered sensorium.
- c. Space-occupying lesions / brain tumors, obstructive hydrocephalus, idiopathic intracranial hypertension (pseudotumor cerebri), cerebral venous sinus thrombosis, and meningitis/encephalitis.
- d. Papillitis (optic neuritis), pseudopapilledema (optic disc drusen), malignant hypertensive retinopathy, and central retinal vein occlusion.
THG24-029
A fundus finding is shown:
a. Describe the fundus image.
b. In what condition it is seen?
c. Name two principal causes of this condition in children.
d. What are the two main types based on ophthalmoscopic appearance?
Answer
- a. Pale, chalky-white optic disc with sharply demarcated margins and attenuated retinal vasculature.
- b. Optic atrophy
- c. Intracranial tumors (craniopharyngioma, optic pathway glioma), congenital/chronic hydrocephalus, and hereditary optic neuropathies (Leber hereditary optic neuropathy, dominant optic atrophy).
- d. Primary optic atrophy (chalky white with sharp margins) and Secondary optic atrophy (dirty yellow-gray with indistinct margins due to preceding papilledema/papillitis).
THG24-030
Acute loss of vision in a 15-year-old child—fundus image:
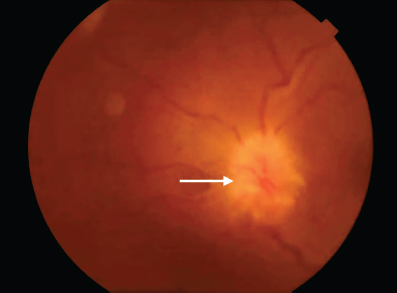
a. What do you see?
b. What is the likely diagnosis?
c. Mention other expected symptoms (any two).
d. Name two infectious diseases/two demyelinating disorders/two toxic or nutritional conditions that may cause this condition.
e. Which drug is used in treatment?
Answer
- a. Hyperemic, swollen optic disc with blurred margins and dilated surrounding capillary vessels (Papillitis).
- b. Acute optic neuritis
- c. Retrobulbar ocular pain aggravated by eye movements, impaired color vision (dyschromatopsia), decreased contrast sensitivity, and relative afferent pupillary defect (RAPD / Marcus Gunn pupil).
- d. Etiologies:
- Demyelinating: Multiple sclerosis, MOG-antibody-associated disease (MOGAD), Neuromyelitis optica spectrum disorder (NMOSD), ADEM.
- Infectious: Tuberculosis, Bartonella (Cat-scratch disease / neuroretinitis), Lyme disease, Syphilis, HIV.
- Toxic/Nutritional: Vitamin B₁₂ deficiency, Methanol poisoning, Ethambutol toxicity.
- e. High-dose Intravenous Methylprednisolone (30 mg/kg/day or 1 g/day for 3–5 days) followed by oral corticosteroid taper.
THG24-031
A fundus photograph is shown:
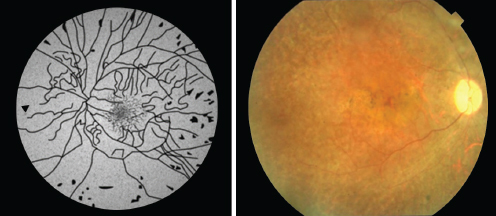
a. What is the likely clinical diagnosis?
b. What are the modes of inheritance?
c. What are the visual defects associated with the same (any three)?
d. Name clinical conditions associated with similar fundus image (any three).
Answer
- a. Retinitis pigmentosa
- b. Autosomal recessive (most common), Autosomal dominant, and X-linked recessive.
- c. Night blindness (nyctalopia), progressive peripheral visual field constriction (tunnel/tubular vision), and loss of central visual acuity in advanced stages.
- d. Associated Syndromes:
- Bardet–Biedl syndrome
- Usher syndrome (sensorineural deafness + RP)
- Refsum disease
- Kearns–Sayre syndrome
- Abetalipoproteinemia
- Neuronal ceroid lipofuscinosis
THG24-032
Retinitis pigmentosa—regarding prognosis and inheritance. Match the following:
| No. | Inheritance Pattern | Code | Clinical Prognosis |
|---|---|---|---|
| 1 | X-linked | a | Favorable prognosis with central vision preserved up to 5th–6th decade |
| 2 | Autosomal recessive | b | Best prognosis with central visual acuity beyond the 6th decade |
| 3 | Autosomal dominant | c | Worst prognosis with severe visual loss beyond 4th decade |
Answer
- 1 — c (X-linked: Worst prognosis with severe early visual loss by 3rd–4th decade)
- 2 — a (Autosomal recessive: Intermediate/favorable prognosis with central vision preserved up to 5th–6th decade)
- 3 — b (Autosomal dominant: Best prognosis with central visual acuity preserved beyond 6th decade)
THG24-033
Retinitis pigmentosa—systemic associations (mention True or False):
a. Bardet–Biedl syndrome
b. Refsum disease
c. Usher disease
d. Stickler’s syndrome
Answer
- a. True (Bardet–Biedl syndrome is associated with pigmentary retinopathy)
- b. True (Refsum disease is associated with retinitis pigmentosa)
- c. True (Usher syndrome is congenital SNHL + retinitis pigmentosa)
- d. False (Stickler syndrome is associated with high myopia and retinal detachment, NOT retinitis pigmentosa)
THG24-034
A pediatric intraocular tumor is shown:
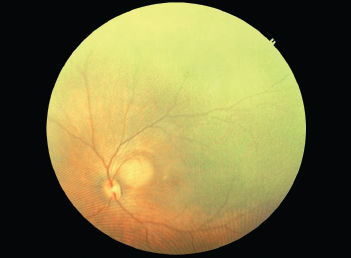
a. What is the likely diagnosis?
b. What are the two patterns of transmission?
c. What is the initial clinical sign? And how it occurs?
d. What is the second most common clinical sign?
e. What investigations you will do to confirm diagnosis?
Answer
- a. Retinoblastoma
- b. Heritable / germline (40%, bilateral/multifocal, RB1 gene mutation) and Non-heritable / somatic (60%, unilateral, unifocal).
- c. Leukocoria (white pupillary reflex) due to reflection of light off the whitish vascularized tumor mass.
- d. Strabismus (squint due to visual axis obstruction)
- e. Ocular ultrasonography (B-scan showing calcified mass), contrast-enhanced MRI orbit and brain (to assess optic nerve and intracranial pineal trilateral extension), and RB1 genetic testing.
THG24-035
A metabolic fundus finding is shown:
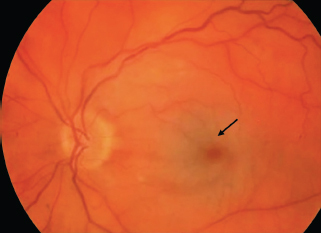
a. What do you see in fundus?
b. What is the explanation for this finding in fundus?
c. Name five conditions in which similar findings are seen in fundus.
d. What are the possible conditions with HSM (any two)?
Answer
- a. Cherry-red spot at the fovea centralis.
- b. Lipid accumulation in the multilayered retinal ganglion cells around the macula makes the parafoveal retina pale, opaque, and whitish. In contrast, the fovea centralis lacks ganglion cells, allowing the underlying red vascular choroid to shine through sharply.
- c. Conditions with Cherry-Red Spot:
- Tay–Sachs disease (
gangliosidosis) - Niemann–Pick disease (Types A and B)
gangliosidosis - Sandhoff disease
- Sialidosis (Mucolipidosis type I / cherry-red spot myoclonus syndrome)
- Farber disease
- Central retinal artery occlusion (CRAO)
- Tay–Sachs disease (
- d. Conditions with hepatosplenomegaly: Niemann–Pick disease,
gangliosidosis, Sandhoff disease, and Gaucher disease. (Note: Tay–Sachs disease has NO hepatosplenomegaly).
THG24-036
Diseases associated with cherry red spot—mention their inheritance pattern:
| No. | Disease | Inheritance Pattern |
|---|---|---|
| 1 | GM1 gangliosidosis | |
| 2 | GM2 gangliosidosis | |
| 3 | Mucolipidosis | |
| 4 | Niemann–Pick disease | |
| 5 | Farber disease |
Answer
| No. | Disease | Inheritance Pattern |
|---|---|---|
| 1 | GM1 gangliosidosis | Autosomal recessive (GLB1 gene) |
| 2 | GM2 gangliosidosis (Tay–Sachs / Sandhoff) | Autosomal recessive (HEXA / HEXB genes) |
| 3 | Mucolipidosis (Sialidosis) | Autosomal recessive (NEU1 gene) |
| 4 | Niemann–Pick disease (Types A / B / C) | Autosomal recessive (SMPD1 / NPC1 genes) |
| 5 | Farber disease | Autosomal recessive (ASAH1 gene) |
THG24-037
Fundus image of preterm baby born at 28 weeks of gestation:
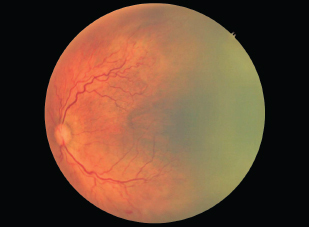
a. What is the diagnosis?
b. What are the risk factors (other than prematurity) associated with this condition (any four)?
c. What is the ideal age at which initial screening ophthalmic examination should be performed in this child?
d. What is the ideal treatment to reduce severe complications of progressive disease?
e. What is screening criteria for screening for this condition according to Rashtriya Bal Swasthya Karyakram (RBSK) (Government of India)?
Answer
- a. Retinopathy of prematurity (ROP)
- b. Unmonitored supplemental oxygen therapy, respiratory distress syndrome, mechanical ventilation, sepsis, blood transfusions, intraventricular hemorrhage, and poor postnatal weight gain.
- c. At 4 weeks of postnatal chronological age or 31–32 weeks postmenstrual age (whichever is later).
- d. Laser photocoagulation of avascular peripheral retina or intravitreal anti-VEGF injection (e.g., Ranibizumab/Bevacizumab).
- e. RBSK Screening Criteria (Government of India):
- Birth weight
OR gestational age - Gestational age 34–36 weeks with risk factors (cardiorespiratory instability, sepsis, prolonged oxygen exposure, inotropic support) as determined by pediatrician.
- Birth weight
THG24-038
A retinal fundus image is shown:
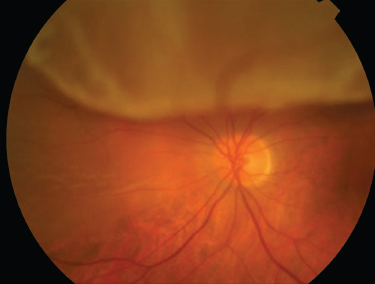
a. What is the diagnosis?
b. What are the types?
c. Mention the causes (any five).
d. What are the usual clinical signs?
e. Mention the investigations to determine cause and appropriate treatment.
Answer
- a. Retinal detachment
- b. Types: Rhegmatogenous, Tractional, and Exudative (serous).
- c. Causes:
- Rhegmatogenous: Ocular trauma, high myopia, post-cataract surgery, retinopathy of prematurity.
- Tractional: Advanced diabetic retinopathy, ROP Stage 4/5, sickle cell retinopathy.
- Exudative: Coats disease, retinoblastoma, severe ocular inflammation/uveitis, choroidal hemangioma.
- d. Flashes of light (photopsia), floaters, dark curtain-like visual field defect, loss of central vision, and secondary strabismus/leukocoria in young infants.
- e. Dilated indirect ophthalmoscopy with scleral indentation, B-scan ocular ultrasonography, and Optical Coherence Tomography (OCT).